To conduct a systematic review and meta-analysis evaluating whether CPR guided by real-time feedback or post-event (debriefing-based) feedback improves CPR quality metrics or patient outcomes compared with standard unguided CPR in adult out-of-hospital cardiac arrest (OHCA). In August 2020, we searched PubMed, Embase, CINAHL, and the Cochrane Library for studies published studies after 2010 involving adult OHCA. Key CPR quality outcomes were chest compression depth, rate, and fraction. Critical patient outcomes were any return of spontaneous circulation (ROSC), survival to hospital admission, and survival to hospital discharge. From 9,464 identified records, 61 underwent full-text review, and 8 studies were ultimately included in the meta-analysis (5 examining real-time feedback devices, 3 examining post-event feedback/debriefing). Meta-analysis showed that: Real-time feedback significantly improved compression depth and rate. Post-event feedback significantly improved compression depth and chest compression fraction. No statistically significant improvement in patient outcomes (ROSC, survival to admission, or survival to discharge) was found for either type of feedback. However, absolute differences in survival rates suggested a potentially meaningful clinical benefit. Heterogeneity across studies ranged from low (“might not be important”) to considerable. Both real-time and post-event feedback improve specific aspects of CPR quality. Optimal CPR performance is likely achieved by combining the two approaches. Although neither feedback strategy demonstrated statistically significant improvements in patient survival, a clinically relevant effect appears plausible. These findings are based on a small number of studies with overall low to very low certainty of evidence.
Introduction
Survival after out-of-hospital cardiac arrest (OHCA) is strongly influenced by the quality of cardiopulmonary resuscitation (CPR), the main goal of which is to restore and maintain adequate blood flow to the heart and brain [1-3]. The best patient outcomes are achieved only when CPR is performed at a high standard [4].
The European Resuscitation Council (ERC) defines high-quality adult CPR as a compression rate of 100–120 compressions per minute, a compression depth of 5–6 cm, a chest compression fraction (the proportion of total resuscitation time spent actively compressing the chest) of at least 60%, complete chest recoil between compressions, and ventilations of 500–600 mL delivered in less than one second [1].
Delivering such performance in the out-of-hospital environment is difficult. Resuscitations frequently occur in cramped, chaotic, or physically challenging locations, and individual paramedics or EMS clinicians typically manage only a small number of cardiac arrests each year, which limits hands-on experience [5]. Numerous studies have demonstrated that CPR provided by professional emergency medical services often fails to meet recommended guideline targets [5, 6].
To help close this performance gap, different forms of CPR feedback have been introduced. Real-time feedback delivers immediate audio, visual, or combined prompts that show current performance metrics during the resuscitation attempt, enabling rescuers to make instant adjustments [6, 7]. Post-event debriefing consists of a structured, retrospective analysis of the team’s performance after the call, usually based on recorded data from the event [8]. The primary purpose of both real-time and post-event feedback is to bring actual CPR performance closer to evidence-based guidelines and, ultimately, to improve survival and neurological outcomes for patients with out-of-hospital cardiac arrest [8].
Previous systematic reviews have not provided a clear answer for out-of-hospital cardiac arrest specifically. For example, Wang et al. recently examined 11 studies that included both in-hospital and out-of-hospital cases and concentrated mainly on how different real-time feedback devices affected short-term survival [9]. An earlier review by Kirkbright et al. in 2014 looked at 20 studies across simulation, OHCA, and in-hospital settings and focused on whether real-time feedback improved CPR technique [10]. Yeung et al., in an even older review, analysed 28 studies that mixed real clinical cases with simulation data [11].
These reviews reached somewhat different conclusions: Wang suggested that survival benefit depends heavily on which device is used, while the other two groups generally found that feedback helps rescuers perform CPR closer to guidelines. Because all three reviews pooled together simulation, in-hospital, and out-of-hospital data, none could say with certainty what feedback actually does in real OHCA cases.
The current review was therefore designed to fill that gap. We focused only on studies published from 2010 onwards (the year when compression depth and rate targets changed and when modern feedback systems became widely available) and included only real clinical adult OHCA cases. Our goals were: (1) to compare the quality of CPR performed by EMS without any feedback against CPR performed with either real-time or post-event feedback, and (2) to examine whether the addition of feedback is linked to better patient survival outcomes.
Materials and Methods
This systematic review and meta-analysis was performed in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) statement [12] and followed the evidence-grading principles of the GRADE approach [13]. The review was framed using the Population, Intervention, Comparison, and Outcome (PICO) structure [14].
Protocol and registration The study protocol was prospectively registered with PROSPERO (registration number CRD42019133881; accessible at https://www.crd.york.ac.uk/prospero/). It was submitted on 30 April 2019 and accepted on 13 June 2019.
Eligibility criteria
Participants We included primary research involving adult patients with out-of-hospital cardiac arrest (OHCA) who received manual CPR delivered by pre-hospital professionals (paramedics, EMTs, physicians, or nurses working in the pre-hospital environment).
Interventions and comparators Eligible studies were required to objectively measure CPR quality through defibrillator-based recording of chest wall movement, with the device capable of quantifying compression rate at minimum. The interventions of interest were either (1) real-time audiovisual feedback displaying performance metrics during the resuscitation or (2) immediate or delayed post-event feedback/debriefing based on recorded data and/or evaluation of non-technical skills. These feedback strategies (real-time, post-event, or both) were compared against a control group in which neither real-time feedback nor structured post-event debriefing was provided.
Outcomes Critical outcomes were improvements in CPR quality parameters, including one or more of the following: chest compression depth (CCD), compression rate (CCR), chest recoil, compression fraction (CCF), and ventilation variables. Important clinical outcomes were any return of spontaneous circulation (ROSC), 30-day survival, and survival to hospital discharge.
Study types We included randomised controlled trials (RCTs), non-randomised controlled trials, and observational before-and-after studies that provided comparative data from real adult OHCA cases treated by emergency medical services with manual CPR. Only articles published in English or Danish from 2010 onward were considered. Editorials, commentaries, letters, opinion pieces, conference abstracts without full-text publication, and media reports were excluded.
Information sources
Search strategy We used a comprehensive three-pronged search strategy: (1) systematic electronic database searching, (2) direct consultation with content experts, and (3) forward and backward citation searching (snowballing) of all studies that reached final inclusion. The search was designed by the lead author (RML) together with an experienced research librarian. Four databases were searched in August 2020 by RML: PubMed, Embase, CINAHL, and the Cochrane Library. Search strings combined controlled vocabulary (MeSH or equivalent) with free-text terms covering out-of-hospital cardiac arrest, emergency medical services, CPR feedback, real-time prompts, post-event debriefing, CPR quality metrics, return of spontaneous circulation, survival, and neurological outcome.
Study selection Records retrieved from all sources were imported into Zotero (version 5.0.82), deduplicated, and then uploaded to Covidence systematic review software (Veritas Health Innovation, Melbourne, Australia) for screening. Screening proceeded in three stages (title, abstract, full text) and was performed independently by two reviewers (RML and AMC). Studies that passed title/abstract screening advanced to full-text assessment using the pre-specified eligibility criteria. References of finally included articles were hand-searched for additional relevant studies, which then underwent the same screening process. Any disagreements at any stage were resolved by consensus discussion. Inter-rater agreement was assessed by calculating Cohen’s kappa using SAS version 9.4.
Data extraction A customized data extraction form was created in Covidence prior to the start of the review. Two reviewers (RML and MNH) independently extracted data from each included study. Covidence automatically flagged discrepancies, which were resolved through discussion until consensus was reached.
Extracted variables (1) participant characteristics (age, sex), (2) cardiac arrest characteristics (location, witnessed status, bystander CPR), (3) system and setting details (defibrillator model, provider level, resuscitation guidelines in use, country), (4) study characteristics (design, data collection period, sample size, type of feedback intervention – real-time, post-event, or both).
Risk of Bias Assessment
Two reviewers (RML and MNH) independently evaluated the risk of bias in every included study.
Randomised trials were appraised with the Cochrane Risk of Bias tool [14], which examines random sequence generation, allocation concealment, blinding of participants and providers, blinding of outcome assessors, completeness of reported data, selective reporting, and any other notable concerns. Each domain was classified as low risk, high risk, or unclear risk when details were lacking.
Non-randomised studies were assessed using the ROBINS-I instrument [15]. This tool judges risk across seven areas: confounding (with pre-defined critical confounders being patient age and sex, initial cardiac rhythm, bystander CPR, and changes in AHA/ERC guidelines over time), participant selection, classification of the intervention, deviations from the intended intervention, missing outcome data, outcome measurement, and selective reporting. Within each domain the risk was rated as low, moderate, serious, or critical; the overall risk-of-bias rating for a study was determined by its highest (worst) domain score. Domains without sufficient information were marked as unclear risk.
The initial assessment was performed by one reviewer (RML) and then thoroughly discussed and finalised in collaboration with the second reviewer (MNH) until agreement was reached.
Inter-rater agreement at the full-text screening stage was quantified using Cohen’s kappa coefficient, interpreted according to standard thresholds: ≤0 (no agreement), 0.01–0.20 (none to slight), 0.21–0.40 (fair), 0.41–0.60 (moderate), 0.61–0.80 (substantial), and 0.81–1.00 (almost perfect) [16].
All meta-analyses were conducted using a random-effects model, with separate pooled estimates generated for real-time feedback and post-event feedback. Dichotomous outcomes were expressed as risk ratios (RR) with 95% confidence intervals. Continuous outcomes were expressed as mean differences (MD) with 95% confidence intervals. Statistical heterogeneity was evaluated with the I² statistic and interpreted using Cochrane guidelines: 0%–40% (heterogeneity might not be important), 30%–60% (moderate), 50%–90% (substantial), and 75%–100% (considerable). Overlapping categories were accepted up to a maximum I² of 60%. All analyses and forest plots were performed in Review Manager 5.2 (The Nordic Cochrane Centre, Copenhagen, Denmark). Because of the small number of included studies, formal assessment of publication bias (e.g., funnel plot or Egger’s test) was not feasible.
When heterogeneity exceeded 60%, a sensitivity analysis was performed by sequentially removing individual studies to identify and exclude those primarily responsible for the high inconsistency.
Certainty of evidence The overall certainty of the body of evidence was graded using the GRADE framework [13]. Randomised trials began with a “high” rating and could be downgraded for limitations in risk of bias, inconsistency, indirectness, imprecision, or suspected publication bias. Observational studies started at “low” certainty and could be upgraded for large magnitude of effect or absence of plausible residual confounding, and downgraded for the same reasons as randomised trials. The final GRADE rating (high, moderate, low, or very low) for each outcome reflected the lowest certainty rating among the critical outcomes.
Results and Discussion
Study selection
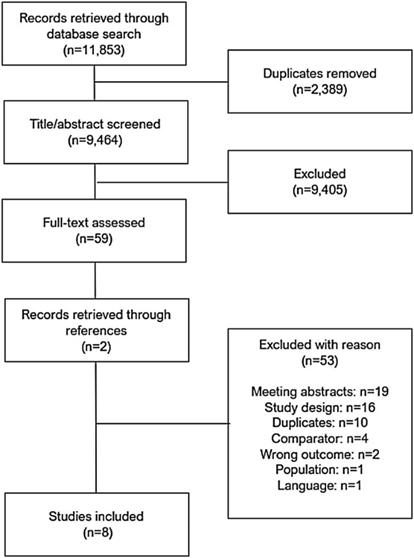
The electronic database search yielded 11 853 records. After removal of 2389 duplicates, 9464 unique citations remained for title and abstract review. Of these, 9405 were excluded as clearly irrelevant. Although formal Cohen’s kappa could not be calculated at this stage due to the low number of conflicts, the two independent reviewers achieved 98.8% proportional agreement (109 disagreements resolved through discussion).
This left 59 articles for full-text assessment. An additional two studies were identified through reference checking of included papers and consultation with experts, bringing the total to 61 full-text articles. During full-text review, 53 studies were excluded for not meeting the inclusion criteria.
Inter-rater reliability at the full-text stage produced a Cohen’s kappa of 0.87, indicating almost perfect agreement[16], which the review team considered excellent. Ultimately, eight studies were included for qualitative synthesis and meta-analysis (Figure 1) [3, 17–23].
|
|
|
Figure 1. PRISMA flowchart |
Excluded studies
Among the 53 full-text articles excluded, 19 were only conference abstracts, 16 had an ineligible study design, 10 were duplicates that Covidence failed to detect, 4 used a control group other than standard (non-feedback) CPR, 2 measured incorrect outcomes, 1 involved the wrong patient population, and 1 was published in German.
Characteristics of included studies Only one study was designed as a cluster-randomised controlled trial [19]. All eight included papers were published in English between 2011 and 2020. Five examined real-time audiovisual feedback [18- 21, 23], while the remaining three focused on post-event debriefing [3, 17, 22] Together they comprised 4601 patients, with individual study sizes varying from 52 to 1586.
Three studies were performed in the United States [18, 19, 22] and five in Europe (Finland [21], Spain [20], Scotland [3], the Netherlands [17] and Germany[23]). Four studies followed the 2005 ERC/AHA guidelines, [3, 19-21] three adhered to the 2010 guidelines [17, 18, 22] and one used the 2015 guidelines [23].
Of the real-time feedback studies, three reported both CPR quality metrics and clinical outcomes, [18, 19, 23] whereas two reported clinical outcomes only [20, 21]. Among the post-event debriefing studies, two provided CPR quality data [17, 22] and one also included clinical outcomes [3]. All post-event feedback was delivered as delayed debriefing (24–72 hours after the event), but none of the papers described the debriefing format, script, framework, or specific content discussed during the sessions.
A detailed summary of study characteristics and reported CPR quality variables is presented in Table 1.
Table 1. Characteristics of included studies
|
Study and Country |
Design |
Intervention |
N (Total) |
Age (mean ± SD or as reported) |
Gender – Males |
Location of Arrest – Public |
Bystander CPR |
Study Period |
Device / Guidelines / Providers |
Compression Depth (cm) |
Compression Rate (per min) |
Compression Fraction (%) |
|
Hostler et al. [19] USA |
Cluster-randomized controlled trial |
Real-time audiovisual feedback |
1,586 |
Control: 66 ± 17 Intervention: 65 ± 17 |
Control: 62% Intervention: 64% |
Control: 13% Intervention: 14% |
Control: 50% Intervention: 52% |
25 months |
Philips HeartStart MRx monitor-defibrillator 2005 AHA guidelines (presumed) EMS providers |
Control: 3.78 Intervention: 3.96 |
Control: 108 Intervention: 103.1 |
Control: 64 Intervention: 65.9 |
|
Bobrow et al. [18] USA |
Before–after cohort |
Real-time audiovisual feedback |
484 |
Control: 69 (59–79) Intervention: 68 (55–79) |
Control: 64.2% Intervention: 68.7% |
Control: 14.2% Intervention: 11.9% |
Control: 44% Intervention: 35.7% |
34 months |
ZOLL E-Series Guidelines unclear (data collection 2005–2010 era) Paramedics/EMTs |
Control: 4.4 Intervention: 5.4 |
Control: 126 Intervention: 105 |
Control: 65.6 Intervention: 87.3 |
|
Sainio et al. [21] Finland |
Prospective cohort |
Real-time feedback |
52 |
Control: 60 ± 20 Intervention: 66 ± 17 |
Control: 72% Intervention: 67% |
Control: 25% Intervention: 40% |
No data |
18 months |
Philips HeartStart MRx 2005 guidelines Physicians & paramedics |
No data |
No data |
No data |
|
Leis et al. [20] Spain |
Prospective cohort |
Real-time feedback |
892 |
Control: 62.7 ± 18.9 Intervention: 62.6 ± 17.4 |
Control: 66.2% Intervention: 72.2% |
No data |
No data |
37 months |
Device not reported 2005 guidelines EMS teams |
No data |
No data |
No data |
|
Lakomek et al. [23] Germany |
Prospective cohort |
Real-time feedback (CorPatch) |
292 |
Control-A: 69.6 ± 14.2 Control-B: 69.8 ± 16.0 Intervention: 71.0 ± 13.0 |
Control-A: 64% Control-B: 56% Intervention: 70% |
No data |
Control-A: 41% Control-B: 50% Intervention: 55% |
25 months |
Corpuls monitor with CorPatch 2015 guidelines Physician-based EMS |
Control-A: no data Control-B: 5.25 Intervention: 5.57 |
Control-A: 127.8 Control-B: 123.0 Intervention: 119.2 |
Control-A: 80.1 Control-B: 87.5 Intervention: 88.9 |
|
Bleijenberg et al. [17] Netherlands |
Before–after cohort |
Post-event debriefing (delayed, oral + objective/subjective data) |
124 |
Control: 68 ± 17 17 Intervention: 66 ± 17 |
Control: 71% Intervention: 70% |
No data |
No data |
31 months |
LIFEPAK 12 2010 guidelines (presumed) Paramedics & ambulance drivers |
No data |
No data |
Control: 79 Intervention: 86 |
|
Lyon et al. [3] Scotland |
Before–after cohort |
Post-event debriefing (delayed, written, objective + subjective) |
111 |
Control: 67 ± 17 Intervention: 64 ± 17 |
Control: 41.2% Intervention: 66.2% |
No data |
No data |
13 months |
LIFEPAK 12 2005 guidelines (presumed) Ambulance crews |
No data |
Control: 124.5 Intervention: 121.3 |
Control: 73 Intervention: 79.3 |
|
Weston et al. [22] USA |
Before–after cohort |
Post-event feedback (self-assessment form, 72 h delayed, written, objective) |
1,060 |
Control: 61.3 ± 17.3 Intervention: 61.4 ± 17 |
Control: 61.8% Intervention: 58.3% |
No data |
No data |
18 months |
ZOLL X-Series 2010 guidelines (presumed) BLS & ALS providers |
Control: 5.0 Intervention: 5.5 |
Control: 109.6 Intervention: 114.8 |
Control: 79.2 Intervention: 86.4 |
a No feedback sensor was attached to the patient during resuscitation.
b Feedback sensor was attached to the patient during resuscitation.
Results of meta-analysis
Chest compression depth
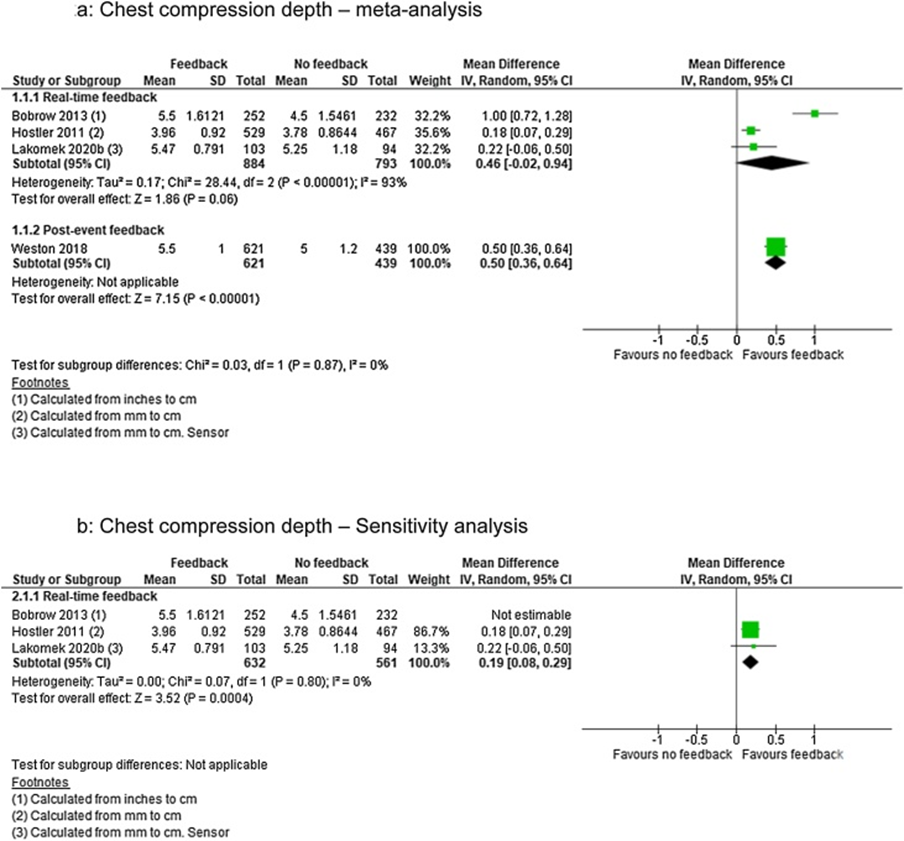
Regarding chest compression depth, the available evidence was of low certainty from one cluster-randomised controlled trial [19] (downgraded due to inconsistency and imprecision) and of very low certainty from three observational studies [18, 22, 23] (downgraded due to risk of bias). These four studies together comprised 3,327 patients.
The analysis of real-time feedback incorporated three studies [18, 19, 23], while post-event feedback was examined in a single study [22].
In the pooled analysis of real-time feedback, the overall effect was not statistically significant (mean difference 0.46 cm, 95% CI −0.02 to 0.94), accompanied by very high heterogeneity (I² = 93%) (Figure 2a). After exclusion of Bobrow et al. [18] in a sensitivity analysis, heterogeneity was eliminated (I² = 0%) and the pooled estimate shifted to a small but statistically significant benefit in favour of the intervention (mean difference 0.19 cm, 95% CI 0.08 to 0.29) (Figure 2b).
The single study that evaluated post-event feedback showed a clear benefit, with compression depth increasing by a mean difference of 0.50 cm (95% CI 0.36 to 0.64) in the intervention group (Figure 2a).
|
|
|
Figure 2. Chest compression depth — meta and sensitivity analysis |
Chest compression rate
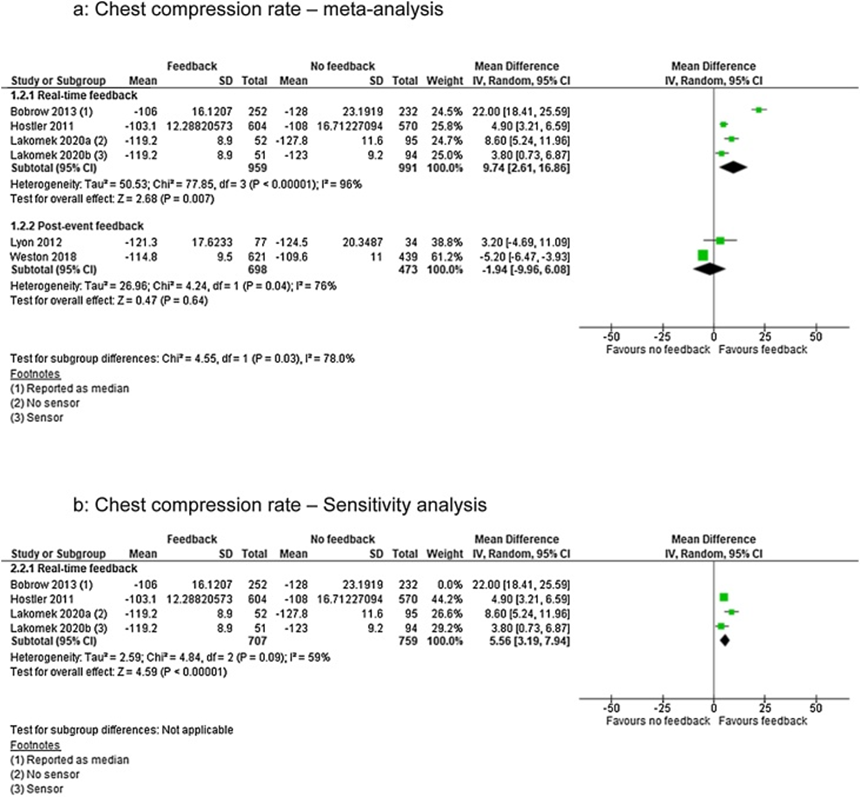
For chest compression rate, the evidence was of low certainty from one randomised controlled trial [19] (downgraded for inconsistency and imprecision) and of very low certainty from four observational studies [3, 18, 22, 23] (downgraded for risk of bias). These five studies included a total of 3,533 patients.
Three studies evaluated real-time feedback [18, 19, 23] and two evaluated post-event feedback [3, 22].
The pooled analysis of real-time feedback demonstrated a statistically significant reduction in compression rate favouring the intervention (mean difference −9.74 compressions per minute, 95% CI −16.86 to −2.61), although heterogeneity was very high (I² = 96%) (Figure 3a). When Bobrow et al. [18] was removed in a sensitivity analysis, heterogeneity decreased substantially (I² = 59%), while the beneficial effect persisted (mean difference −5.56 compressions per minute, 95% CI −7.94 to −3.19) (Figure 3b).
In contrast, post-event feedback showed no significant effect on compression rate (mean difference −1.94 compressions per minute, 95% CI −9.96 to 6.08), with considerable heterogeneity (I² = 76%) (Figure 3a). Because only two studies were available, no sensitivity analysis was performed.
|
|
|
Figure 3. Chest compression rate — meta and sensitivity analysis |
Chest compression fraction
Chest compression fraction
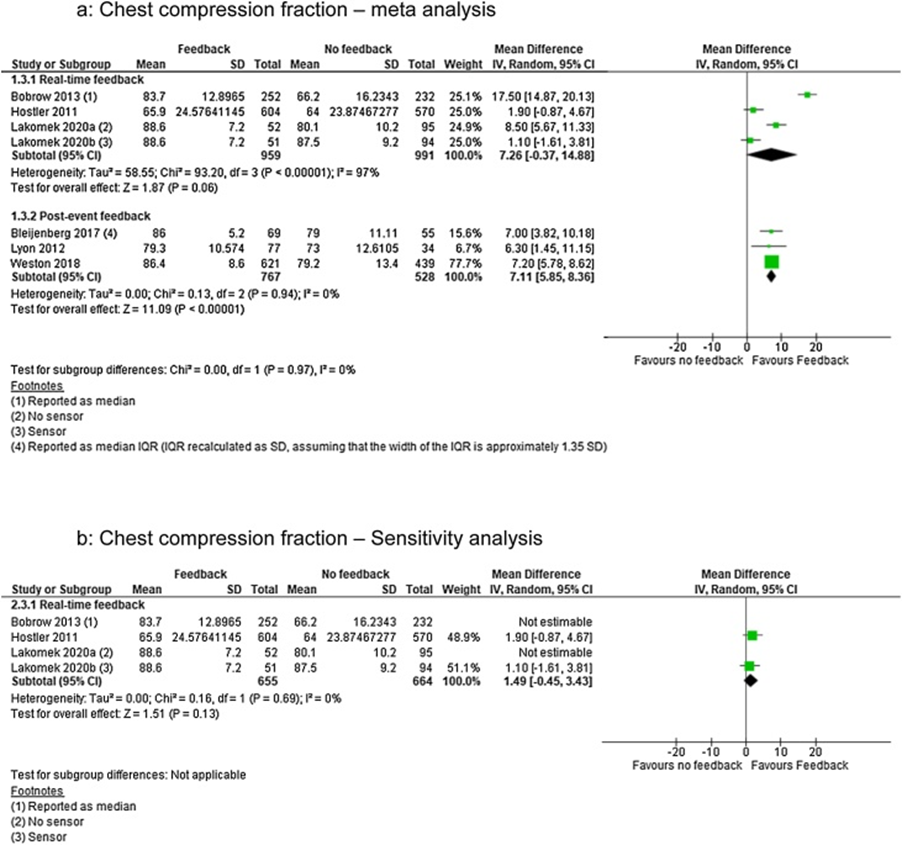
For chest compression fraction (CCF), the evidence was of low certainty from one randomised controlled trial [19] (downgraded for inconsistency and imprecision) and of very low certainty from five observational studies [3, 17, 18, 22, 23] (downgraded for risk of bias). These six studies encompassed a total of 3,657 patients.
Three studies assessed real-time feedback [18, 19, 23] and three assessed post-event feedback [3, 17, 22].
The pooled analysis of real-time feedback revealed no statistically significant improvement (mean difference 7.26%, 95% CI −0.37 to 14.88), with very high heterogeneity (I² = 97%) (Figure 4a). After excluding Bobrow et al. [18] and the no-sensor control group from Lakomek et al. [23] were excluded in a sensitivity analysis, heterogeneity fell to 0%, but the effect remained non-significant (mean difference 1.49%, 95% CI −0.45 to 3.43) (Figure 4b).
In contrast, post-event feedback demonstrated a clear and statistically significant benefit, with compression fraction increasing by a mean difference of 7.11% (95% CI 5.85 to 8.36) and no heterogeneity (I² = 0%) (Figure 4a).
|
|
|
Figure 4. Chest compression fraction — meta and sensitivity analysis |
Return of spontaneous circulation
For return of spontaneous circulation, the evidence was of low certainty from one cluster-randomised controlled trial [19] (downgraded for inconsistency and imprecision) and of very low certainty from five observational studies [3, 18, 20, 21, 23] (downgraded for risk of bias). These six studies included a total of 3,417 patients.
Five studies examined real-time feedback [18, 19, 20, 21, 23] and one examined post-event feedback [3].
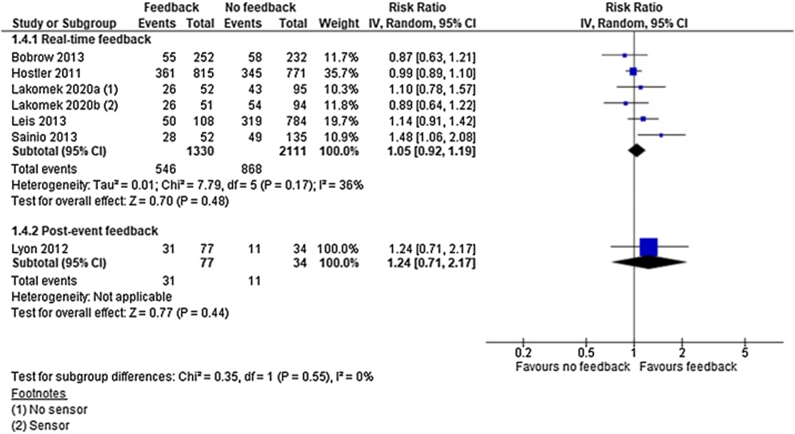
Neither real-time feedback (risk ratio 1.05, 95% CI 0.92 to 1.19; I² = 36%) nor post-event feedback (risk ratio 1.24, 95% CI 0.71 to 2.17) demonstrated a statistically significant effect on ROSC (Figure 5).
In absolute terms, the use of feedback (any type) was associated with 5.4 additional patients achieving ROSC per 1,000 treated compared with no feedback.
|
|
|
Figure 5. Return of spontaneous circulation — meta-analysis |
Survival to hospital/sustained return of spontaneous circulation
Survival to hospital admission or sustained ROSC
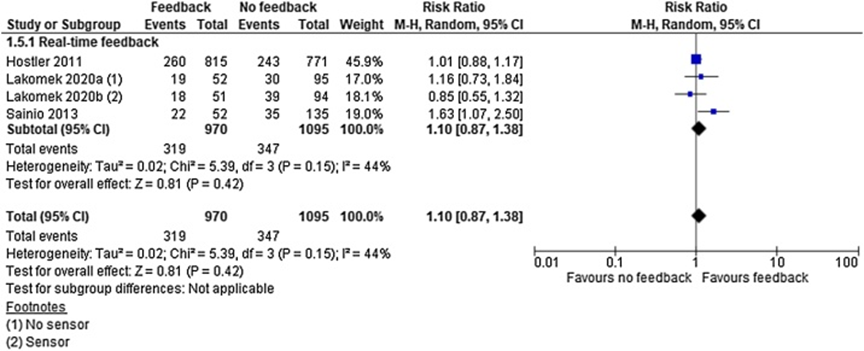
For survival to hospital admission or sustained ROSC, the evidence was of low certainty from one cluster-randomised controlled trial [19] (downgraded for inconsistency and imprecision) and of very low certainty from two observational studies [21, 23] (downgraded for risk of bias). These three studies included a total of 1,930 patients.
All three studies evaluated real-time feedback. Pooled analysis showed no statistically significant effect of the intervention (risk ratio 1.10, 95% CI 0.87 to 1.38; I² = 44%) (Figure 6).
In absolute terms, real-time feedback was associated with 12 additional patients per 1,000 achieving survival to hospital admission or sustained ROSC compared with no feedback.
|
|
|
Figure 6. Survival to hospital — meta-analysis |
Survival to hospital discharge
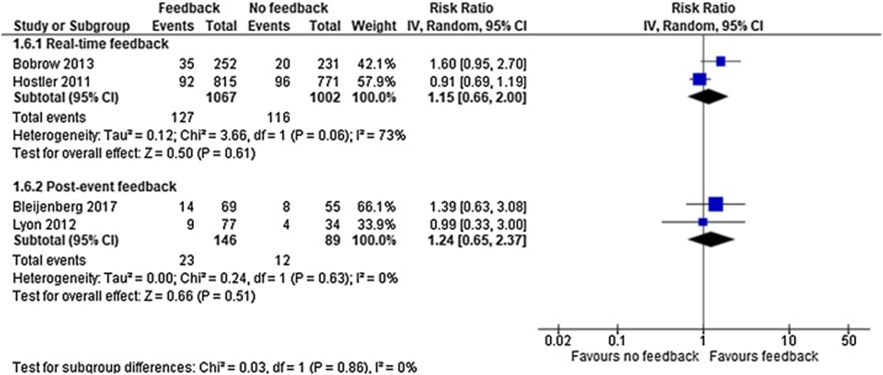
For survival to hospital discharge, we identified low-quality evidence from one cluster randomized controlled trial [19], downgraded due to inconsistency of results and imprecision, and very low-quality evidence from three observational studies [3, 17, 18], downgraded for limitations in study design. Two studies [18, 19] were included in the real-time feedback group, and two [3, 17] in the post-event feedback group, representing a total of 2,305 patients.
Analysis of real-time feedback revealed no statistically significant effect (RR 1.15; 95% CI, 0.66–2.00) but showed substantial heterogeneity (I² = 73%). Given that only two studies [18, 19] were available in this group, no sensitivity analysis was performed. Post-event feedback analysis similarly showed no significant effect (RR 1.24; 95% CI, 0.65–2.37) with no observed heterogeneity (I² = 0%) (Figure 7). In absolute terms, feedback was associated with approximately 6.3 additional patients discharged alive per 1,000 compared with no feedback.
|
|
|
Figure 7. Survival to hospital discharge — meta-analysis |
Risk of bias
Results from the Cochrane Risk of Bias tool assessment
Risk of bias assessment
Randomised controlled trial (RoB 2) Sequence generation and allocation concealment were judged as unclear risk due to inadequate reporting of methods. Blinding of participants and personnel was rated high risk; however, given the nature of the intervention (providers were necessarily aware when real-time or post-event feedback was provided), this was considered unavoidable and unlikely to affect objective CPR quality metrics or clinical outcomes. Blinding of outcome assessors was rated low risk. Incomplete outcome data attracted high risk because the handling and extent of missing data were not sufficiently described. Selective reporting and other potential sources of bias were both judged low risk.
Observational studies (ROBINS-I) Among the non-randomised studies: – In the confounding domain, five studies were classified as critical risk of bias [3, 17, 20, 21, 23]. – In the participant selection domain, two studies were rated serious risk [20, 21]. – In the domain of deviations from intended interventions, one study was rated serious [21]. In the missing data domain, one study was rated serious [23]. For all other domains across the remaining studies, the risk of bias was judged moderate or low (Table 2).
Table 2. Risk of bias
Observational studies – Risk of bias assessed with ROBINS-I tool
|
Study |
Confounding (D1) |
Selection of participants (D2) |
Classification of interventions (D3) |
Deviations from intended interventions (D4) |
Missing data (D5) |
Measurement of outcomes (D6) |
Selection of reported results (D7) |
Overall risk of bias |
|
Bleijenberg et al. [17] |
Critical |
Moderate |
Moderate |
Low |
Moderate |
Low |
Low |
Critical |
|
Bobrow et al. [18] |
Moderate |
Moderate |
Low |
Moderate |
Low |
Low |
Low |
Moderate |
|
Leis et al. [20] |
Critical |
Serious |
Low |
Low |
Moderate |
Low |
Low |
Critical |
|
Lyon et al. [3] |
Critical |
Moderate |
Low |
Low |
Moderate |
Low |
Low |
Critical |
|
Lakomek et al. [23] |
Critical |
Moderate |
Low |
Low |
Serious |
Low |
Low |
Critical |
|
Sainio et al. [21] |
Critical |
Serious |
Moderate |
Serious |
Moderate |
Moderate |
Low |
Critical |
|
Weston et al. [22] |
Moderate |
Moderate |
Low |
Low |
Moderate |
Low |
Low |
|
|
Study |
Sequence generation |
Allocation concealment |
Blinding of participants & personnel |
Blinding of outcome assessors |
Incomplete outcome data |
Selective reporting |
Other sources of bias |
Overall risk of bias |
|
Hostler et al. [19] |
Unclear |
Unclear |
High (unavoidable due to feedback) |
Low |
High |
Low |
Low |
High |
a Highest risk of bias judgement, was indicative of the overall judgement.
GRADE Assessment Results The overall certainty of the effect estimates was rated low for all outcomes because of serious inconsistency across studies and imprecision of the results. In the observational studies, certainty was further downgraded to very low owing to a serious risk of bias in addition to the same problems of inconsistency and imprecision.
Summary of evidence This systematic review focused specifically on feedback use during out-of-hospital cardiac arrest in real clinical practice. Real-time and post-event feedback differ fundamentally in timing and therefore in their potential impact: real-time feedback permits immediate corrections during the resuscitation itself, whereas post-event feedback can influence only future cases. After adjustment for heterogeneity in compression depth (CCD), compression rate (CCR), and chest compression fraction (CCF), real-time feedback was associated with improvements in compression depth and rate, although chest compression fraction showed no significant change. Post-event feedback improved compression depth and chest compression fraction (with no remaining heterogeneity) but not compression rate (heterogeneity could not be adjusted). Neither form of feedback demonstrated clear superiority with respect to return of spontaneous circulation, survival to hospital admission (no heterogeneity), or survival to discharge (heterogeneity could not be adjusted in the real-time feedback analyses). Despite a comprehensive search strategy, the included studies provided only low to very low certainty evidence.
In comparison with earlier reviews, Wang et al. did not present CPR performance metrics and instead analyzed results according to the type of feedback device, so direct comparison with the present findings must be interpreted cautiously; nevertheless, their results similarly suggest that real-time feedback may not improve patient outcomes. In contrast to Kirkbright et al., who found no benefit of feedback for patient-centered outcomes, the current review identified a non-significant trend favoring feedback.
Effect of feedback on CPR quality metrics The impact of feedback on CPR quality differs according to whether the feedback is real-time or post-event and according to which component is examined (compression depth, rate, or fraction). Several factors may account for these findings and for the only partial confirmation of the review’s original hypothesis. One important factor is the “one-size-fits-all” nature of current CPR guidelines, which are derived from data on average-sized adults. In obese or underweight patients, rescuers may need to modify compression depth to achieve physiologically appropriate force, resulting in apparent non-compliance with guidelines even though the compressions are clinically correct. A similar distortion can occur when chest compressions are performed on soft surfaces, producing the so-called mattress effect [24, 25].
Effect of feedback on patient outcome Our meta-analysis showed no association between feedback (real-time or post-event) and improved patient outcomes. Several factors likely explain this absence of effect. First, although feedback produced statistically significant improvements in certain CPR quality metrics, these gains were often modest and may fall below the threshold required for clinically meaningful benefit. More importantly, high-quality CPR depends on five interrelated components; enhancing just one or two of them is unlikely to translate into better survival. Finally, CPR quality represents only one link in the chain of survival from out-of-hospital cardiac arrest. Critical time-dependent factors such as time to defibrillation, bystander CPR, and emergency response interval can dominate outcomes and easily overshadow any modest benefit derived from feedback-guided CPR.
Strengths
This review distinguishes itself from earlier work by focusing exclusively on out-of-hospital cardiac arrest, thereby addressing a specific pre-hospital context with its unique environmental and logistical constraints. By including both real-time and post-event feedback approaches in the same analysis, we provide a comprehensive and transparent evidence base to guide clinical quality-improvement initiatives and decision-making regarding feedback use in pre-hospital resuscitation.
Limitations
Research on feedback during out-of-hospital cardiac arrest remains limited, as evidenced by the small number of eligible studies and their consistently low or very low certainty of evidence. This inevitably reduces confidence in our effect estimates. Excluding studies because of poor methodological quality or high risk of bias was intentionally avoided to preserve the breadth of available evidence in this understudied but critical area of pre-hospital care; consequently, considerable uncertainty surrounds our conclusions. Minor improvements or adjustments within an already high-quality performance range may simply be too subtle to influence patient-centred outcomes, and most included studies were not powered to detect differences in survival. Post-event feedback was heterogeneous in delivery method; our findings primarily reflect delayed feedback and may not apply to other formats. Finally, not all studies specified which resuscitation guidelines were in effect during data collection, preventing strict guideline-based inclusion criteria. To minimise inclusion of data collected under pre-2005 guidelines, we restricted eligibility to publications from 2010 onward.
Considerations for future research High-quality studies that evaluate CPR feedback in out-of-hospital cardiac arrest according to current guideline recommendations are needed, with sufficient power to assess both CPR quality metrics and patient-centred outcomes.
Conclusion
Evidence of low to very low certainty indicates that real-time feedback improves compression depth and compression rate, whereas post-event feedback improves compression depth and chest compression fraction. Neither type of feedback was associated with higher rates of return of spontaneous circulation, survival to hospital admission, or survival to discharge. Robust, adequately powered research on feedback strategies in the pre-hospital setting remains essential.
Acknowledgments: None.
Conflict of interest: None.
Financial support: This review has been supported by the TrygFoundation. Copenhagen Emergency Medical Services receives funding from Laerdal Foundation. Parker institute is supported by the Oak Foundation. Funders had no role in study design, data collection, data analysis or data interpretation, writing of the report or to submit the article for publication.
Ethics statement: None.