Information regarding the ‘Phase of Illness’ within specialized home-based palliative care remains unavailable in Switzerland. This study aimed to examine how oncological patients and their informal caregivers experience burden, needs, and associated resource utilization across each specific ‘Phase of Illness’ to establish a comprehensive profile of every phase’s unique attributes. A convergent parallel mixed-methods approach was utilized. For the quantitative component (comprising 91 adult oncology patients and 54 informal caregivers), data were gathered on clinical/sociodemographic profiles, phase-associated symptomatology, burden, needs, and resource utilization. For the qualitative component, semi-structured interviews were conducted with 8 patients and 12 informal caregivers, and focus groups were held with 20 nursing professionals. Data synthesis and analysis involved factorial ANOVA, repeated-measures ANOVA, qualitative content analysis, and joint display integration. The investigation identified distinctive central concepts and targeted action priorities for every individual ‘Phase of Illness’: “ambivalence” paired to “keep it under control” (stable), “anxiety and uncertainty” directed toward “de-escalation” (unstable), “the tangible end of life” oriented around “enduring” (deteriorating), “clarity” focused on “focusing on essentials” (terminal), and “finality” aimed at “finding a conclusion” (bereavement). The outcomes underscore the profound vulnerability and multi-faceted nature of the challenges and requirements faced by cancer patients and their relatives across all stages of specialized home-based palliative care. Care frameworks and reimbursement models within specialized home palliative care must be secured to adequately support the psychosocial vulnerabilities of patients and families, particularly during the stable and bereavement stages.
Introduction
Casemix classification frameworks categorize patient populations into distinct, homogeneous cohorts using core criteria (such as diagnoses) based on their clinical needs and resource utilization. Beyond underpinning healthcare financing and reimbursement models, casemix frameworks serve as tools for identifying and communicating patient care needs [1]. Nonetheless, conventional casemix systems anchored strictly on diagnoses and clinical interventions prove inadequate for capturing the holistic requirements of individuals receiving palliative care. Furthermore, they are ineffective at forecasting corresponding resource consumption [2]. To address this, the Australian Healthcare System instituted a specialized casemix classification tailored for subacute and non-acute medical care, incorporating palliative care as one of its five key case types [3]. The parameters used to categorize patients under the palliative care designation include age, problem severity, functional capacity, and the current ‘Phase of Illness’ [4]. The ‘Phase of Illness’ framework incorporates five separate stages: ‘stable’, ‘unstable’, ‘deteriorating’, ‘terminal’, and ‘bereavement’. These stages operate independently of disease staging or prognosis, meaning they can manifest in any sequence (except for the terminal and bereavement phases). Rather, the primary benchmarks for the assignment are the patient’s care requirements and whether the current management plan is suitable for addressing those needs [5]. Mather et al. [1] emphasize that the ‘Phase of Illness’ serves as a valuable clinical tool for appraising comprehensive palliative demands and forecasting subsequent resource needs.
This Australian casemix model has laid the groundwork for the sustainable collection of longitudinal palliative care outcome data. Advancements in palliative care quality have been realized by merging routine clinical outcome tracking, institutional benchmarking, data feedback loops, and targeted quality enhancement strategies [6]. Correspondingly, initiatives are underway across Europe to develop, implement, and embed palliative care casemix models and outcome measurement systems [7-9]. Even though healthcare funding and operational models vary considerably within and across national systems, the use of standardized outcome metrics is essential for global benchmarking and collaborative research [10]. This practice establishes a shared terminology across distinct healthcare disciplines, clinical facilities, and nations [11]. Implementing such a uniform language has been shown to elevate clinical communication, optimize assessment procedures, and improve longitudinal patient tracking by providing a structured, reliable template for care planning and clinical handovers [12].
The integration of patient- and proxy-reported outcome assessments is gaining prominent traction in Switzerland. Nevertheless, the ‘Phase of Illness’ framework remains under-established in the Swiss context, particularly within specialized home-based palliative care, as prior initiatives have predominantly targeted specialized inpatient palliative care departments [13, 14]. Consequently, there is a lack of Swiss data addressing the specific burdens, needs, and resource use of patients and informal caregivers across individual phases. This study, therefore, sought to analyze patient and caregiver perceptions of burden, needs, and related resource allocation within each ‘Phase of Illness’ to supply an exhaustive description of the attributes defining each stage. The scope was restricted to cancer patients under specialized home palliative care and their informal caregivers. This group was selected because the participating home care organizations primarily served oncology cohorts. Additionally, physical and psychosocial distress profiles differ markedly between oncological and non-oncological diagnoses within community palliative care [15], necessitating a singular focus on oncology.
Materials and Methods
A convergent parallel mixed-methods framework was adopted [16]. The quantitative track utilized a cross-sectional survey methodology [17, 18], while the qualitative track employed a descriptive qualitative approach [19]. Both arms were weighted equally to capture a comprehensive understanding of the distinct traits of each ‘Phase of Illness’. This mixed-methods methodology was selected to effectively capture the intricacies of the topic while minimizing participant fatigue by aligning data collection precisely with the core research inquiries to ensure institutional relevance. Furthermore, this method is uniquely suited to palliative care research, where clinical actions are inherently holistic and custom-tailored, demanding both conceptual depth and analytical breadth [20, 21]. Reporting aligned with the Good Reporting of a Mixed Methods Study (GRAMMS) guidelines.
Fieldwork was conducted from March 2020 through April 2022. Eligible candidates included adult individuals diagnosed with cancer alongside their primary informal caregivers. Participants were under the care of one of three specialized community nursing teams operating across two municipal regions in Switzerland. These three cohorts functioned under comparable administrative structures and comprised specialized palliative care nursing professionals. Depending on the clinical severity of the home scenario, these nursing teams integrated their care with general practitioners (possessing palliative credentials) or dedicated palliative medicine physicians.
A convenience sampling approach was used for the quantitative arm, whereas a purposeful sampling strategy (maximizing variation) was utilized for the qualitative arm. Recruitment was facilitated by clinical staff within the specialized palliative teams, who evaluated existing and newly registered patients against the eligibility parameters (adult oncological patients) and extended participation invitations for the quantitative tracking. Individuals presenting with an Australia-modified Karnofsky Performance Status (AKPS) score of $\le 20$ [22] were excluded from data gathering to protect highly vulnerable and heavily burdened patients. All candidates provided formal written informed consent before enrollment. Qualitative recruitment was coordinated closely with the primary research team, utilizing a consecutive selection strategy informed by concurrent insights extracted from ongoing interview transcript analyses. Qualitative analysis was performed iteratively alongside data gathering, and recruitment ceased upon reaching data saturation, defined as the point at which no novel conceptual themes emerged from the text [23].
Quantitative assessments were completed once per subject via a battery of paper-administered patient- and proxy-centered instruments (Table 1). During the bereavement stage, data collection was restricted to the sociodemographic profiles of the informal caregivers and the medical backgrounds of the deceased patients. Qualitative insights were gathered through individual semi-structured interviews with patients and relatives, as well as three distinct focus groups with nursing staff from the participating home care agencies. The interview frameworks were designed specifically for this investigation. Pre-testing was conducted for all survey instruments and the qualitative interview templates intended for patients and their caregivers.
Table 1. Study measures. From: ‘Phase of Illness’ in oncology patients receiving specialist palliative home care: a mixed methods study on phase-specific burden, needs and use of resources.
|
Instrument |
Completed by |
Purpose and measurement |
Remarks/References |
|
Sociodemographic survey |
Patients, Family caregivers, Healthcare staff |
A custom-designed questionnaire collected participant background characteristics. For patients and family caregivers, information included age, sex, migration status, living arrangement, educational attainment, and use of professional support services. The staff version gathered age, sex, education, professional experience, and employment percentage. Every participant involved in the focus group discussions completed this survey. |
— |
|
Clinical information form |
Healthcare staff |
An investigator-developed form used to record patients’ primary and comorbid diagnoses, cancer stage, and all current or completed medical and non-medical treatments. |
— |
|
German phase of illness classification |
Healthcare staff |
Patients were assigned to one of five predefined clinical stages: stable, unstable, deteriorating, terminal, or bereavement, according to their disease status. |
[1, 5] |
|
German palliative care outcome scale (POS) |
Patients, Family caregivers, Healthcare staff |
This instrument evaluates physical, emotional, psychological, and spiritual concerns, together with information and support needs, using 10 scored items on a 5-point response scale (0 = no needs; 4 = overwhelming needs). The original first 2 items were omitted because symptom assessment was performed using MIDOS. Item 11 allows respondents to describe their principal concern in free text. Item 12 differs by respondent group: caregivers and staff rate functional performance using the Eastern Cooperative Oncology Group (ECOG) Performance Status Scale (5-point scale: 0 = normal activity; 4 = completely bedridden), whereas patients indicate whether they completed the questionnaire independently. |
Established and psychometrically validated assessment tool [10, 24] |
|
Minimal documentation system (MIDOS) |
Patients, Family caregivers, Healthcare staff |
Symptom severity is evaluated across 13 symptoms, each scored on a 4-point scale (0 = no symptoms; 3 = overwhelming symptoms), with an additional 1 open-response section for comments. |
German validation of the Edmonton Symptom Assessment Scale (ESAS) [25] |
|
German Barthel Index |
Healthcare staff |
Functional ability in activities of daily living is measured using 10 domains with weighted scoring. Scores range from 0 to 20, with 20 representing complete independence. |
Originally designed for neurological rehabilitation and later validated for palliative care populations [26, 27] |
|
German caregiver quality of life index–cancer (CQOLC) |
Family caregivers |
Caregiver well-being is assessed through 35 questions, each rated on a 5-point scale (0 = not at all affected; 4 = very much affected). |
Frequently used and validated quality-of-life measure [28, 29] |
|
Healthcare resource utilization questionnaire |
Healthcare staff |
A project-specific questionnaire was designed to quantify the amount of care delivered by the 3 participating home-care teams. It documented nursing input from specialist palliative care teams, other specialist community nursing services (e.g., psychiatric nursing), and general home-care nursing services. Service duration was estimated according to the Swiss outpatient reimbursement framework. |
Because specialist palliative home-care services had no formal reimbursement mechanism during the bereavement phase, they were typically no longer involved. Consequently, this instrument was not administered during that stage. |
Quantitative data processing was executed by a biostatistician utilizing IBM SPSS Statistics 28. Data properties were classified according to measurement scales using frequency distributions and appropriate descriptive parameters. Variations across distinct independent sub-samples (such as the specific ‘Phase of Illness’) were evaluated via ANOVA combined with post-hoc comparisons (Bonferroni adjustment). When statistical assumptions were violated (such as homogeneity of variances), the Kruskal-Wallis test was used. For longitudinal or multi-perspective measures (such as evaluating symptom scores across disparate viewpoints), repeated-measures ANOVA was employed. Where the assumption of sphericity was violated (assessed via Mauchly’s test), the Greenhouse-Geisser adjustment was applied. The significance threshold for all statistical computations was fixed at 5%.
Qualitative thematic content analysis was performed by three investigators (DB, EB, AK) according to the methodological steps outlined by Schreier [30]. (1) The primary author conducted an exhaustive reading of the data transcripts to flag critical sections, appending analytical notes and clinical observations. (2) Five primary analytical codes were deductively established based on the pre-existing “Phase of Illness” framework. (3) Two investigators (DB, EB) worked independently to code the text data line by line during the initial analysis phase using these main headers. (4) An index was constructed grouping all coded text extracts corresponding to each main category. (5) Secondary subcategories were subsequently derived inductively from the text contents by two authors (DB, EB), who evaluated all extracted subcategories, integrated them into broader conceptual groups, and drafted explicit definitions for each. (6) A comprehensive re-coding of the entirety of the transcripts was completed during a secondary review cycle by the first author. (7) An analytical evaluation was executed by three authors (DB, EB, AK) to examine, map, and contrast the interactions between the emerging categories.
Integration of the qualitative and quantitative tracking arms was achieved by three authors (DB, EB, AK) using joint displays [31].
Results and Discussion
Characteristics of participants
An analytical breakdown of participant demographics and clinical details is displayed in Table 2. A total of 34 eligible patients or their informal caregivers chose not to enroll in the investigation, a decision driven primarily by the progressive decline of the patient’s physical state. Each participant was assessed within a single, static illness stage; the study design did not track longitudinal transitions across multiple phases.
Table 2. Characteristics of patients, family caregivers, and nurses. From: ‘Phase of Illness’ in oncology patients receiving specialist palliative home care: a mixed methods study on phase-specific burden, needs and use of resources
|
Characteristic |
Qualitative: Nurses |
Qualitative: Family caregivers |
Qualitative: Patients |
Quantitative: Family caregivers |
Quantitative: Patients |
|
Sample size (n) |
20 |
12 |
8 |
54 |
91 |
|
Illness phase, n (%) |
|
|
|
|
|
|
Stable |
— |
5 (41.7) |
7 (87.5) |
— |
38 (42.9) |
|
Unstable |
— |
1 (8.3) |
— |
— |
16 (17.6) |
|
Deteriorating |
— |
1 (8.3) |
1 (12.5) |
— |
22 (24.2) |
|
Terminal |
— |
— |
— |
— |
11 (12.1) |
|
Bereavement |
— |
5 (41.7) |
— |
— |
3 (3.3) |
|
Missing data |
— |
– |
– |
— |
1 (1.1) |
|
Gender, n (%) |
|
|
|
|
|
|
Female |
16 (80.0) |
9 (75.0) |
6 (75.0) |
40 (74.1) |
50 (54.9) |
|
Male |
4 (20.0) |
3 (25.0) |
2 (25.0) |
14 (25.9) |
35 (38.5) |
|
Missing data |
– |
– |
– |
– |
6 (6.6) |
|
Age in years, Mean [minimum; maximum] |
— |
— |
— |
59 [20;86] |
71 [32;101] |
|
Missing observations (n) |
— |
— |
— |
1 |
8 |
|
Household arrangement, n (%)* |
|
|
|
|
|
|
Residing alone |
— |
— |
— |
2 (3.7) |
35 (38.5) |
|
Living with a spouse or partner |
— |
— |
— |
50 (92.6) |
35 (38.5) |
|
Living with sibling(s) |
— |
— |
— |
2 (3.7) |
0 (0) |
|
Living with parent(s) |
— |
— |
— |
1 (1.9) |
0 (0) |
|
Living with child(ren) |
— |
— |
— |
9 (16.7) |
5 (5.5) |
|
Missing data |
— |
— |
— |
– |
16 (17.6) |
|
Born in Switzerland, n (%) |
— |
— |
— |
42 (77.8) |
59 (64.8) |
|
Missing data |
— |
— |
— |
– |
16 (17.6) |
|
Educational attainment, n (%) |
|
|
|
|
|
|
Compulsory schooling |
— |
— |
— |
5 (9.3) |
4 (4.4) |
|
Apprenticeship/Vocational training |
— |
— |
— |
18 (33.3) |
25 (27.5) |
|
High school |
— |
— |
— |
6 (11.1) |
5 (5.5) |
|
University of Applied Sciences |
— |
— |
— |
9 (16.7) |
12 (13.2) |
|
University degree |
— |
— |
— |
14 (25.9) |
21 (23.1) |
|
Other qualification |
— |
— |
— |
2 (3.7) |
2 (2.2) |
|
Missing data |
— |
— |
— |
– |
22 (24.2) |
|
Duration of home care in months, Mean [minimum; maximum] |
— |
— |
— |
— |
9 [0;84] |
|
Missing observations (n) |
— |
— |
— |
— |
20 |
|
Primary tumor diagnosis, n (%) |
|
|
|
|
|
|
Gastrointestinal cancer |
— |
— |
— |
— |
33 (36.3) |
|
Gynecological cancer |
— |
— |
— |
— |
20 (22.0) |
|
Pulmonary cancer |
— |
— |
— |
— |
14 (15.4) |
|
Urological cancer |
— |
— |
— |
— |
9 (9.9) |
|
Cerebral cancer |
— |
— |
— |
— |
5 (5.5) |
|
Unknown diagnosis |
— |
— |
— |
— |
3 (3.3) |
|
Other cancer types |
— |
— |
— |
— |
7 (7.7) |
*multiple answers possible
Phase-specific symptoms, needs, and use of resources
A comparative analysis of the evaluation scores revealed statistically significant variations across patient, caregiver, and clinician perspectives for the MIDOS instrument, whereas no such variance was observed for the POS tool (repeated-measurement ANOVA, POS: $F(1.82, 124.06) = 1.00$, $p = 0.37$; MIDOS: $F(1.62, 109.85) = 4.74$, $p = 0.016$). Nonetheless, these statistical discrepancies were deemed clinically negligible because the calculated Mean Difference fell below 0.3, indicating that the variations did not alter the broader response classifications. On this basis, subsequent descriptions rely solely on the data gathered from the clinician versions of the POS and MIDOS, given the superior volume and completeness of this dataset. From a quantitative standpoint, the overall quality of life among informal caregivers remained remarkably constant across all phases (Factorial ANOVA, CQOLC, $F(3,83) = 1.12$, $p = 0.344$). In contrast, the qualitative narratives highlighted a persistent undercurrent of caregiver strain throughout every stage.
|
|
|
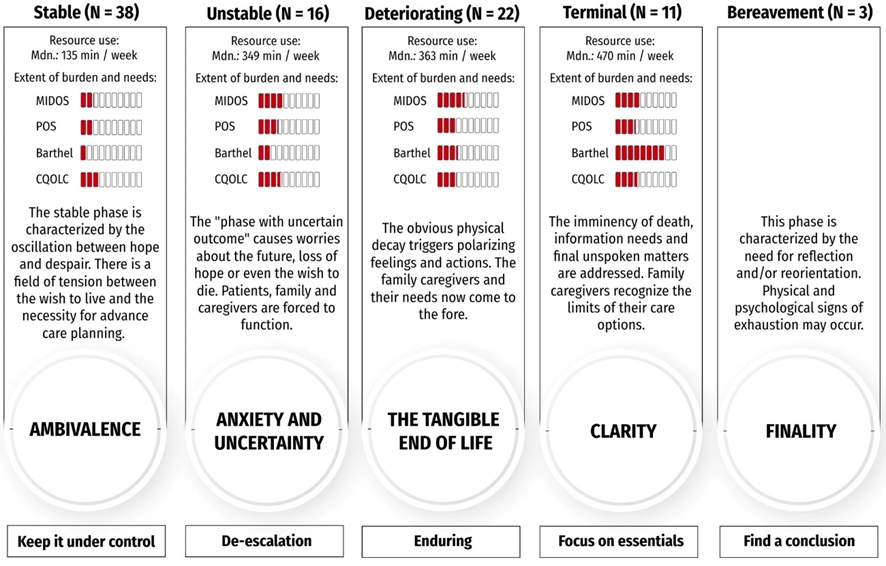
Figure 1. Summary of findings. |
The main theme of the respective phase is shown in the circle and explained by the summary of quantitative and qualitative data above. The box below indicates the priorities for action of patients, family caregivers, and the nursing staff (e.g., ‘keep it under control’)
The stable phase: “Ambivalence”
The stable period was characterized by an interval in which all parties focused on maintaining clinical and situational equilibrium. During this phase, both symptom severity and unaddressed patient requirements were significantly lower than in any other phase of the trajectory (MIDOS S, Bonferroni: $p < 0.001$; POS S, Bonferroni: $p < 0.001$). Furthermore, patients exhibited a significantly higher degree of physical independence than those categorized in the deteriorating or terminal stages (Barthel; Bonferroni: $p = 0.008$ and $p < 0.001$). Despite this stability, navigating the unpredictable nature of future disease progression generated psychological distress, fear, hopelessness, and intense anxiety for both patients and their families. One patient articulated this liminal experience:
Certain days present challenges that cannot be ignored. It feels as though you are suspended between two distinct realms—no longer truly belonging to the living, yet not belonging to the dead either. (interview 9, patient, pos. 29)
Concurrently, however, families also experienced feelings of reassurance, expectation, and optimism. This stemmed from the fact that physical symptoms and the overarching medical situation were successfully managed, and the current care framework effectively met family expectations. Both patients and relatives expressed a strong desire to maintain a sense of “normalcy” and “everyday humanity.” For some, this desire manifested as a deliberate choice to defer discussions surrounding end-of-life planning, mortality, and the dying process. Conversely, other participants actively sought out advance care planning options. From the perspective of specialized palliative care teams, the absence of immediate clinical crises creates a crucial window for deeper communication. This makes the stable phase uniquely valuable for establishing a therapeutic relationship and anticipating future transitions. Nevertheless, because there were few pressing logistical or medical emergencies, patients and informal caregivers had minimal to no contact with the specialized nursing team during this period. Consequently, clinicians dedicated significantly less time to counseling services during this phase than during the unstable, deteriorating, or terminal stages (Resource Use Questionnaire, KLV-a; Bonferroni: $p = 0.001$, $p = 0.002$, and $p = 0.019$).
The unstable phase: “Anxiety and uncertainty”
Functional capacity remained highly preserved during this period of care (Barthel, M: 16.33, SD: 5.27). Although quantitative indicators demonstrated that overall symptom distress and unaddressed needs mirrored the high levels seen in the deteriorating or terminal phases, they were significantly elevated when contrasted with the stable phase (MIDOS S, Bonferroni: $p < 0.001$; POS S, Bonferroni: $p < 0.001$). Qualitative insights indicated that the sudden emergence of acute, overwhelming symptoms frequently triggered this instability, which was accompanied by severe restlessness and profound anxiety. Both patients and their relatives were forced to confront the stark reality of a poor prognosis, which functioned as a painful reality check. This confrontation frequently resulted in deep existential and psychological suffering:
These clinical situations can provoke a profound sense of despair or even an explicit expression of a desire for death. Individuals frequently remark that the circumstances have become unmanageable for everyone involved, a reaction rooted in their total powerlessness. During this period, spiritual dilemmas surface—issues that previously held no significance for them. (focus group 2, pos. 83)
Informal caregivers grappled with extensive caregiving responsibilities and were forced to make complex, urgent choices under pressure:
I was informed that my mother is experiencing symptoms of cognitive decline, but I cannot share this information with my father, as it would cause him severe emotional distress. At the same time, my application for a caregiver allowance for him was denied because his condition is not sufficiently severe. This has left me in a permanent dispute with administrative authorities. I feel completely abandoned, with no external assistance or resource allocation available. I am reaching my physical limits, yet I continue to handle all these responsibilities without compensation, which has led to the loss of my employment and financial independence. (interview 2, family caregiver, pos. 16)
Clinical interventions during this phase were primarily reactive rather than preventive, with the overarching objective of crisis de-escalation. Acute hospital admissions frequently occurred as an emergency measure to secure immediate safety. Following these events, however, several caregivers reflected that the specialized community palliative nursing team could have successfully stabilized the crisis at home, restored a sense of security, and prevented the need for hospitalization. While the total volume of nursing care hours was higher than in the stable phase, the difference did not achieve statistical significance. Conversely, the specific time dedicated to family counseling was significantly greater in this phase than in the stable stage (Resource Use Questionnaire, KLV-a, Bonferroni: $p = 0.001$). No significant differences in service hours were observed between the unstable phase and the deteriorating or terminal phases.
The deteriorating phase: “the tangible end of life”
During this period, all individuals involved witnessed the patient’s visible physical decline. Even when patients temporarily reverted to a stable condition, both patients and their informal caregivers became profoundly aware of the approaching end of life. Frequently, multiple symptoms escalated concurrently. Quantitative indicators for functional dependence, symptom distress, and unaddressed needs did not exhibit statistically significant variations from those observed in the unstable or terminal phases; however, they were significantly elevated compared to the stable phase (MIDOS S, Bonferroni, $p < 0.001$; POS S, Bonferroni, $p < 0.001$; Barthel, Bonferroni: $p = 0.008$). A subset of patients or informal caregivers remained unable to acknowledge the reality of the impending death, resulting in requests for continued active medical interventions. These treatments were frequently deemed clinically inappropriate by healthcare professionals when balancing potential burdens against therapeutic benefits. Such discrepancies proved highly distressing for individuals who had already recognized and accepted the physical decline. Conversely, clinical situations tended to stabilize when all parties involved reached a shared awareness of the unavoidable outcome (focus group 2, pos. 119). This shared understanding allowed the care team to address anticipatory grief and facilitate end-of-life reconciliation through structured advance care planning dialogues:
At times, a distinct pattern of physical decline occurs, giving rise to an undeniable clarity that can be exceptionally painful to confront. In these moments, our role shifts to active listening and observation to discern the patient’s current priorities alongside the family’s immediate concerns. These situations represent some of our most profound clinical challenges, in which our primary contribution may be to bear the emotional weight while offering a supportive, continuous presence (focus group 1, pos. 124).
At this stage, the administrative, logistical, or communicative requirements of informal caregivers occasionally overshadowed the patient’s immediate needs. Being left alone with a severely ill relative without the capacity to alleviate their suffering was described as an intensely distressing and overwhelming experience. Nevertheless, the clinical team operated on highly familiar ground during this phase, which allowed them to maintain situational control through minor adjustments, such as educating family members on the appropriate administration of prescribed as-needed medications. While total direct service hours did not differ significantly from those in any other phase, the time allocated strictly to counseling interventions was significantly greater than that recorded during the stable phase (Resource Use Questionnaire, KLV-a, Bonferroni: $p = 0.002$).
The terminal phase: “clarity”
The imminence of death became unambiguous to all participants during the terminal phase. At this juncture, clinical interactions shifted heavily toward acknowledging the immediacy of mortality and guiding the patient and family caregivers through the dying process. This environment also facilitated the resolution of final, unspoken interpersonal matters. In their interactions with the dying individual, caregivers reoriented their focus toward core priorities, emphasizing personal presence and restricting clinical interventions exclusively to those offering direct comfort to the patient:
In many respects, this represents a profound and meaningful stage of care. The collective trajectory becomes unified, and the ultimate destination becomes clear, effectively dissipating the preceding restlessness. The pressure of outstanding obligations dissolves, creating an invaluable window for relatives to experience and share these final moments (focus group 1, pos. 146).
Our final opportunity for meaningful verbal communication occurred roughly 24 hours before her passing. During this interaction, she explicitly requested that I remain by her side overnight, expressing fear and uncertainty regarding the unfamiliar transition she was about to undergo (interview 7, family caregiver, pos. 46).
Patients frequently experienced a loss of consciousness during this stage. Consequently, functional independence reached its lowest point during the terminal phase, demonstrating statistically significant reductions compared with both the stable and unstable phases (Barthel; Bonferroni, $p < 0.001$ and $p < 0.001$). Measures of symptom burden and unaddressed requirements remained significantly elevated compared to the stable phase (MIDOS S, Bonferroni: $p < 0.001$, POS S, Bonferroni: $p < 0.001$). However, they did not differ significantly from the other advanced phases. While certain patients exhibited greater tranquility, others manifested heightened restlessness and agitation, which amplified the distress of informal caregivers and occasionally precipitated acute hospital admissions.
The terminal phase was further characterized by an intensified clinical focus on the family members providing care. Certain relatives only at this point recognized the true extent of the prolonged stress and physical exhaustion they had been enduring, noting that they had completely exhausted their personal reserves. Furthermore, they articulated clear requirements for targeted information on the physiological signs of the active dying process, along with guidance on the administrative protocols following a death.
While the total volume of service time exceeded that of the stable, unstable, and deteriorating phases, the directional differences did not reach statistical significance.
The bereavement phase: “finality”
In the immediate aftermath of the patient’s death, surviving family members were predominantly occupied with executing various urgent administrative duties. As a consequence, the immediate impact of the loss was initially obscured by these practical demands. However, the reality of the absence became the central focus as the bereavement period advanced. Informal caregivers routinely reported profound loneliness and found themselves directly confronting the logistical and emotional void within their daily routines:
I feel completely isolated now, as though I have lost my entire foundational support. I have no familiarity with managing tasks like tax returns, which my mother always handled on my behalf. I am suddenly struck by the realization that I can no longer call her to seek her counsel or perspective on daily matters. (interview 18, family caregiver, pos. 89).
For a subset of informal caregivers, the concluding debriefing session with the specialized community palliative care team provided a valuable venue to process and discuss their recent caregiving experiences. Conversely, other relatives expressed a desire to establish closure regarding the preceding weeks and months; these individuals actively sought a change of environment and preferred not to revisit the emotionally taxing caregiving period. Caregivers also demonstrated marked physical and psychological depletion, exhibiting clear manifestations of exhaustion. Within this context, the necessity for ongoing professional support structures became highly apparent:
My physician explicitly informed me that I required a dedicated period of rest to recuperate and rebuild my strength, noting that I was entirely depleted. When you are constantly waking up throughout the night and rushing back and forth under intense pressure, you operate on autopilot. Eventually, my body collapsed from the strain; I experienced overwhelming fatigue where I was incapable of doing anything other than sleeping continuously, to the point where I could have fallen asleep standing up. (interview 6, family caregiver, pos. 25).
Our thematic mapping identified distinct central concepts and operational priorities for every individual ‘Phase of Illness’: “ambivalence” oriented toward the objective to “keep it under control” (stable), “anxiety and uncertainty” targeted at “de-escalation” (unstable), “the tangible end of life” focused on “Enduring” (deteriorating), “clarity” directed toward “focusing on essentials” (terminal), and “finality” aimed at “finding a conclusion” (bereavement).
Among the most clinically critical insights from this research is the pronounced and frequently overlooked psychosocial fragility experienced by both patients and their relative caregivers during the stable phase. In this context, psychological fragility is closely intertwined with ambivalence, as both concepts reflect the complex psychological state of patients and informal caregivers during a period of clinical stability. As ambivalence highlights the internal friction between opposing emotional states—such as optimism and despair—vulnerability in this stage stems from a cognitive oscillation between the present moment and future anticipation, balancing active living with the progression of the disease. This unaddressed psychosocial vulnerability underscores the utility of hope as an essential mechanism for patients and families to regulate conflicting emotional states, rendering it a vital strategy for navigating an intricate psychological landscape [32]. In a systematic review of the dynamics of hope in palliative populations, Velić et al. demonstrate that patients view hope as an indispensable part of daily life. While physical symptoms remain reasonably controlled, individuals prioritize maximizing immediate life satisfaction while sustaining personally meaningful structural roles. By leaning into hope, families aim to reinforce interpersonal connections among affected relatives [32]. This dynamic may clarify why both patients and families frequently avoid discussing psychosocially distressing symptoms, even during clinical encounters with healthcare staff.
Nevertheless, managing psychosocial and spiritual distress necessitates transparent, open communication channels between clinicians, patients, and their informal support networks. Within the current investigation, nursing professionals observed that the stable phase offered an invaluable opportunity for deep dialogue and therapeutic relationship-building, owing to the absence of immediate medical crises. However, our findings indicate that informal caregivers in particular had virtually no integration with specialized community palliative services during this stable interval. A potential systemic explanation from a clinical standpoint is that management strategies may overemphasize the patient’s physical symptomatology and functional needs, thereby ignoring the concurrent requirements of relatives or missing a critical window for early family integration. Instead, psychosocial and spiritual dimensions must be systematically incorporated when appraising the overall appropriateness of an established management plan [33].
In stark contrast to the ambivalent equilibrium of the stable phase, the unstable phase was characterized by acute panic and profound insecurity. The protective hope previously maintained was replaced by a sense of futility. This clinical instability necessitated intensified monitoring by medical professionals, frequently requiring acute hospital admission to restore clinical baseline equilibrium. These observations emphasize the vital importance of leveraging stable periods to proactively prepare for unstable intervals, which were typically managed through reactive interventions and characterized by highly constrained decision-making under intense time pressure.
Throughout the deteriorating phase, an increased requirement for clinical counseling emerged. Crucially, surviving relatives found the visible approach of mortality uniquely challenging to tolerate, experiencing profound helplessness as passive observers. Linderholm and Friedrichsen observed that a tenuous professional relationship with community palliative clinicians can amplify a relative’s sense of powerlessness [34]. Such psychological distress can also be accompanied by intense guilt regarding perceived caregiving inadequacies [35], which may inadvertently drive demands for non-beneficial, aggressive clinical interventions [36]. Laryionava et al. emphasized the critical obligation of clinicians to implement a family-centered approach to curtail the deployment of resource-intensive, distressing, and futile medical procedures [37]. Furthermore, pursuing treatments that offer no realistic clinical benefit to the patient can significantly exacerbate moral distress among nursing staff [38].
An additional notable outcome was that surviving families maintained minimal contact with specialized home-based palliative care teams throughout the bereavement phase, suggesting that the lack of engagement during the stable phase persisted into the post-death period. This pattern may be attributable to several distinct factors. First, there is an absence of formal statutory reimbursement for specialized community palliative care interventions following a patient’s demise, which prevents the delivery of standardized post-death care. Furthermore, ongoing institutional support was not universally desired by all families; certain relatives actively sought absolute closure and consciously avoided subsequent clinical contact, whereas others experienced severe cumulative stress that culminated in acute physical and psychological breakdowns. These insights underscore the heterogeneous nature of the grieving process, indicating that community palliative services should design more individualized, longitudinal follow-up protocols and proactively refer families to external bereavement organizations to more effectively address diverse family needs during this stage [39].
Utilizing a mixed-methods methodology provided a comprehensive, multidimensional understanding of phase-specific distress among patients and informal caregivers. However, an inherent limitation of this approach involved the conceptual complexity of synthesizing and interpreting data derived from disparate sources, particularly when quantitative metrics and qualitative narratives yielded conflicting or divergent trends. To mitigate this analytical challenge, joint displays were used to visually align and contrast the qualitative and quantitative datasets, thereby facilitating the systematic identification of overarching patterns and empirical discrepancies. Regular interpretive deliberations among the primary research team, incorporating both qualitative and quantitative methodology experts, further refined data integration and ensured a comprehensive interpretation of the findings.
By using a single-point cross-sectional assessment, the study aimed to minimize the burden on participants. Nonetheless, adopting a longitudinal framework would have yielded a more nuanced understanding of the clinical transitions that characterize the ‘Phase of Illness’ model. To establish the feasibility of a longitudinal design, the selected assessment instruments must be systematically integrated into the routine, daily operational infrastructure of specialized community palliative care. In this regard, the adoption of a unified clinical ecosystem—one that seamlessly integrates outcome tracking, clinical charting, digital assessments, real-time visualization for multidisciplinary team meetings, quality benchmarking, and continuous data aggregation for research—should be prioritized [9].
In contrast to the qualitative interview recruitment process, enrolling participants for the quantitative data gathering track proved highly challenging. Operational feedback from nursing staff indicated that the profound vulnerability of patients and families acted as a significant impediment to recruitment. These observations align with prior literature demonstrating that compliance with patient-reported outcome measures drops significantly during advanced, highly intensive stages of care [12, 40]. Regarding the MIDOS and POS instruments, the perspectives of patients, informal caregivers, and nursing professionals demonstrated high concordance. This consistency indicates that “Patient-centered Outcome Measures [41]” represent a viable methodology for obtaining robust data in clinical environments where primary data collection can otherwise impose a severe participant burden.
Finally, a pragmatic decision was made to restrict the study cohort exclusively to oncological patients, reflecting the reality that the vast majority of individuals referred to specialized community palliative care carry a cancer diagnosis. Nevertheless, subsequent investigations should evaluate other life-limiting pathologies to enhance empirical inclusivity.
Conclusion
The insights generated by this study underscore the profound vulnerability and multi-faceted nature of the challenges and requirements experienced by cancer patients and their families navigating community-based palliative care across all clinical phases. However, relatives were rarely connected with the specialized home-based palliative care infrastructure during the stable phase—even when managing high-intensity caregiving responsibilities. Consequently, even when an established care plan is deemed appropriate for addressing immediate physical symptoms, problems, and needs, clinicians must maintain heightened vigilance during this phase to detect subtle shifts in the functional and psychosocial health of both patients and their informal caregivers. Regarding the bereavement phase, it is imperative not only to develop professional competencies and specialized care models within community palliative care frameworks but also to establish sustainable funding mechanisms to ensure ongoing care for heavily burdened informal caregivers. Maintaining contact throughout the bereavement period provides specialized community palliative teams with a critical window to identify individuals requiring supplementary community interventions (such as grief support groups). Specialized community palliative teams thus serve an essential gatekeeping function in this setting. Additionally, further empirical research examining the phase-specific distress profiles and clinical needs of non-oncological patient populations and their primary caregivers is urgently required.
Acknowledgments: A special ‘thank you’ goes to the participating patients and their family caregivers, who shared their intimate stories with us at a time of great vulnerability. The authors would also like to thank all members of the participating specialist palliative home care teams for their effort during data collection and Dr. Diana Staudacher for editing the manuscript.
Conflict of interest: None
Financial support: We received financial support from the Ebnet Foundation and the Zurich Price for Health Services Research.
Ethics statement: The Cantonal Ethics Committee Zurich clarified that the research project did not fall within the scope of the Human Research Act (BASEC 2019-01487). We treated the collected data confidentially and ensured anonymity, data protection, and the right to privacy. The study adhered to the principles of the Declaration of Helsinki.