Providing support for bereaved individuals is a central element of palliative care. Yet, research in this field is hindered by variability in outcome measures, which makes it difficult to compare the effectiveness of different support programs and service models. Core Outcome Sets (COS) define a standardized set of outcomes that should be assessed in studies of particular services or health conditions. This study aimed to develop a COS for evaluating adult bereavement support in palliative care, drawing on the perspectives of relevant stakeholders. A preliminary set of potential outcomes was compiled through a systematic review of quantitative and qualitative studies on bereavement support. An expert workshop with 21 stakeholders was conducted to discuss which outcomes were most critical and to evaluate and refine the literature-derived list. Insights from this workshop informed a two-round international DELPHI survey involving 240 participants, designed to establish consensus on essential outcomes and dimensions. Subsequently, a consensus meeting with 23 participants was held to rank and validate the prioritization of outcomes, followed by a final feedback session to confirm the selection. Two outcomes were ultimately identified as core: ‘Grief coping ability’ and ‘Mental well-being and quality of life’. In addition, 21 dimensions were defined to assess these outcomes in detail. Coping-related dimensions were grouped into five categories: overwhelming or negative grief, communication and connectedness, understanding and meaning-making, balancing grief with ongoing life, and access to appropriate support. Dimensions pertaining to mental well-being and quality of life were categorized as participation in work or daily activities, social and relational functioning, positive mental states, and negative emotional states. This COS offers a structured framework for both research and practice in bereavement care, supporting consistent evaluation while incorporating resilience- and public health-oriented approaches. Future work will focus on developing specific measures aligned with this COS, facilitating standardized assessment and enabling comparison across bereavement services and interventions.
Introduction
Grief is a natural process that most individuals navigate with the help of their social networks; however, some people require structured professional support to manage their bereavement [1, 2]. Bereavement is associated with increased risks to mental health, physical morbidity, and mortality [2–5], and services providing targeted support can play a crucial role in mitigating these risks [2]. Beyond individual health impacts, bereavement also carries substantial socio-economic consequences that affect multiple sectors of society [6–8]. Within palliative and end-of-life care, bereavement support is considered a key component, and varying levels of provision are recommended to meet the diverse needs of bereaved individuals [1, 2, 9–11].
A public health perspective and guidelines from the UK National Institute for Health and Care Excellence (NICE) [10, 12, 13] propose a three-tiered model of bereavement support, with services delivered according to the intensity of need:
Despite these frameworks, the evidence supporting different levels of bereavement support remains limited. Systematic reviews and meta-analyses often report inconclusive outcomes or weak effects [4, 14–16], although some evidence suggests interventions may be more effective for individuals experiencing severe or complicated grief [4, 16]. Nonetheless, these findings sometimes conflict with the practical experience of clinicians, who observe meaningful benefits from bereavement interventions, as also highlighted in qualitative and mixed-method evaluations [14, 15].
A key challenge identified in multiple reviews is inconsistent outcome measurement [4, 14, 17–19]. For instance, a review of family caregivers’ end-of-life and bereavement experiences identified 89 distinct instruments, nearly half of which were study-specific and lacked psychometric validation [19]. Variation in outcomes has also been noted in meta-analyses of interventions targeting complicated grief [4], as well as in broader reviews of bereavement support in palliative and cancer care contexts [14, 17, 18]. Some experts argue that null findings in intervention studies may stem from measuring inappropriate or overly simplistic outcomes, such as general psychiatric symptom checklists or global functioning scales, which do not capture the specific dimensions of bereavement [15]. These inconsistencies hinder the ability to synthesize evidence across studies and limit the strength of conclusions needed to guide clinical practice and service delivery [14, 17, 18, 20].
Recent national and international initiatives have sought to establish consensus on service standards for bereavement support through expert stakeholder engagement [10, 21] (https://www.eapcnet.eu/eapc-groups/task-forces/bereavement). While defining what constitutes a quality service is valuable, understanding the outcomes these services aim to achieve is equally critical for evaluating their effectiveness.
To address these challenges, Core Outcome Sets (COS) have been increasingly used in healthcare research. A COS represents a standardized, minimum set of outcomes that should be measured and reported in all trials for a specific condition, based on stakeholder consensus regarding what is essential to assess (www.comet-initiative.org). Implementing COS can enhance consistency across studies, reduce heterogeneity, facilitate meta-analysis, and limit reporting bias [22]. Engaging diverse stakeholders ensures that relevant and meaningful outcomes are captured [22]. In response to the gaps in bereavement research, the present study sought to develop a COS specifically for palliative care contexts, focusing on interventions and services for adults who have lost an adult relative to terminal illness.
Materials and Methods
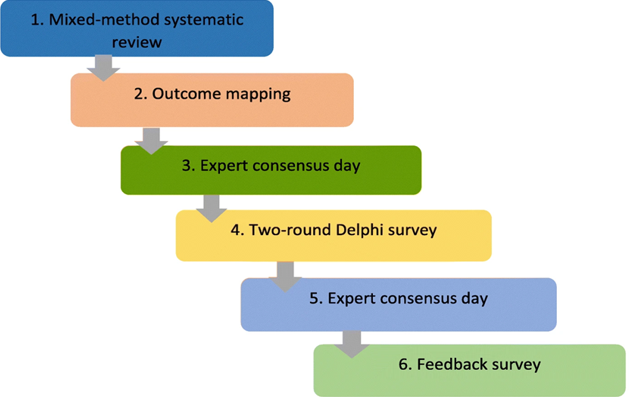
Several approaches exist for developing a Core Outcome Set (COS), with systematic or literature reviews and Delphi techniques increasingly favored in recent years [20, 23]. In this study, the COS was established by integrating data from a systematic review, insights from two expert consensus meetings, and a modified two-round Delphi survey. This multi-step process was designed to achieve stakeholder agreement on which outcomes and dimensions should be considered essential or “core” (Figure 1).
|
|
|
Figure 1. COS methodology used in study |
Systematic review and outcome mapping
A mixed-methods systematic review was conducted to identify outcomes and outcome measures used in bereavement support interventions for adults who had lost someone to terminal illness. Searches were carried out in Medline, Embase, PsycINFO, and CINAHL, using combinations of bereavement/grief-related terms and terms related to palliative care, advanced illness, and caregiving. Studies were eligible if they evaluated bereavement interventions or services for adults bereaved through terminal illness, were conducted in Western countries, and published in English from 1996 onwards. Two independent reviewers screened titles, abstracts, and full texts to identify relevant studies. The full review protocol, including search strategies, is registered on Prospero (CRD42016043530, www.crd.york.ac.uk/prospero).
A supplementary search of the same databases was performed to identify systematic reviews of adult bereavement interventions and measurement tools used in bereavement research and practice. This step ensured inclusion of outcomes and measures that may not have been reported in palliative care-specific interventions.
From the included studies, an Excel spreadsheet was created to catalogue all outcomes reported in quantitative evaluations of bereavement support. Two researchers (EH and SS) independently reviewed the outcomes to cluster similar items, define single terms for overlapping outcomes, and organize them into broader domains. Disagreements or uncertainties were resolved through discussion with the wider research team. Information on the psychometric properties of each measure was collected, and similar dimensions were grouped and standardized using the same process. Additional outcomes and dimensions identified through supplementary searches or recommended by previous studies were also included.
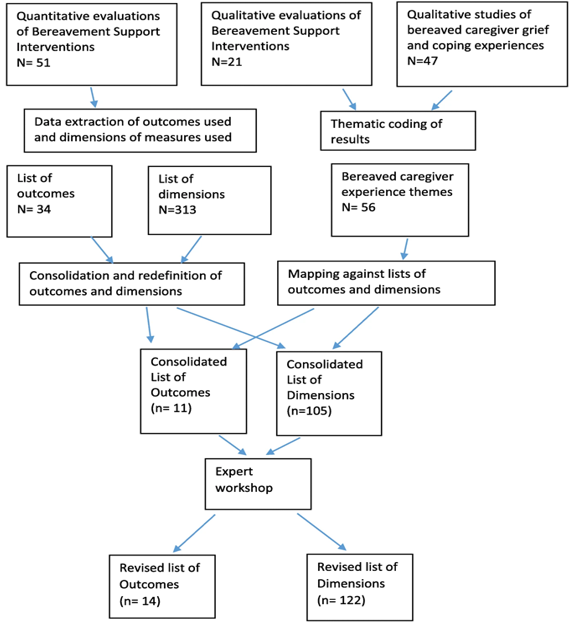
Data from qualitative evaluation studies were also examined. Extracted findings on interventional impacts and caregiver grief and coping experiences were organized thematically to generate potential outcome dimensions. These were then mapped against the quantitative outcome lists, highlighting matches and identifying new dimensions as needed. This process resulted in a total of 11 outcomes and 105 associated outcome dimensions.
Expert workshop
To ensure all relevant outcomes and dimensions were captured, a stakeholder workshop was convened with 21 UK-based participants, including professionals and non-professionals from diverse backgrounds. Participants were recruited through bereavement provider networks, patient and public involvement (PPI) networks, professional contacts, and snowball recommendations (Table 1).
The workshop included breakout sessions: two groups of professionals and one group of individuals with caregiving and bereavement experience. In the first session, participants were asked to identify and categorize outcomes and dimensions they considered important for evaluating bereavement support services. In the second session, each group reviewed the outcomes compiled from the systematic review and compared them with their own suggestions, discussing and critiquing the lists. Following these discussions, the outcome lists were revised, and additional items were incorporated based on stakeholder input (Figure 2).
|
|
|
Figure 2. Flow diagram of outcome mapping process |
Delphi survey
A modified two-round Delphi survey was employed to gather stakeholder perspectives on the outcomes and dimensions considered most essential for inclusion in the COS. The Delphi technique is a structured, iterative approach in which a panel of experts completes multiple rounds of questionnaires to achieve consensus on specific items [24, 25].
The survey items were derived from the outcomes identified in the systematic review and refined through the consensus workshop. These lists were further mapped, consolidated, and piloted with a mixed group of 23 stakeholders prior to the main survey. Both paper and online versions of the questionnaire were created.
In Round One, participants rated the importance of each outcome and outcome dimension for inclusion in the COS using a 5-point Likert scale, ranging from “not important” to “very important.” The first round remained open for 34 weeks, while Round Two was open for 4 weeks. Invitations to participate were sent to the corresponding authors of studies included in the systematic review and to attendees of the first consensus day. Participants were encouraged to share the survey within their professional networks, and social media was used to further promote participation. To enhance service user engagement, all UK Marie Curie Hospices were invited to recruit current bereavement service users. Hospice bereavement research leads identified appropriate staff and service users, provided information about the study, and distributed questionnaires along with participant information sheets.
Responses collected online were exported into SPSS, while paper questionnaires were manually entered. Participants were classified into four stakeholder groups: service users, service providers, members of the public, and researchers. Members of the public included adults who had experienced bereavement but had no prior engagement with formal bereavement support services. Consensus was defined as at least 70% agreement within each stakeholder group, with particular priority given to service users’ responses. An item was considered to have reached consensus in Round One if at least 70% of both the total sample and service users rated it as either “important/very important” or “not important/slightly important.”
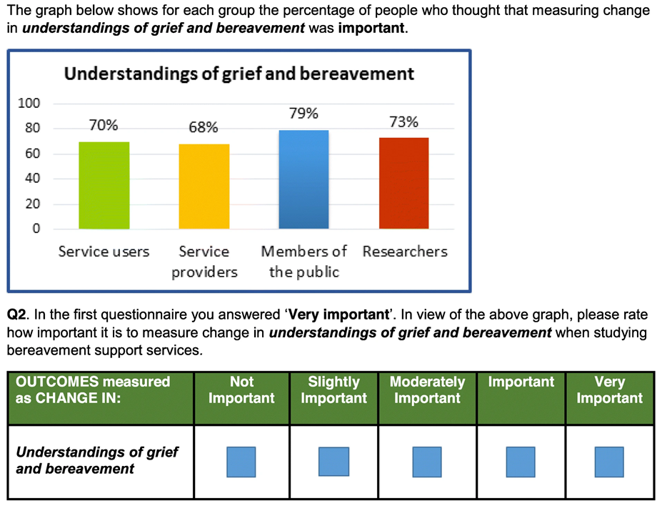
In Round Two, participants re-evaluated items that had not reached consensus in the first round. Each question included visual feedback showing the percentage of agreement across stakeholder groups, the participant’s prior response, and a request to indicate their current preferences again (Figure 3).
|
|
|
Figure 3. Example question used for Delphi – round 2 |
Final consensus day
In April 2018, a final consensus meeting was convened to finalize and validate the selection of outcomes derived from the Delphi survey. Attendees were presented with organized lists of outcomes and corresponding dimensions. To reduce participant fatigue, each question included a maximum of seven items, and participants could allocate up to three votes depending on prior survey scores. Using electronic voting, participants indicated which items they deemed most critical. After each voting round, results from the survey and the votes were displayed and discussed collectively, allowing participants to reflect on similarities and differences.
During a second session, the shortlisted outcomes and dimensions were reviewed. Participants were asked to confirm agreement with the selections and suggest any additional items they felt were missing. Due to time limitations, this stage could not be fully completed. To address this, the outcomes and dimensions were circulated to all participants after the event, providing an opportunity for further feedback on the emerging COS.
Mapping and feedback exercise
The Delphi rounds and consensus day voting demonstrated strong agreement for the highest-ranking outcomes, clearly identifying the primary core outcome. To validate and refine potential additional core outcomes, a mapping exercise was undertaken to link the top-scoring outcome dimensions back to their respective outcomes. Most dimensions corresponded with the top three outcomes, although significant overlap between dimensions for the second and third outcomes suggested a need to prioritize one over the other.
A feedback survey was then sent to all consensus day participants, summarizing the Delphi and voting results and highlighting areas of convergence and divergence. Respondents were asked to indicate preferences for the uncertain second outcome and to flag any excluded dimensions they believed should be reinstated. Dimensions scoring below 80% in both the overall and service-user-specific samples were initially excluded. A dimension could only be re-included if at least 80% of feedback survey respondents supported it; items with support below this threshold were marked as “unresolved” for consideration in future studies.
Patient and public involvement (PPI)
Two Public Contributors (PCs) were closely involved throughout the project. One acted as a co-applicant on the funding application, while the other joined at the study’s inception. Their involvement was integrated across all stages, from planning and protocol development to the design of study materials and outputs. The PCs ensured that the methods and documentation were suitable for participants, particularly bereaved carers, and helped make all materials accessible, including information sheets, Delphi surveys, and consensus day resources.
The PCs actively participated in the outcome mapping process, attended management group meetings, and co-facilitated discussions during the first consensus day. Reflective logs maintained by both researchers and PCs were used to monitor progress, assess adherence to the protocol, and evaluate the impact of PPI contributions on the study outcomes.
Results and Discussion
Participant characteristics
Recruitment occurred between 3 March 2017 and 13 April 2018. Table 1 provides a detailed overview of the stakeholders involved across the different stages of the study, including service users, providers, members of the public, and researchers.
Table 1. Participants recruited at each stage of the study.
|
Groups |
First Consensus Day |
Delphi One |
Delphi Two |
Second Consensus Day |
Feedback Survey |
|
Bereaved People |
7 |
69 |
30 |
8 |
7 |
|
Service Providers |
11 |
119 |
49 |
8 |
3 |
|
Academic/Researchers |
3 |
33 |
18 |
3 |
1 |
|
Members of the Public |
|
19 |
11 |
4 |
|
|
Total |
21 |
240 |
108 |
23 |
11 |
Outcome extraction and mapping
The findings from the outcome mapping exercise are summarized in Table 2, showing the frequency of each descriptor outcome as assigned by the research team, alongside the frequency of each outcome as originally reported in the quantitative studies included in the exercise. A total of 105 outcome dimensions were identified at this stage.
First expert workshop
Discussions during the first expert workshop generated two overarching themes. The first focused on identifying the key areas that bereavement services should address when supporting service users. The second explored the implications of these focus areas for defining measurable outcomes that could be used to evaluate the effectiveness of bereavement interventions.
Table 2. List of outcomes used in previous studies.
|
escriptor Outcomes (Reported Verbatim Outcomes) |
Overall Frequency |
|
Anxiety and Depression |
49 |
|
Anxiety (13), Depression (19), Anxiety and Depression (2), Mental Stress (1), Distress (9), Symptom Distress (3), Mental Health (2) |
|
|
Grief |
27 |
|
Grief (22), Complicated Grief (2), Blame (1), Despair (1), Knowledge of Death and Bereavement (1) |
|
|
Post-Traumatic Stress |
9 |
|
Avoidance/Intrusion (6), Post-Traumatic Stress (3) |
|
|
Quality of Life and Wellbeing |
8 |
|
Quality of Life (3), Spiritual Wellbeing (1), Hopelessness (2), Hope (1), Balance (1) |
|
|
Coping |
5 |
|
Coping and Adaptation (1), Coping (2), Religious Coping (2) |
|
|
Self-Esteem |
5 |
|
Self-Esteem (5) |
|
|
Mood/Affect |
4 |
|
Mood/Affect (4) |
|
|
Social Functioning and Adjustment |
6 |
|
Social Adjustment (1), Social Functioning (2), Marital Strain (1), Interpersonal Problems (2) |
|
|
Physical Health |
3 |
|
Health (1), Physical Health (1), Physical Functioning (1) |
|
|
Locus of Control |
2 |
|
Locus of Control (2) |
|
|
Interpersonal and Social Support |
2 |
|
Social Support (1), Interpersonal Relations (1) |
|
Managing and coping with grief
Coping with grief
Across all three stakeholder groups, discussions emphasized that bereavement services should focus on helping individuals manage and navigate their grief, rather than attempting to “treat” it. Consequently, participants preferred framing outcomes in terms of coping rather than grief itself. Key points included:
Social adjustment, relationships, and wellbeing
Participants also highlighted outcomes related to social and personal adjustment, relationships, and overall wellbeing, with a focus on support-related results. Key points included:
Following these discussions, the original outcome lists derived from the systematic review were updated to reflect participants’ feedback.
Two-round delphi survey
From the initial stages of the project, 17 outcomes and 51 outcome dimensions were identified. For ease of completion, dimensions were organized under broader themes of emotional issues, wellbeing, health, and support.
A total of 240 participants completed the first Delphi round. Table 3 summarizes their characteristics. Missing data were minimal: four respondents did not report age, education, or ethnicity, and two additional participants omitted ethnicity information.
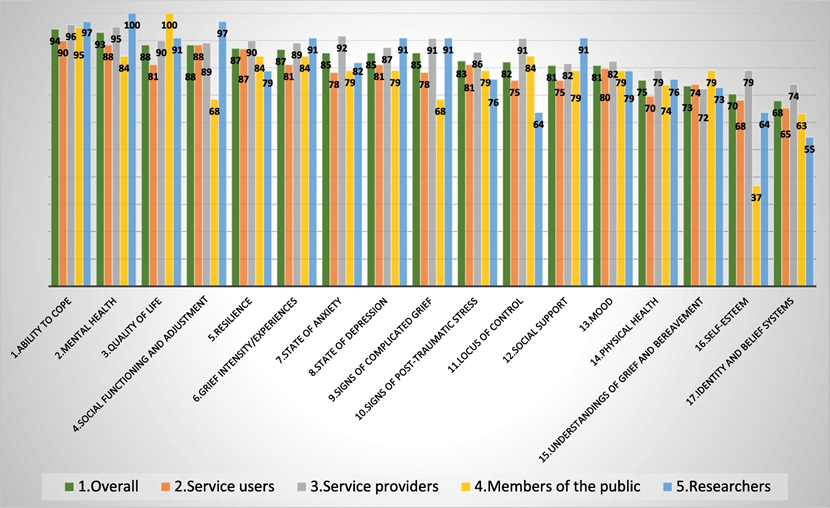
The first-round results are shown in Figure 4, with bar graphs displaying the proportion of each stakeholder group agreeing on the importance of each outcome, alongside the overall cohort score. Two outcomes—self-esteem and identity, and belief systems—failed to reach the 70% agreement threshold. Additionally, 17 of the 51 outcome dimensions did not achieve consensus. These 19 items were included in the second Delphi round. No outcomes were rated as unimportant or slightly important (Figure 4).
|
|
|
Figure 4. Delphi Round 1: percentages of respondents who thought the outcomes important or very important |
After completing the second round of the Delphi survey, the two outcomes in question—‘self-esteem’ and ‘identity and belief system’—each achieved an overall agreement score of 62%. Notably, the degree of consensus across stakeholder groups remained largely consistent between the first and second rounds for most outcomes.
Table 3. Socio-demographic characteristics of participants for Delphi round 1.
|
|
All participants |
Service users |
|
N (%) |
N (%) |
|
|
Age |
||
|
18 to 24 |
2 (0.8) |
1(1.6) |
|
25 to 34 |
16 (6.8) |
1(1.6) |
|
35 to 44 |
35 (14.9) |
7(11.0) |
|
45 to 54 |
67 (28.5) |
14(21.9) |
|
55 to 64 |
77 (32.8) |
20(31.2) |
|
65 to 74 |
27 (11.5) |
12(18.7) |
|
75 to 79 |
6 (2.6) |
6(9.3) |
|
80 to 84 |
5 (2.1) |
3(4.7) |
|
Gender |
||
|
Male |
59 (25.1) |
17(24.6) |
|
Female |
174 (74.0) |
51(73.9) |
|
Prefer not to say |
1(0.4) |
1(1.4) |
|
Ethnicity |
||
|
White |
217(92.3) |
60(93.7) |
|
Mixed |
3(1.3) |
1(1.5) |
|
Asian or Asian British |
6(2.5) |
1(1.5) |
|
Black/African/Caribbean/Black British |
5(2.1) |
2(3.1) |
|
Prefer not to say |
2(0.8) |
– |
|
Highest qualification |
||
|
No qualifications |
5(2.1) |
5(7.7) |
|
Trade apprenticeship |
3(1.3) |
2(3.1) |
|
1 or more O level/GCSE’s (at grades A-C) |
12(5.1) |
7(10.8) |
|
1 or more A levels |
10(4.2) |
2(3.1) |
|
ONC/OND/ City & Guilds |
7(3.0) |
2(3.1) |
|
HNC/HND |
8(3.4) |
3(4.6) |
|
University First Degree (e.g. BA, BSc) |
44(18.7) |
15(23.1) |
|
Postgraduate Degree (e.g. MA, MSc, PhD) |
90(38.2) |
16(24.6) |
|
Postgraduate Qualification (e.g. certificate or diploma) |
49(20.8) |
7(10.8) |
|
Other |
7(3.0) |
6(9.2) |
Table 4 lists the 51 outcome dimensions. For each of them it is indicated if it reached 70% or 80% agreement in the Delphi survey.
Table 4. Agreement reached for the outcome dimensions following rounds 1 and 2 of the Delphi survey and consensus day voting.
|
Emotional Issues |
70% |
80% |
Shortlisted Consensus Day |
Wellbeing |
70% |
80% |
Shortlisted Consensus Day |
Health |
70% |
80% |
Shortlisted Consensus Day |
Support |
70% |
80% |
Shortlisted Consensus Day |
|
Feelings of loneliness and emptiness |
✓ |
✓ |
✓ |
Ability to participate in worka |
✓ |
✓ |
- |
Anxiety (feelings of tension, nervousness, panic, distress) |
✓ |
✓ |
✓ |
Relationships with friends and family |
✓ |
✓ |
- |
|
Preoccupation with thoughts of the deceased person |
✓ |
✓ |
- |
Ability to participate in social or other activities |
✓ |
✓ |
✓ |
Depression (sense of hopelessness, pessimism, periods of crying) |
✓ |
✓ |
✓ |
Relationships with health and social care professional(s) |
X |
X |
- |
|
Avoidance of reminders of the deceased person |
X |
X |
- |
Ability to perform daily tasks |
✓ |
✓ |
- |
Related physical symptoms (e.g., pain or sickness) |
✓ |
- |
- |
Finding comfort, meaning, or strength in religious or spiritual beliefs |
X |
X |
- |
|
Avoidance and denial of distress, grief, or other problems |
✓ |
- |
✓ |
Involvement in home management and housework |
X |
X |
- |
Problems with memory, concentration, making decisions, speech |
✓ |
- |
✓ |
Accessing practical support if needed |
✓ |
✓ |
✓ |
|
Intensity of grief experienced around time of death |
✓ |
- |
✓ |
Financial security and material wellbeing |
✓ |
- |
- |
Suicidal thoughts |
✓ |
✓ |
- |
Accessing financial/material support if neededb |
✓ |
✓ |
- |
|
Overwhelming thoughts and/or nightmares about loss |
✓ |
✓ |
- |
Ability to function as part of a family |
✓ |
✓ |
- |
Irritation and bad mood |
✓ |
- |
- |
Accessing emotional support if needed |
✓ |
✓ |
- |
|
Hallucinations about the deceased person |
X |
X |
- |
Sense of identity and role |
✓ |
- |
✓ |
Sleep-related problems |
✓ |
- |
- |
Ability to express feelings openly and honestly |
✓ |
✓ |
- |
|
Feelings of shame and/or stigma |
X |
X |
- |
Sense of meaning and purpose in life |
✓ |
✓ |
✓ |
Tiredness and fatigueb |
✓ |
✓ |
- |
Accessing guidance if needed |
✓ |
- |
- |
|
Feelings of detachment and distancing |
✓ |
- |
- |
Optimism and hopefulness |
✓ |
✓ |
- |
Hyperactivity and inability to slow downc |
✓ |
- |
- |
Feeling understood by and connected with other bereaved peopleb |
✓ |
✓ |
✓ |
|
Feelings of blame, guilt, anger, bitterness, regret |
✓ |
✓ |
- |
Satisfaction with home, neighbourhood, and community environment |
X |
X |
- |
Paranoia or obsessive thoughtsc |
✓ |
X |
- |
|
|
|
|
|
|
|
|
|
Acceptance of grief experiences as normal |
✓ |
✓ |
✓ |
Symptoms of phobias |
X |
X |
- |
|
|
|
|
|
|
|
|
|
Acceptance of loss |
✓ |
✓ |
- |
Behaviours such as eating disorders or substance abuse |
✓ |
- |
- |
|
|
|
|
|
|
|
|
|
Understanding and finding meaning of loss |
✓ |
✓ |
- |
Self-esteem |
✓ |
- |
- |
|
|
|
|
|
|
|
|
|
Positive reminiscence and remembering of the deceaseda |
✓ |
✓ |
✓ |
General health problems (e.g., infections, blood pressure, loss of sex drive, other illness)b |
✓ |
✓ |
- |
|
|
|
|
|
|
|
|
|
Regulation and control of feelings and behaviours |
✓ |
- |
✓ |
Use of health care services |
X |
X |
✓ |
|
|
|
|
|
|
|
|
|
Ability to find balance and channel grief |
✓ |
✓ |
✓ |
|
|
|
|
|
|
|
|
|
|
|
|
|
Ability to take control (e.g., look ahead and start to move forward with life) |
✓ |
✓ |
✓ |
|
|
|
|
|
|
|
|
aMet 80% threshold in service user sub-group in Delphi 1
bMet 80% threshold in service user sub-group in Delphi 2. These items also needed to have been selected on consensus day or final feedback survey to be included
cExceeded 70% in second round of the Delphi survey (service user sub-group)
Second consensus day results
The second consensus day centered on a series of electronic voting sessions, allowing participants to individually indicate their priorities and collectively discuss areas of agreement or divergence with the Delphi survey findings. Overall, the voting results closely aligned with the Delphi survey outcomes. Table 5 presents the six highest-ranked outcomes from the voting exercises alongside the top six outcomes from the Delphi survey, illustrating a strong consistency between the two methods. The corresponding shortlisted outcome dimensions from the voting exercises are detailed in Table 4.
Table 5. Highest scoring outcomes from Consensus Day and Delphi Survey.
|
Consensus Day Outcomes |
Delphi Survey Outcomes |
|
Quality of Life |
Ability to Cope |
|
Ability to Cope |
Mental Health |
|
Resilience |
Quality of life |
|
Social Support |
Social functioning and adjustment |
|
Grief intensity/experiences |
Resilience |
|
Mental Health |
Grief intensity/experiences |
Mapping exercise: linking outcomes and dimensions
The mapping exercise reconnected outcome dimensions that achieved over 80% agreement in the Delphi survey with their corresponding outcomes to guide and validate outcome selection. This analysis revealed that nearly all the high-agreement dimensions corresponded to the top three outcomes identified in the Delphi survey. While the first core outcome, “Ability to cope,” was clearly indicated, there was notable overlap between the second and third outcomes—“Mental health” and “Quality of life”—driven by the large number of selected wellbeing-related dimensions. This overlap highlighted the need to choose between these two outcomes and prompted a wellbeing-focused definition of “Mental health.” Given the grief-specific nature of many coping-related items, the first outcome was redefined as “Ability to cope with grief,” allowing incorporation of several selected grief-related items.
Feedback exercise results
The feedback survey aimed primarily to clarify consensus day delegates’ preferences for the second core outcome and to identify any outcome dimensions initially proposed for exclusion that should be retained. Eleven delegates responded, though one provided only general agreement without answering specific questions. Among respondents, six favored “Quality of life” (four bereaved participants, one service provider, one researcher), three preferred “Mental health and wellbeing” (two bereaved participants, one service provider), and one suggested a combined “Quality of life and wellbeing” outcome. Considering these mixed preferences, the qualitative reasoning provided in comments, and the convergence of wellbeing-related dimensions, the second outcome was ultimately defined as “Quality of life and mental wellbeing.”
No new outcome dimensions were added following the feedback survey. However, five dimensions were classified as “unresolved” (50–79% agreement) according to the pre-specified criteria: sense of identity and role; difficulties with memory, concentration, decision-making, or speech; accessing financial or material support if needed; fatigue; and general health problems (e.g., infections, blood pressure). These items may merit further exploration in future research.
Core outcomes and dimensions
The finalized core outcomes and their associated dimensions are presented in Table 6. For clarity, the dimensions have been organized into nine thematic categories.
Table 6. Core Outcomes with Dimensions.
|
bility to Cope with Grief |
Quality of Life and Mental Wellbeing |
|
Negative and Overwhelming Grief |
Participation in Work and/or Other Regular Activities |
|
- Feelings of loneliness and emptiness |
- Ability to perform daily tasks |
|
- Feelings of blame, guilt, anger, bitterness, regret |
- Ability to participate in work |
|
- Overwhelming thoughts and/or nightmares about loss |
- Ability to participate in social activities |
|
- Preoccupation with thoughts of the deceased |
|
|
Communication and Connectedness |
Relationships and Social Functioning |
|
- Ability to express feelings openly and honestly |
- Ability to function as part of a family |
|
- Feeling understood by and connected with other bereaved people |
- Relationships with friends and family |
|
Understanding, Accepting, and Finding Meaning in Grief |
Positive Mental Wellbeing |
|
- Acceptance of grief experiences as normal |
- Sense of meaning and purpose in life |
|
- Understanding, acceptance, finding meaning in loss |
- Optimism and hopefulness |
|
- Positive reminiscence and remembering of the deceased |
|
|
Finding Balance Between Grief and Life Going Forwards |
Negative Mental & Emotional State |
|
- Ability to find balance and channel grief |
- Anxiety (feelings of tension, nervousness, panic, and distress) |
|
- Ability to take control/look ahead and start to move forward with life |
- Depression (sense of hopelessness, pessimism, periods of crying) |
|
|
- Suicidal thoughts |
|
Accessing Appropriate Support |
|
|
- Accessing emotional support if needed |
|
|
- Accessing practical support if needed |
|
Through a comprehensive process of outcome identification, mapping, and engagement with stakeholders, this study has established two core outcomes and their associated dimensions that can guide both the design and evaluation of adult bereavement support within palliative care. The outcomes—“Ability to cope with grief” and “Quality of life and mental wellbeing”—provide a standardized framework for researchers and practitioners while offering a conceptual shift away from the predominantly medicalized or pathological approaches in existing literature, aligning more closely with public health and resilience-focused perspectives on bereavement care [12, 13]. The implications for service evaluation, research, and program design are discussed below.
The initial outcome mapping exercise highlighted the need for a standardized set of outcomes to assess adult bereavement interventions. The identification of 34 differently described outcomes, along with numerous measurement instruments, reinforces previous observations regarding the inconsistent outcome reporting in bereavement research [4, 14, 15, 17–19]. By establishing the two core outcomes—“Ability to cope with grief” and “Quality of life and mental wellbeing”—this work represents an important step toward more consistent and meaningful measurement in this field. These outcomes complement recently developed consensus-based service standards [11, 21] and those currently under development (https://www.eapcnet.eu/eapc-groups/task-forces/bereavement).
The selected outcomes reflect a conceptual approach that prioritizes coping, support, and wellbeing rather than pathology. They align with public health and resilience-based models that emphasize the role of social networks and a balanced provision of community-based and specialist interventions [12, 13]. Stakeholder workshops explicitly supported a shift toward outcomes focused on coping, support, and quality of life. The divergence between commonly reported research outcomes (e.g., Grief, Depression, Anxiety) and the outcomes favored by consensus day and Delphi participants (Coping, Wellbeing, Quality of Life, Mental Health, Social Support) further underscores the need for this approach. While elements of grief, depression, and anxiety are included within the two core outcomes, the overarching orientation is positive, capturing both individual and social dimensions of resilience and wellbeing during bereavement. Improvements in some dimensions may reflect direct effects of interventions (e.g., “Communication and connectedness”), while others may represent indirect benefits indicative of overall enhanced wellbeing (e.g., “Participation in work or regular activities”).
Several factors may account for the shift away from disease-focused outcomes. First, the mapping exercises included numerous RCTs of grief therapy, where researchers may prefer pathological outcomes. In contrast, the consensus exercises drew participants from a wider stakeholder base—including service users, providers, and researchers from diverse methodological backgrounds—reflecting the broader scope of palliative care bereavement support rather than grief therapy alone. This highlights the importance of inclusive stakeholder participation in developing Core Outcome Sets.
Moreover, the Delphi survey, voting exercises, and expert discussions revealed that many prioritized outcomes and dimensions originated from qualitative literature or stakeholder discussions and were only marginally represented in prior quantitative evaluations. This suggests that inconsistencies in outcomes and potentially inappropriate selection of outcome measures may partly explain the inconclusive or limited positive results frequently reported in bereavement intervention trials [4, 14–16]. Recent mixed-method reviews also note that although RCT evidence shows limited positive effects, qualitative and mixed-method evaluations consistently identify beneficial impacts, many of which are now captured in the present Core Outcome Set—for example, “facilitating loss and grief resolution,” “restoration and moving on,” “acquisition of coping strategies,” and “social support” [14]. This reinforces the value of integrating qualitative evidence with stakeholder input to ensure that outcomes relevant to service users are included in evaluation protocols.
Limitations, strengths, and implications for future research
A key challenge in this study was the potential variability in how participants interpreted and responded to survey items. To address this, several mitigation strategies were implemented, including open discussions during consensus days, extensive pilot testing of the survey, and active involvement of patient and public contributors (PPI) throughout the research process. The strong alignment between findings from both consensus days and the Delphi survey, as well as the consistency in the prioritization of outcomes and their dimensions, lends further confidence in the validity of the results. Another strength of this study is the relatively high participation of bereaved individuals and service users, ensuring that the core outcomes reflect the perspectives of those most directly affected by bereavement support. Nonetheless, some self-selection bias is likely, and groups with lower socio-economic status or minority ethnic backgrounds were underrepresented in the sample.
The next phase of this work involves identifying, adapting, or developing assessment tools that specifically capture the two core outcomes. An initial “best-fit” review of existing validated instruments revealed that none fully covered the selected outcomes but highlighted measures with potential for adaptation. Grief-specific tools linked to coping, resilience, and meaning-making frameworks—such as the Inventory for Daily Widowed Life [26], Adult Attitude to Grief Scale [27], and Grief and Meaning Reconstruction Inventory [28]—show promise. Additionally, generic quality of life and wellbeing instruments, including the Multicultural Quality of Life Index [29] and the Warwick-Edinburgh Mental Wellbeing Scale [30], captured several relevant dimensions. Further work is required to conduct updated literature searches, perform rigorous content analysis, quality appraisal, and stakeholder consultation following COMET and COSMIN guidance [31, 32]. This will support robust recommendations regarding existing measures suitable for this core outcome set and identify areas where new tool development or validation is needed. Given the recognized challenges of conducting research on complex interventions [33] and in palliative care and bereavement contexts specifically [34, 35], consideration is also being given to how tools can be designed to support a variety of evaluation approaches for both clinical practice and research purposes [36].
Conclusion
This study has established two core outcomes—“Ability to cope with grief” and “Quality of life and mental wellbeing”—along with their associated dimensions, providing a standardized framework to guide the design and evaluation of adult bereavement support in palliative care. By incorporating the perspectives of key stakeholders, this work offers a consistent and meaningful alternative to the predominantly medicalized and pathological outcomes commonly reported in quantitative literature. Future research will focus on developing and refining measurement tools aligned with this core outcome set, enabling improved comparability of bereavement services and interventions across clinical and research settings.
Acknowledgments: None
Conflict of interest: None
Financial support: None
Ethics statement: None