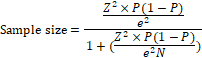Clinical placements are fundamental to the development of nursing students’ professional competence; however, these experiences often present significant challenges and can be a major source of stress. While stress is widely recognized as both a trigger and an exacerbating factor for poor health, limited research has explored how general health status itself influences perceived stress levels. This study aimed to identify factors associated with perceived stress during clinical practice among nursing students, with particular emphasis on the relationship between stress and general health status. A cross-sectional quantitative design was employed, involving 724 associate degree nursing students from Southern Taiwan. Participants’ health status scores ranged from 28 to 139, with a mean score of 68.40 (SD = 25.75). Based on score classifications, 35.5% of students reported good health (28–55), 24.6% moderate health (56–83), and 39.9% poor health (≥84). Perceived stress scores ranged from 0 to 95, with an average of 36.65 (SD = 15.95). Classification and regression tree (CART) analysis identified health status as the most influential factor associated with perceived stress (Normalized Importance = 100%). Students with General Health Questionnaire (GHQ-28) scores ≤34.5 reported mild stress, those with scores between >34.5 and <84.5 experienced moderate stress, and scores ≥84.5 marked the threshold for severe stress levels. The results suggest that general health status may serve as an effective indicator for identifying nursing students who are at higher risk of experiencing elevated stress during clinical practice. However, due to the cross-sectional nature of the study and the reciprocal relationship between health and stress, further longitudinal research is needed to clarify the causal pathways linking health status and stress vulnerability.
Introduction
Clinical placements are fundamental to nursing education, providing students with the opportunity to develop clinical competence and apply theoretical knowledge in real-world healthcare settings. Through these placements, students gain hands-on experience in patient care, strengthen their sense of professional identity, and enhance communication, teamwork, and confidence in their nursing roles [1, 2]. The first clinical placement, in particular, represents a critical milestone in a nursing student’s academic and professional development.
Although the value of clinical practice is well recognized, these experiences are also widely acknowledged as being demanding and stressful [3–5]. For many students, clinical placements do not always meet expectations, and the transition from classroom learning to real patient care can be overwhelming [6]. The shift from student to practitioner often involves emotional and cognitive challenges, ranging from discomfort and self-doubt to what has been described as “reality shock” — characterized by anxiety, discouragement, and fatigue [5, 7–9].
Common stressors include difficulty integrating theory with practice, fear of making clinical errors, uncertainty in applying professional knowledge, limited confidence in technical skills, communication challenges with patients, families, and healthcare teams, lack of trust from patients, time pressure, and managing acute clinical situations [10–15].
Such stressors can lead to significant physical and psychological symptoms, including headaches, anxiety, restlessness, sleep disturbances, impaired concentration, cognitive decline, and reduced learning efficiency. Persistent stress during placements can negatively affect students’ clinical performance and may even discourage them from pursuing nursing careers after graduation [11, 13, 16–22].
Personal characteristics also play an important role in shaping how students experience and manage stress. Factors such as low self-esteem, poor self-confidence, indecisiveness, limited self-control, a tendency toward self-blame, and inadequate social skills have all been associated with greater stress vulnerability among students [23-26]. According to the stress vulnerability model, environmental stressors can exacerbate an individual’s underlying biological or psychological susceptibility to ill health [27]. Previous research in general populations suggests that stress can act as both a precipitating and aggravating factor for illness [28, 29]. Moreover, stress and health appear to share a bidirectional relationship: high stress levels may impair general health, while poor health status may heighten sensitivity to stress. Despite this theoretical understanding, few studies have specifically examined how general health status influences perceived stress levels, particularly in nursing students during clinical placements.
In Taiwan, clinical placement constitutes a major component of the nursing curriculum and is designed to equip students with the essential competencies required for professional registration. To qualify as registered nurses, students must complete a minimum of 1,016 hours of clinical training in teaching hospitals accredited by the Ministry of Examination [30]. Typically, students undertake rotational placements across various departments during their final year, gaining exposure to diverse clinical environments. These experiences have been shown to enhance students’ professional growth, clarify their understanding of the nursing role, and strengthen both cognitive and technical skills [31].
However, previous studies in Taiwan have also identified high stress levels among nursing students during clinical training. For instance, research examining the relationship between stress and psychosocial well-being among nursing students found that the primary sources of stress were a lack of professional knowledge and skill, with social and behavioral symptoms being common responses [32]. Another cross-sectional study involving 357 diploma nursing students identified higher stress levels, female gender, and introverted personality traits as significant predictors of psychosocial symptoms during clinical practice [33]. Despite these findings, the specific influence of students’ general health status on their perceived stress levels during clinical placements has not been well explored.
To support nursing students in managing stress effectively and completing their clinical education successfully, it is essential to gain a deeper understanding of the factors contributing to stress during clinical training, especially within distinct cultural and educational contexts. Therefore, this study aimed to examine the factors associated with perceived stress among nursing students in Taiwan, with a particular focus on the role of general health status as a potential determinant of stress during clinical placement.
Materials and Methods
Study design
A quantitative, cross-sectional approach was employed to investigate the factors associated with perceived stress among nursing students undertaking clinical practice. The study was carried out at a nursing institution in southern Taiwan that offers a five-year associate degree program in nursing.
Participants and sampling
The study population consisted of senior students enrolled in the final two years of the associate nursing program, during which they participate in extensive clinical training placements lasting either six months or one year. Participants were selected through a convenience sampling technique.
Students were eligible to participate if they met the following criteria: they were in their fourth or fifth year of study; had no diagnosed serious physical or psychological illnesses; and were not experiencing major family difficulties during the clinical internship period, as confirmed by their supervising clinical instructor.
According to statistics provided by the Ministry of Education’s Basic Information of Schools at All Levels [34], a total of 1,939 students were registered at the institution in 2019. The required sample size for this study was computed using the formula recommended by [35], ensuring sufficient statistical power for analysis.
|
|
(1) |
Sample size estimation
The sample size for this study was calculated using several assumptions: the probability of students performing well or poorly in clinical practice was set at 0.5, the sampling error was 0.03, and the confidence level was 95%. The 3% margin of error aligns with accepted standards in educational and social science research for continuous data [36, 37]. This margin ensures that the true population mean on a seven-point scale is estimated to fall within ±0.21 of the sample mean. Based on these parameters, the minimum required sample size was 689. Allowing for a potential 10% nonresponse rate, the final sample size was adjusted to 758 participants.
Instruments
Data were collected using two validated self-report instruments: the Perceived Stress Scale for Nursing Students in Clinical Practice (PSS-NC) and the Chinese version of the General Health Questionnaire (GHQ-28). The PSS-NC, developed by Sheu et al. [38], is a 29-item measure designed to assess the intensity and sources of stress experienced by nursing students in Taiwan during clinical practice. The scale evaluates stress related to patient care, interactions with instructors and clinical staff, academic and clinical workload, relationships with peers, demonstration of professional knowledge and skills, and the overall clinical environment. Each item is rated on a five-point Likert scale ranging from 0 (“never”) to 4 (“always”), with higher scores indicating greater perceived stress. The instrument has demonstrated strong reliability and validity in previous studies [38].
The GHQ-28 [39, 40] was used to assess participants’ general physical and psychological health over the preceding month. This self-administered questionnaire, originally derived from the GHQ-60 through exploratory factor analysis, consists of 28 items divided into four subscales measuring somatic symptoms, anxiety and insomnia, social dysfunction, and severe depression. Respondents rate each item on a five-point Likert scale from 1 (“never”) to 5 (“much more than usual”), with higher scores reflecting poorer health. The Chinese translation of the GHQ-28 has been validated across multiple populations, demonstrating stable factor structures and cultural applicability [41–43]. Total scores were classified into three categories to indicate overall health status: scores of 28–55 were considered good health, 56–83 as moderate health, and scores ≥84 as indicative of poor health.
Data collection
Following institutional approval and ethical clearance, the lead researcher and two trained research assistants approached eligible students individually during their clinical placements. The study purpose, procedures, and ethical considerations were explained in detail, and each student was provided with an information sheet. Interested students received a consent form along with a prepaid envelope for returning the signed form. Upon receipt of consent, the research team distributed the self-administered questionnaires, which included the PSS-NC and GHQ-28, along with envelopes for secure return. Students completed the questionnaires in a quiet, interruption-free setting, requiring approximately one hour.
Participants were informed of their right to withdraw from the study at any time without consequence to their placement or academic standing. They were also told they could request deletion of their data up to a specified date, after which analysis would commence. No participants requested data removal. As a small token of appreciation, participants were offered fluorescent markers for their time and effort.
Ethical considerations
Ethical approval for this study was granted by the Ethics Committee of National Cheng Kung University (NCKU HREC-E-105-113-2). Prior to participation, the study’s objectives, procedures, and requirements were thoroughly explained to potential participants. Those who expressed interest received a detailed cover letter outlining the study and their role in it. Participants were assured that all information collected would remain confidential and that their responses would be anonymized. They were also informed of their right to decline participation or withdraw from the study at any point without any consequences for their academic standing or clinical placement.
Statistical analysis
All statistical analyses were performed using IBM SPSS for Windows, version 23.0 (IBM Corp., Armonk, NY). Continuous variables were summarized as means and standard deviations, and normality assumptions were confirmed. Pearson’s correlation coefficients were calculated to examine associations between variables, with significance set at p < 0.05. Group comparisons were conducted using multifactor analysis of variance (ANOVA).
To explore the influence of variables such as general health status, internship category, academic year, gender, and daily sleep duration on perceived stress, a Classification and Regression Tree (CART) analysis was performed. CART is a widely used exploratory technique that identifies key predictors, uncovers data structure, and produces a decision tree model [44]. The CART procedure involved three steps: initially, a decision tree was generated using the full training dataset; next, the tree was pruned and optimized based on parameters including maximum depth, minimum sample size per leaf, and minimum node impurity, to ensure the model achieved optimal generalizability; finally, the test dataset was applied to the trained model for prediction [45]. Specifically, the analysis was carried out by constructing a classification model from the full sample, setting the minimum parent node size at 100 and the child node size at 50, followed by evaluating classification accuracy using ten-fold cross-validation. Post-pruning was applied using the maximum risk difference criterion, set to zero, to generate the final tree with minimal risk. Decision nodes indicated points where choices were made, with branches representing mutually exclusive and collectively exhaustive alternatives [46–48].
Results and Discussion
Demographic characteristics
Out of 790 distributed questionnaires, 724 were returned completed, yielding a response rate of 91.6%. The participants were predominantly female (96.7%), with a mean age of 19.13 years (SD ± 0.42). Most students (79.4%) were in the final year of the program. Regarding sleep patterns, 57.6% reported sleeping six to eight hours per night, whereas 40.9% reported less than five hours of sleep per night. Clinical practice placements were distributed across Medical-Surgical Nursing (13.54%), Obstetrics Nursing (16.16%), Pediatric Nursing (18.23%), Psychiatric Nursing (19.47%), Community Nursing (19.06%), and Long-Term Care (13.54%). The majority of students (79.42%) had completed six months of internship at the time of data collection, while 20.58% had completed two to four months.
Table 1. Demographic data (N = 724)
|
Variable |
Category |
n |
% |
|
Gender |
|||
|
Male |
24 |
3.3 |
|
|
Female |
700 |
96.7 |
|
|
Practice grade |
|||
|
Fourth grade |
149 |
20.6 |
|
|
Fifth grade |
575 |
79.4 |
|
|
Sleep duration (hours) |
|||
|
9–10 |
11 |
1.5 |
|
|
6–8 |
417 |
57.6 |
|
|
4–5 |
288 |
39.8 |
|
|
1–3 |
8 |
1.1 |
|
|
Practice area |
|||
|
Medical-Surgical Nursing Practicum |
98 |
13.5 |
|
|
Obstetrics Nursing Practicum |
117 |
16.2 |
|
|
Pediatric Nursing Practicum |
132 |
18.2 |
|
|
Psychiatric Nursing Practicum |
141 |
19.5 |
|
|
Community Nursing Practicum |
138 |
19.1 |
|
|
Long-Term Care Practicum |
98 |
13.5 |
|
|
Duration of clinical practice (months) |
|||
|
2–4 |
149 |
20.6 |
|
|
6 |
575 |
79.4 |
Values are presented as number (n) and percentage (%). Percentages may not sum to 100.0 due to rounding.
Health status of nursing students
Participants’ overall health status scores ranged from 28 to 139, with higher scores reflecting poorer health. The mean score was 68.40 (SD = 25.75). Among the specific domains, the highest levels of distress were observed in anxiety and insomnia (Mean = 24.97, SD ± 4.35) and social dysfunction (Mean = 24.31, SD ± 3.26) (Table 2).
When categorized according to overall scores, 35.5% of students (n = 257) were classified as having good health (scores 28–55), 24.6% (n = 178) as moderate health (scores 56–83), and 39.9% (n = 289) as poor health (scores ≥84). Items most frequently associated with poor health included dissatisfaction with task performance (Mean = 2.89, SD ± 1.14), difficulty in feeling capable of making decisions (Mean = 2.86, SD ± 1.14), challenges in keeping oneself busy and engaged (Mean = 2.41, SD ± 1.09), and a sense of being overwhelmed by responsibilities (Mean = 2.77, SD ± 1.21) (Table 3).
Table 2. Students’ health status scores on individual domains
|
Domain |
Good (28–55) n = 257 (35.5%) |
Moderate (56–83) n = 178 (24.6%) |
Poor (≥ 84) n = 289 (39.9%) |
Overall N = 724 |
||||
|
M ± SD |
Range |
M ± SD |
Range |
M ± SD |
Range |
M ± SD |
Range |
|
|
Somatic symptoms |
10.11 ± 3.36 |
7–22 |
18.33 ± 4.32 |
7–34 |
23.57 ± 3.86 |
16–67 |
17.45 ± 6.74 |
7–35 |
|
Anxiety & insomnia |
9.69 ± 3.42 |
7–23 |
19.80 ± 4.42 |
7–30 |
24.97 ± 4.35 |
19–68 |
18.24 ± 7.60 |
7–35 |
|
Social dysfunction |
11.05 ± 4.13 |
7–23 |
19.76 ± 4.23 |
9–45 |
24.31 ± 3.26 |
15–35 |
18.47 ± 6.87 |
7–35 |
|
Severe depression |
7.77 ± 2.24 |
7–21 |
12.44 ± 5.16 |
7–25 |
20.93 ± 4.35 |
8–35 |
14.17 ± 7.03 |
7–35 |
Table 3. Students’ health status scores on individual items
|
Health Status Factor / Item |
M |
SD |
Range |
Item Ranking |
Factor Ranking |
|
I. Somatic symptoms |
17.45 |
6.74 |
7–35 |
— |
3 |
|
1. Been feeling perfectly well and in good health? |
2.71 |
1.09 |
1–5 |
7 |
|
|
2. Been feeling in need of a good tonic? |
2.35 |
1.19 |
1–5 |
19 |
|
|
3. Been feeling run down and out of sorts? |
2.49 |
1.16 |
1–5 |
12 |
|
|
4. Been feeling that you are ill? |
2.71 |
1.15 |
1–5 |
6 |
|
|
5. Been getting any pains in your head? |
2.46 |
1.17 |
1–5 |
16 |
|
|
6. Been getting a feeling of tightness or pressure in your head? |
2.60 |
1.22 |
1–5 |
11 |
|
|
7. Been having hot or cold spells? |
2.14 |
1.08 |
1–5 |
22 |
|
|
II. Anxiety and insomnia |
18.24 |
7.60 |
7–35 |
— |
2 |
|
8. Been losing much sleep over worry? |
2.48 |
1.21 |
1–5 |
14 |
|
|
9. Been having difficulty in staying asleep once you fall asleep? |
2.48 |
1.22 |
1–5 |
13 |
|
|
10. Been feeling constantly under strain? |
2.74 |
1.24 |
1–5 |
5 |
|
|
11. Been getting edgy or bad tempered? |
2.65 |
1.21 |
1–5 |
10 |
|
|
12. Been getting scared or panicky for no reason? |
2.41 |
1.19 |
1–5 |
17 |
|
|
13. Been feeling everything is getting on top of you? |
2.77 |
1.21 |
1–5 |
4 |
|
|
14. Been feeling nervous and strung-out all the time? |
2.69 |
1.25 |
1–5 |
8 |
|
|
III. Social dysfunction |
18.47 |
6.87 |
7–35 |
— |
1 |
|
15. Been managing to keep yourself busy and occupied? |
2.85 |
1.19 |
1–5 |
3 |
|
|
16. Been taking longer over the things you do? |
2.69 |
1.19 |
1–5 |
9 |
|
|
17. Been satisfied with the way you have carried out your tasks? |
2.89 |
1.14 |
1–5 |
1 |
|
|
18. Been feeling capable of making decisions about things? |
2.86 |
1.14 |
1–5 |
2 |
|
|
19. Been able to enjoy your normal day-to-day activities? |
2.48 |
1.10 |
1–5 |
15 |
|
|
20. Been managing to keep yourself busy and occupied?* |
2.41 |
1.09 |
1–5 |
18 |
|
|
21. Been taking longer over the things you do?* |
2.29 |
1.12 |
1–5 |
20 |
|
|
IV. Severe depression |
14.17 |
7.03 |
7–35 |
— |
4 |
|
22. Been thinking of yourself as a worthless person? |
2.11 |
1.11 |
1–5 |
23 |
|
|
23. Been feeling that life is entirely hopeless? |
2.10 |
1.12 |
1–5 |
24 |
|
|
24. Been feeling that life is not worth living? |
2.06 |
1.11 |
1–5 |
25 |
|
|
25. Been thinking of the possibility that you may do away with yourself? |
1.94 |
1.06 |
1–5 |
26 |
|
|
26. Been feeling at times that you could not do anything because your nerves were too bad? |
2.24 |
1.18 |
1–5 |
21 |
|
|
27. Been finding yourself wishing you were dead and away from it all? |
1.87 |
1.05 |
1–5 |
27 |
|
|
28. Been finding that the idea of taking your own life keeps coming into your mind? |
1.85 |
1.03 |
1–5 |
28 |
|
|
Overall GHQ-28 Score |
68.40 |
25.75 |
28–139 |
— |
— |
Perceived stress during clinical practice
The overall perceived stress scores among participants ranged from 0 to 95, with a mean of 36.65 (SD ± 15.95). Based on the average item scores, 26.7% of students (n = 193) experienced mild stress (mean single-item score ≈ 1), 64.5% (n = 467) reported moderate stress (mean single-item score ≈ 1.5), and 8.8% (n = 64) experienced moderate-to-severe stress (mean single-item score > 1.5) (Table 4).
Across specific domains, the highest levels of stress were observed in caring for patients, which had a mean score of 12.83 (SD ± 5.14), followed by stress related to assignments and workload (Mean = 7.62, SD ± 3.91) and stress arising from interactions with teachers and nursing staff (Mean = 5.90, SD ± 3.47) (Table 4).
Table 4. Areas of stress perceived by students – findings from ANOVA
|
Stressor Category |
Mild (Scores 0–29, n=193) |
Moderate (Scores 30–43, n=467) |
Moderate to Severe (Scores ≥44, n=64) |
Overall (n=724) |
p-value |
||||
|
Mean ± SD |
Range |
Mean ± SD |
Range |
Mean ± SD |
Range |
Mean ± SD |
Range |
||
|
Patient care responsibilities |
7.513 ± 3.823 |
0–17 |
14.015 ± 3.504 |
5–23 |
20.828 ± 4.907 |
13–48 |
12.834 ± 5.144 |
0–29 |
< .001 |
|
Instructors and nursing staff |
2.383 ± 1.837 |
0–8 |
6.539 ± 2.346 |
0–17 |
11.891 ± 3.030 |
5–19 |
5.900 ± 3.468 |
0–19 |
< .001 |
|
Coursework and workload demands |
3.469 ± 2.367 |
0–11 |
8.441 ± 2.635 |
3–19 |
14.109 ± 2.437 |
9–20 |
7.618 ± 3.908 |
0–20 |
< .001 |
|
Colleagues and personal life |
1.166 ± 1.292 |
0–6 |
3.507 ± 1.839 |
0–9 |
6.719 ± 2.746 |
0–14 |
3.165 ± 2.356 |
0–14 |
< .001 |
|
Insufficient clinical knowledge/skills |
2.187 ± 1.523 |
0–6 |
4.703 ± 1.560 |
0–15 |
7.000 ± 1.380 |
3–10 |
4.220 ± 2.033 |
0–10 |
< .001 |
|
Clinical setting conditions |
0.876 ± 1.139 |
0–4 |
3.244 ± 1.453 |
0–8 |
6.234 ± 1.892 |
2–10 |
2.877 ± 2.042 |
0–10 |
< .001 |
Key stressors in clinical practice
Students reported that the most stressful situations during clinical placements were related to direct patient care. The highest perceived stress was associated with a lack of experience and confidence in providing nursing care and making clinical judgments (Mean = 1.94, SD ± 0.89), followed by difficulties in meeting personal expectations when clinical performance fell short of self-set standards (Mean = 1.87, SD ± 0.92). Challenges in responding appropriately to questions from doctors, instructors, and patients were also notable stressors (Mean = 1.77, SD ± 0.81). Concern over academic grades contributed to stress as well, with a mean score of 1.76 (SD ± 1.08). In contrast, students reported that environmental factors and interactions with peers and daily life responsibilities caused relatively lower levels of stress (Table 5).
Table 5 Sources of stress perceived by nursing students
|
Stress Source / Item |
Mean |
SD |
Range |
Item Rank |
Category Rank |
|
I. Stress from patient care |
1 |
||||
|
Inadequate experience and judgment in nursing care (Q2) |
1.94 |
0.89 |
0–4 |
1 |
|
|
Unsure how to address patients’ physical, psychological, and social needs (Q3) |
1.74 |
0.89 |
0–4 |
5 |
|
|
Difficulty communicating effectively with patients (Q4) |
1.41 |
0.86 |
0–4 |
13 |
|
|
Fear of not gaining trust from patients or their families (Q8) |
1.47 |
0.91 |
0–4 |
11 |
|
|
Struggle transitioning from student to professional nurse role (Q9) |
1.12 |
0.85 |
0–4 |
17 |
|
|
Unable to respond adequately to questions from doctors, instructors, or patients (Q10) |
1.77 |
0.81 |
0–4 |
3 |
|
|
Frustration from gap between expected and actual clinical performance (Q11) |
1.87 |
0.92 |
0–4 |
2 |
|
|
Inability to deliver high-quality nursing care (Q12) |
1.50 |
0.76 |
0–4 |
9 |
|
|
II. Stress from instructors and clinical staff |
4 |
||||
|
Conflict between theoretical learning and clinical reality (Q1) |
1.62 |
0.89 |
0–4 |
7 |
|
|
Perception of unfair grading by instructors (Q14) |
0.73 |
0.78 |
0–4 |
26 |
|
|
Lack of empathy and support from healthcare staff (Q17) |
0.72 |
0.73 |
0–4 |
27 |
|
|
Difficulty discussing patient conditions with faculty and staff (Q18) |
1.12 |
0.85 |
0–4 |
18 |
|
|
Discrepancy between expected and received instructor guidance (Q20) |
1.04 |
0.81 |
0–4 |
19 |
|
|
Insufficient mentoring and support from instructors (Q25) |
0.68 |
0.73 |
0–4 |
28 |
|
|
III. Stress from coursework and workload |
2 |
||||
|
Anxiety over poor academic performance (Q13) |
1.76 |
1.08 |
0–4 |
4 |
|
|
Clinical demands exceed physical/emotional capacity (Q15) |
1.34 |
0.88 |
0–4 |
14 |
|
|
Pressure from the intensity and standards of clinical duties (Q16) |
1.70 |
1.09 |
0–4 |
6 |
|
|
Rigid schedule disrupts family and social life (Q19) |
1.49 |
1.05 |
0–4 |
10 |
|
|
Falling short of instructors’ performance expectations (Q22) |
1.31 |
0.88 |
0–4 |
15 |
|
|
IV. Stress from peers and personal life |
6 |
||||
|
Clinical duties limit participation in extracurriculars (Q5) |
0.84 |
1.00 |
0–4 |
24 |
|
|
Pressure from comparative performance evaluations (Q21) |
0.76 |
0.79 |
0–4 |
25 |
|
|
Difficulty forming relationships with peers (Q23) |
0.67 |
0.73 |
0–4 |
29 |
|
|
Competitive pressure from classmates in academic and clinical settings (Q24) |
0.89 |
0.81 |
0–4 |
23 |
|
|
V. Stress from lack of professional knowledge and skills |
3 |
||||
|
Unfamiliarity with patient diagnoses and treatments (Q6) |
1.42 |
0.76 |
0–4 |
12 |
|
|
Lack of knowledge in medical histories and terminology (Q7) |
1.51 |
0.82 |
0–4 |
8 |
|
|
Inadequate mastery of clinical nursing procedures (Q26) |
1.29 |
0.83 |
0–4 |
16 |
|
|
VI. Stress from the clinical environment |
5 |
||||
|
Anxiety due to sudden changes in patient status (Q27) |
0.93 |
0.72 |
0–4 |
22 |
|
|
Unfamiliarity with ward equipment and layout (Q28) |
0.95 |
0.79 |
0–4 |
21 |
|
|
General stress from the hospital practice setting (Q29) |
1.00 |
0.90 |
0–4 |
20 |
|
|
Total |
36.65 |
15.95 |
0–95 |
– |
– |
Correlation between nursing students’ health status and the level of stress
In the unadjusted linear correlation analysis, health status was strongly and positively associated with perceived stress (r = 0.665, p < 0.01), indicating that students with poorer health reported higher levels of stress (Table 6).
Table 6. Adjusted analysis of the correlation of health status with internship stress (N = 724)
|
Average |
Standard deviation |
r |
|
|
Health status |
68.40 |
25.75 |
.665* |
|
Internship stress |
36.65 |
15.95 |
* p < .01
Factors associated with perceived stress: cart analysis findings
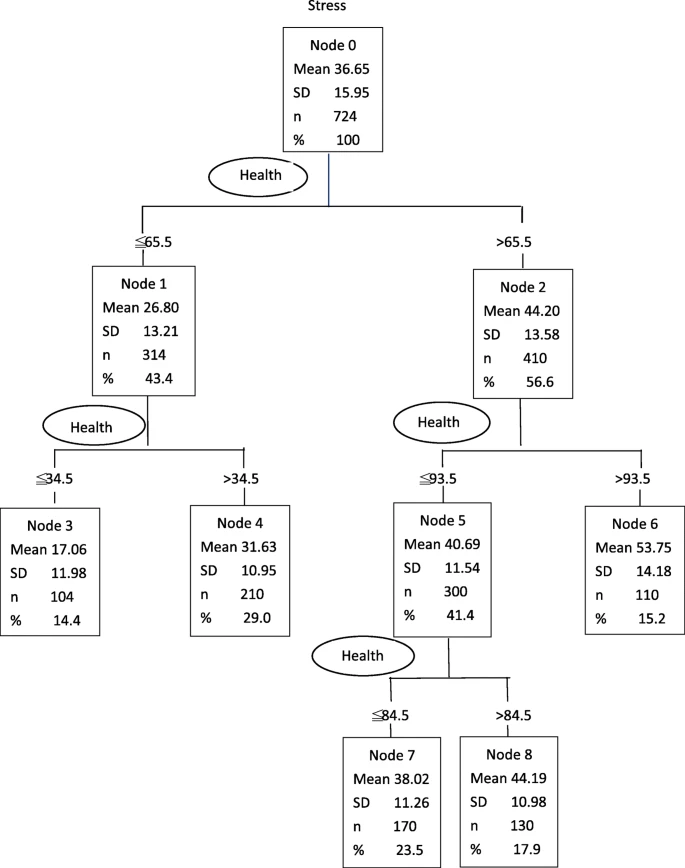
The Classification and Regression Tree (CART) analysis generated a decision tree comprising three main branches and five terminal nodes, illustrating factors related to perceived stress during clinical practice (Figure 1). The optimal model included eight nodes and five terminal nodes, structured according to the minimum Gini index improvement for perceived stress.
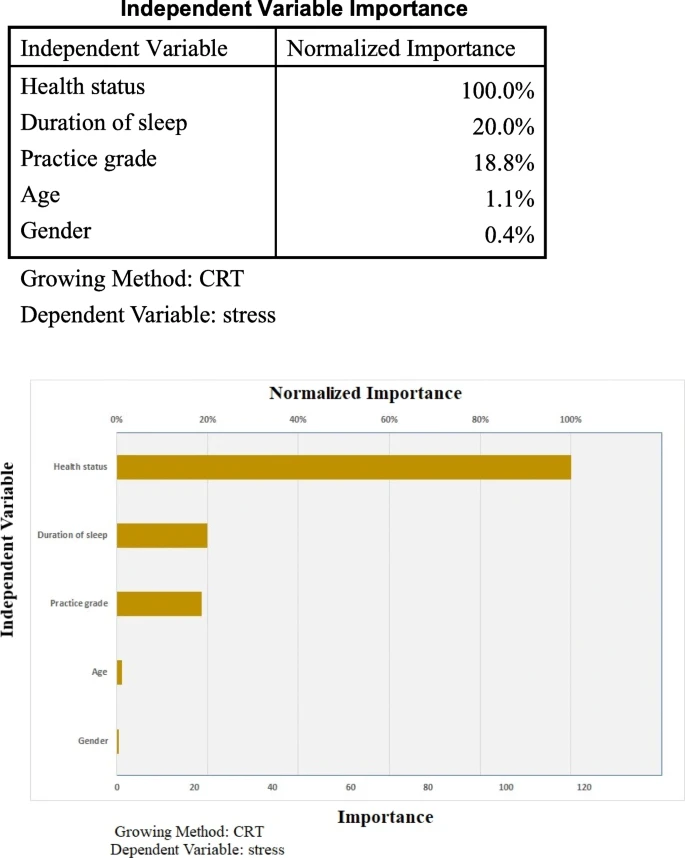
General health status emerged as the most influential predictor in the first layer of the tree, with a Normalized Importance value of 100% (Figure 2). The analysis indicated that students with a GHQ-28 score of 34.5 or lower were likely to experience mild stress, whereas those with scores between 34.5 and 84.5 were more likely to report moderate stress. A score of 84.5 represented the threshold at which perceived stress transitioned to severe levels, and students scoring above 84.5 were at risk of severe or extremely severe stress. Predicted perceived stress scores and corresponding population sizes at key nodes included: 17.06 for 104 students at node 3 (GHQ-28 < 34.5), 31.63 for 210 students at node 4 (GHQ-28 < 34.5), 38.02 for 170 students at node 7 (GHQ-28 ≤ 84.5), 44.19 for 130 students at node 8 (GHQ-28 > 84.5), and 53.75 for 110 students at node 6 (GHQ-28 > 93.5).
These results highlight general health status as the primary factor predicting the level of perceived stress among nursing students, confirming its central role in shaping students’ experiences during clinical placements.
|
|
|
Figure 1. CART analysis: Health status and the level of perceived stress |
|
|
|
Figure 2. CART analysis: Factors associated with perceived stress of clinical practice |
This study investigated the factors associated with perceived stress during clinical practice among nursing students in Taiwan, with a particular emphasis on the role of general health status. To the best of the authors’ knowledge, this is the first study to specifically examine how general health status influences the levels of stress experienced by nursing students during their clinical placements.
Over one-third of the participants in this study reported poor overall health, with the greatest difficulties observed in the domains of anxiety and insomnia, as well as social dysfunction. Students reported challenges such as dissatisfaction with task performance, difficulty in decision-making, struggles to remain occupied and engaged, and a general sense of being overwhelmed. General health is widely recognized as a crucial determinant of student success and academic performance. In the context of nursing education, students’ health during clinical placements can substantially affect their clinical performance and their ability to achieve intended learning outcomes. The well-being of nursing students is particularly important given the rigorous demands of the program and the profession, as well as its implications for the delivery of quality patient care [49].
Most students in this study experienced moderate to severe levels of stress, particularly in areas related to patient care, academic assignments and workload, and interactions with teachers and nursing staff. Previous research has consistently highlighted clinical placements as significant sources of stress for nursing students [4, 10–15, 24]. Specific stressors documented in prior studies include the gap between theoretical knowledge and practical application, feelings of unpreparedness, fear of making mistakes, apprehension around death and dying, interpersonal difficulties with instructors and clinical staff, unfamiliarity with clinical environments, and conflicts between personal professional beliefs and the realities of hospital practice [24, 50, 51]. Consistent with these findings, students in the present study identified a lack of experience and confidence in providing care and making clinical judgments, challenges in meeting self-expectations, limited knowledge in addressing patients’ physio-psycho-social needs, and concerns about grades as the predominant stressors. While some of these stressors are inherent due to the students’ limited professional experience, the results underscore the need for educators and clinical supervisors to provide stronger guidance and preparatory support to help students manage stress effectively during clinical training.
Interestingly, unlike some previous studies that have identified the clinical environment as a major stressor [24, 25, 33, 52, 53], students in this study reported that environmental factors and interactions with peers and daily life caused relatively little stress. This aligns with findings from other Taiwanese studies examining initial clinical practice experiences [32].
The most striking finding from the CART analysis was that general health status emerged as the strongest predictor of perceived stress. Students with poorer health reported higher levels of stress, highlighting the importance of assessing and supporting students’ overall well-being. Since previous studies have rarely focused on the direct relationship between health status and stress during clinical placements in Taiwan or comparable settings, these findings provide novel insight into identifying students most at risk for high stress.
Several limitations should be acknowledged. The use of convenience sampling and the recruitment of participants from a single associate degree nursing program may limit the generalizability of the findings. Additionally, the cross-sectional design restricts causal inferences between health status and stress, and the potential bidirectional relationship between these variables warrants caution in interpreting the predictive role of health status. It is unclear whether poor health predisposes students to higher stress, or whether elevated stress contributes to deteriorating health. Finally, reliance on self-reported measures may have introduced bias, potentially affecting the validity of the findings.
Conclusion
This study provides valuable insights into perceived stress during clinical practice among final-year nursing students in Taiwan, highlighting a clear association between general health status and vulnerability to stress. The findings contribute to the existing evidence by demonstrating the potential utility of the GHQ-28 as a tool for identifying students at higher risk of stress during clinical placements. Despite these insights, the cross-sectional design and the likely bidirectional relationship between health and stress limit the ability to establish a causal link, underscoring the need for further research to clarify the predictive role of health status in relation to perceived stress.
The results have significant implications for nursing educators and clinical placement supervisors in identifying and supporting students most susceptible to stress. While some stressors are inherent to clinical training, strategies aimed at promoting students’ general health and well-being—through educational, psychological, and evidence-based interventions—could enhance their resilience and coping capacity. Given that individual health is influenced by multiple internal and external factors, continuous monitoring and support throughout the course of study and clinical practice are essential.
Additionally, psychosocial support from peers and family members should be considered and incorporated into interventions aimed at mitigating stress. Future research should adopt longitudinal and experimental designs to explore the dynamic relationship between health status and stress, investigate coping strategies at different stages of clinical placement, and evaluate the feasibility of sustained intervention programs. Understanding the perspectives of educators and clinical supervisors regarding stressors is also recommended to inform comprehensive support strategies for nursing students.
Abbreviations
CART: Classification and regression tree
GHQ: General Health Questionnaire
EFA: Exploratory factor analysis
Acknowledgments: None.
Conflict of interest: None.
Financial support: None.
Ethics statement: None.