Predicting the clinical course of dementia is often challenging, which can limit the timely implementation of palliative care. This study explored how palliative care influences healthcare utilization and examined factors potentially associated with mortality among patients with advanced dementia. We included 57 residents with advanced dementia (Clinical Dementia Rating ≥ 5 or Functional Assessment Staging Test stage 7b) enrolled in a palliative care program at a long-term care facility in Taipei, Taiwan. Comparisons were made between medical service use before and after initiation of palliative care. Multivariable logistic regression was applied to identify variables linked to 6-month mortality, both prior to and following palliative care. Following the introduction of palliative care, participants had notable reductions in healthcare utilization, including outpatient visits, prescription medications, hospital admissions, and emergency department visits (all p < 0.001). While univariate analysis suggested that patients who died within six months had a slightly higher number of hospitalizations prior to receiving hospice care (p = 0.058), this association did not remain significant in multivariate models. The findings indicate that palliative care can meaningfully reduce healthcare utilization among individuals with advanced dementia. Additional studies with larger samples are needed to clarify the determinants of short-term mortality in this population.
Introduction
Dementia is a progressive neurodegenerative disorder characterized by impairments in memory, language, motor function, and balance [1, 2]. Individuals with dementia often require complex, long-term care involving multidisciplinary teams and coordination of various healthcare resources [3]. The prevalence of dementia has risen globally, affecting both Western [1, 3, 4] and Eastern populations [5], driven largely by aging demographics. This increase places a significant burden on healthcare systems and incurs substantial socioeconomic costs [6].
Since dementia is incurable and inevitably progressive, palliative care has been recognized as a suitable approach to enhance the quality of life of affected patients [7, 8]. Palliative care programs focus on individuals with advanced-stage illnesses who are at high risk of mortality, aiming to alleviate suffering and minimize unnecessary or aggressive medical interventions [9]. Historically, palliative care has been more widely implemented among cancer patients than those with dementia [1, 10]. Barriers to palliative care for dementia include limited awareness of the terminal nature of the disease among caregivers and some healthcare professionals [1, 11], the unpredictable trajectory of dementia [1, 2, 10], challenges in prognosis [10, 12], and the lack of structured policies, guidelines, or funding to support care [9, 12].
Recent data indicate a growing utilization of palliative care among dementia patients [10, 13]. For instance, in the United States, the proportion of dementia patients enrolled in palliative care increased from less than 1% in 1995 to roughly 15% by 2014 [10]. National Medicare data showed that more than half of nursing home residents receiving palliative care in 2004 and 2009 had dementia [14], with inpatient care and treatment accounting for a large share of expenditures [15]. Despite this, end-stage dementia patients often receive suboptimal palliative support compared to patients with other conditions [1, 12]. The lack of reliable prognostic indicators complicates decision-making regarding the timing of end-of-life care, resulting in a higher likelihood of aggressive interventions during periods of functional decline or acute medical events such as infections, dehydration, delirium, or falls [6, 10].
Although an increasing number of dementia patients die in nursing homes [16, 17], many still die in hospitals, reflecting ongoing overutilization of medical services and indicating that palliative care principles are not yet fully integrated into dementia care. Moreover, research on mortality risk factors among advanced dementia patients receiving palliative care remains limited [12, 18], and evidence regarding the impact of palliative care on reducing healthcare utilization is inconsistent [6]. To address these gaps, this study analyzed data from dementia patients enrolled in a nursing home-based palliative care program in Taipei, Taiwan, examining both changes in medical service utilization before and after palliative care implementation and potential predictors of 6-month mortality.
Materials and Methods
Data sources
In July 2014, a nursing home in Taipei, Taiwan, implemented a palliative care program led by the Taipei City Psychiatric Center (TCPC; Songde branch), part of Taipei City Hospital. Prior to 2014, palliative care services in Taiwan were predominantly hospital-based, with limited availability in nursing homes. The TCPC initiative, known as the TCPC-Nursing Home Palliative Care Program, integrates palliative care directly into the nursing home setting. The program is delivered by a multidisciplinary team, including board-certified neurologists, psychiatrists, psychiatric nurses, social workers, pharmacists, and clinical psychologists, in close collaboration with the nursing home staff.
Eligibility for enrollment followed Taiwan’s National Health Insurance guidelines. Potential participants were evaluated by TCPC neurologists or psychiatrists and included residents with terminal cancer, advanced dementia (Clinical Dementia Rating ≥ 5 or Functional Assessment Staging Test stage 7b), severe neurodegenerative diseases other than dementia, or serious heart, liver, or lung disease. Advanced dementia patients present particular challenges for care due to profound cognitive and functional decline, highlighting the need to shift from aggressive or burdensome interventions to palliative-focused care.
The program emphasizes family engagement, providing detailed information through meetings and obtaining formal consent from family members for palliative care participation. Clinical services are delivered twice weekly at the nursing home and include medication management, nutritional evaluation, and monitoring or management of NG or Foley tubes. The multidisciplinary team is available around the clock for urgent consultations via instant messaging, with interim in-person services arranged when necessary.
The objectives of this program include reducing unnecessary medical interventions and emergency visits, thereby minimizing physical and emotional burdens for patients and their families. After patient death, clinical psychologists offer post-mortem support to families, while medical staff assist with death certificate procedures to facilitate funeral arrangements.
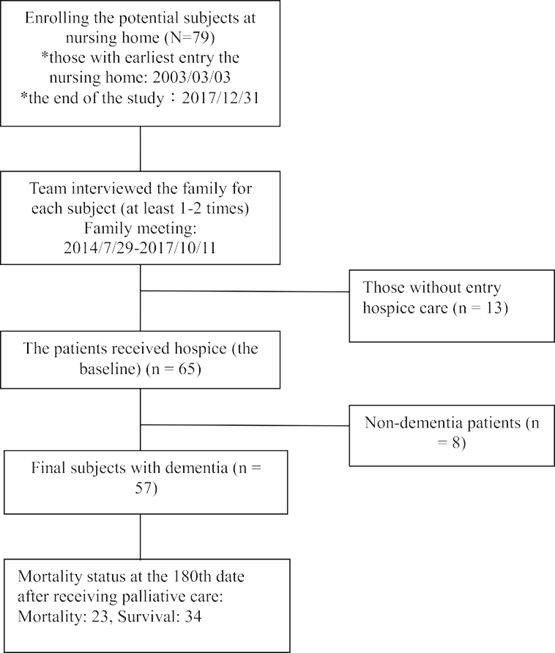
By October 2017, 79 residents had been enrolled in the program, 65 consented to receive palliative care, and 57 of these had advanced dementia and were included in the current analysis (Figure 1). The study follow-up continued until December 31, 2017. The study protocol was approved by the Institutional Review Board of Taipei City Hospital (TCHIRB-10707101-E). The survey instrument used in this study was specifically developed for this research and has not been previously published.
|
|
|
Figure 1. Flowchart of the study |
Variables
Patient demographics, including age and sex, were collected along with clinical information such as existing comorbidities and cognitive status, both at nursing home admission and at the start of palliative care. Data on healthcare use were also obtained, covering the number of medical department visits, prescribed medications, hospital admissions, duration of ICU stays, and emergency department visits before and after palliative care initiation. Functional ability was assessed using the Barthel Index [19], and cognitive performance was measured with the Mini-Mental State Examination [20]. Mortality was tracked at six months (180 days) following entry into the palliative care program, consistent with hospice eligibility criteria in the Medicare system that estimate survival under six months [18, 21].
Statistical analysis
Descriptive statistics summarized demographic and clinical characteristics of the dementia patients receiving palliative care. To compare healthcare utilization before and after program enrollment, paired t-tests were applied to average monthly indices.
Because dementia patients often remain in palliative care for periods exceeding six months and require in-person recertification under regulatory standards [22], mortality at 180 days was selected as the primary endpoint for analyzing potential risk factors. Clinical variables recorded before, at the initiation of, and during palliative care were evaluated as possible predictors, as outlined in Table 3.
Potential risk factors for six-month mortality were first examined using univariate logistic regression. Variables demonstrating statistical significance (p < 0.05) were then included in a multivariate logistic regression model using backward stepwise selection to identify independent predictors. Statistical significance was defined as a two-sided p-value < 0.05. Analyses were conducted using SAS software version 9.4 (SAS Institute Inc., Cary, NC, USA).
Patient characteristics
The clinical and demographic features of dementia patients enrolled in the palliative care program are presented in Table 1. In most cases, the patients’ children provided consent for palliative care after participating in at least one family meeting.
Table 1. Characteristics of dementia patients receiving palliative care.
|
Characteristics |
Men (N = 22) |
Women (N = 35) |
|
|
Mean (SD) |
Mean (SD) |
|
Age at Receiving Palliative Care (years) |
88.2 (5.6) |
89.2 (5.2) |
|
Duration from Entry to Nursing Home to Receiving Palliative Care (years) |
4.7 (4.1) |
5.2 (4.2) |
|
Duration from First Family Meeting to Entry of Palliative Care (days) |
24.1 (78.1) |
19.2 (45.8) |
|
|
N (%) |
N (%) |
|
Person Who Signed Palliative Care Contract |
|
|
|
Couple |
4 (18.2) |
1 (2.9) |
|
Child |
14 (63.6) |
30 (85.7) |
|
Others |
4 (18.2) |
4 (11.4) |
|
Family Members Participating in Family Meeting |
|
|
|
1–2 |
15 (68.2) |
26 (71.1) |
|
>2 |
7 (31.8) |
9 (28.9) |
|
Number of Family Meetings |
|
|
|
1 |
25 (92.6) |
30 (78.9) |
|
2 (twice) |
2 (7.4) |
7 (18.4) |
Participant characteristics
Among pre-existing conditions recorded at nursing home entry, hypertension was most prevalent (57.8%), followed by stroke (38.6%), diabetes mellitus (26.3%), and other cardiovascular diseases not related to hypertension (22.8%).
Evaluation of healthcare utilization
Table 2 summarizes the monthly use of healthcare services before and after patients entered the palliative care program. Following enrollment in hospice care, patients with advanced dementia showed a marked decline in healthcare utilization, including fewer visits to hospital departments (p < 0.001), a reduction in the number of medications prescribed (p < 0.001), decreased hospital admissions (p < 0.001), and fewer emergency department visits (p < 0.001). This indicates that the palliative care program was associated with a measurable reduction in reliance on medical services.
Table 2. Differences in the utilization of medical services before and after the provision of palliative care.
|
Characteristics (Average Number per Month) |
Pre-Palliative-Care Stageb (N = 57) |
Post-Palliative-Care Stagec (N = 57) |
Statisticsa |
|
|
Mean (SD) |
Mean (SD) |
|
|
The Departments Visited |
2.23 (0.96) |
0.07 (0.26) |
P < 0.001 |
|
Number of Medications |
7.84 (3.04) |
5.39 (2.51) |
P < 0.001 |
|
Number of Hospitalizations |
1.42 (1.45) |
0.07 (0.32) |
P < 0.001 |
|
Length of Stay (days) |
19.72 (22.74) |
0.56 (3.21) |
P < 0.001 |
|
Length of Stay of ICU Admissions (days) |
1.49 (5.82) |
0.00 (0.00) |
P = 0.058 |
|
Number of Visits to Emergency Department |
0.39 (0.82) |
0.02 (0.13) |
P = 0.001 |
aBased on paired t test
bThe average period of contribution in months (SD) in the prepalliative care stage: 10.53 (3.25)
cThe average period of contribution in months (SD) in the postpalliative care stage: 9.07 (8.73)
Factors linked to mid-term mortality
Table 3 presents the potential factors related to mid-term mortality, defined as death within 180 days of receiving palliative care. Univariate analysis indicated that patients who died within 180 days had experienced more than two hospital admissions prior to hospice care, showing borderline statistical significance (p = 0.058) compared with those who survived beyond 180 days. No other significant differences were found between patients who survived past 180 days and those who died within this period regarding age at hospice entry, the number of hospital departments visited per month before palliative care, or the monthly number of prescribed medications prior to hospice admission. Moreover, multivariate analysis did not identify any significant factors associated with mid-term mortality.
Table 3. Before and after palliative care factors associated with mortality within 180 d of the provision of palliative care.
|
Characteristics |
Mortality Within 6 Months (N = 23) |
Survival ≥ 6 Months (N = 34) |
Odds Ratioa |
95% CIa |
P-valuea |
|
Before Palliative Care (Baseline) |
N (%) |
N (%) |
|
|
|
|
Age at Receiving Palliative Care (y/o) |
|
|
|
|
|
|
≤ 85 |
5 (18.5) |
6 (17.6) |
Reference |
– |
– |
|
86–90 |
8 (29.6) |
15 (44.1) |
0.64 |
0.15–2.77 |
0.550 |
|
> 90 |
10 (51.9) |
13 (38.2) |
0.92 |
0.22–3.92 |
0.914 |
|
Number of Departments Visited per Month |
|
|
|
|
|
|
1 |
2 (8.7) |
9 (26.5) |
Reference |
– |
– |
|
2 |
13 (56.5) |
17 (50.0) |
3.44 |
0.63–18.72 |
0.153 |
|
> 2 |
8 (34.8) |
8 (23.5) |
4.50 |
0.73–27.74 |
0.105 |
|
Number of Medications Used per Month |
|
|
|
|
|
|
0–5 |
2 (8.7) |
10 (29.4) |
Reference |
– |
– |
|
> 5 |
21 (91.3) |
24 (70.6) |
4.38 |
0.86–22.27 |
0.075 |
|
Number of Admissions Within 1 Year |
|
|
|
|
|
|
0 |
5 (21.7) |
9 (26.5) |
Reference |
– |
– |
|
1 |
6 (26.1) |
20 (58.8) |
0.54 |
0.13–2.24 |
0.396 |
|
> 1 |
12 (52.2) |
5 (14.7) |
4.32 |
0.95–19.58 |
0.058 |
|
ICU Admission Within 1 Year |
|
|
|
|
|
|
Yes |
4 (17.4) |
1 (2.9) |
Reference |
– |
– |
|
No |
19 (82.6) |
33 (97.1) |
0.14 |
0.02–1.38 |
0.093 |
|
Number of ER Visits Within 1 Year |
|
|
|
|
|
|
0 |
18 (78.3) |
25 (73.5) |
Reference |
– |
– |
|
1–6 |
5 (21.7) |
9 (26.5) |
0.77 |
0.22–2.69 |
0.684 |
|
At Receiving Palliative Care |
|
|
|
|
|
|
Cognitive Impairment |
|
|
|
|
|
|
Severe |
23 (100) |
31 (91.2) |
Reference |
– |
– |
|
Moderate |
0 (0) |
2 (5.9) |
0 |
0 |
1.000 |
|
Mild |
0 (0) |
1 (2.9) |
0 |
0 |
0.999 |
|
Mobility |
|
|
|
|
|
|
Bedridden |
22 (95.7) |
26 (76.5) |
Reference |
– |
– |
|
Wheelchair |
1 (4.3) |
8 (23.5) |
0.15 |
0.02–1.28 |
0.082 |
|
Intake |
|
|
|
|
|
|
NG Tube Feeding |
20 (87.0) |
28 (82.4) |
Reference |
– |
– |
|
Oral Feeding |
2 (8.6) |
6 (17.6) |
0.47 |
0.09–2.56 |
0.380 |
|
Gastroenteric Tube Feeding |
1 (4.3) |
0 (0) |
2.26 |
0 |
1.000 |
|
Urination |
|
|
|
|
|
|
Diaper |
13 (56.5) |
20 (58.8) |
Reference |
– |
– |
|
Urinary Tube |
9 (39.1) |
11 (32.4) |
1.26 |
0.41–3.87 |
0.688 |
|
Bladder Fistula/Intestinal Fistula |
1 (4.3) |
3 (8.8) |
0.51 |
0.48–5.48 |
0.581 |
|
Respiratory Function |
|
|
|
|
|
|
Spontaneous Respiration |
6 (26.1) |
16 (47.1) |
Reference |
– |
– |
|
Tracheostomy |
2 (8.7) |
1 (2.9) |
5.33 |
0.41–70.20 |
0.203 |
|
Need Oxygen |
15 (39.1) |
17 (47.1) |
2.35 |
0.73–7.56 |
0.151 |
|
Barthel Index, Mean (SD) |
0 (0) |
0 (0) |
– |
– |
– |
|
MMSE, Mean (SD) [23] |
9.95 (0.31) |
9.87 (0.52) |
0.82 |
0.20–3.35 |
0.778 |
|
After Palliative Care |
|
|
|
|
|
|
Number of Departments Visited per Month |
|
|
|
|
|
|
0 |
21 (91.3) |
32 (94.1) |
Reference |
– |
– |
|
≥ 1 |
2 (8.7) |
2 (5.9) |
1.52 |
0.20–11.67 |
0.685 |
|
Number of Medications Used per Month |
|
|
|
|
|
|
0–5 |
10 (43.5) |
22 (64.7) |
Reference |
– |
– |
|
> 5 |
13 (56.5) |
12 (35.3) |
2.38 |
0.81–7.04 |
0.116 |
|
Number of Admissions After Palliative Care |
|
|
|
|
|
|
0 |
21 (91.3) |
33 (97.1) |
Reference |
– |
– |
|
≥ 1 |
2 (8.7) |
1 (2.9) |
3.14 |
0.27–36.86 |
0.362 |
|
ICU Admission After Palliative Care |
|
|
|
|
|
|
Nil |
23 (100) |
34 (100) |
– |
– |
– |
|
Number of ER Visits After Palliative Care |
|
|
|
|
|
|
0 |
23 (100) |
33 (97.1) |
Reference |
– |
– |
|
1 |
0 (0) |
1 (2.9) |
0.00 |
0 |
1.000 |
MMSE Mini-Mental State Examination. aBased on univariate logistic regression analysis
Results and Discussion
Key findings
This study yielded two primary findings. First, after initiating palliative care, dementia patients demonstrated a notable reduction in the use of medical services compared with their usage prior to receiving such care. Second, no significant risk factors for mortality were identified among advanced dementia patients undergoing palliative care.
Patient and service provider characteristics
All participants had dementia as their primary diagnosis, with hypertension and stroke being the most prevalent comorbidities. The majority were not diagnosed with cancer. Upon entering the palliative care program, most patients were bedridden, required tube feeding, and exhibited worsened cognitive function compared with their initial admission to the facility.
Regarding previously established models for palliative care delivery in nursing homes, a U.S. study [24] identified three effective approaches: Model 1, Palliative Care Consult Service, involves external consultants responding to requests from the nursing home medical director, attending physician, or director of nursing. Model 2, Nursing Home–Based Palliative Care, employs in-house palliative care personnel. Model 3, Nursing Home–Palliative Care Partnerships, offers fully integrated palliative care within the nursing home [25]. The TCPC–nursing home palliative care model applied in this study is a hybrid of Models 1 and 3, providing professional consultations while delivering ongoing care within the nursing home. This multidisciplinary approach has improved palliative care access for all residents, including biweekly patient visits, monthly family meetings with caregivers, and monthly team meetings to review and adjust treatment plans.
Evaluation of services
The evidence regarding palliative care’s effectiveness in reducing medical service utilization among dementia patients is mixed. Consistent with our findings, a U.S. study [26] reported that advanced dementia patients receiving palliative care in nursing homes required fewer medications, injections, feeding tubes, intravenous fluids, and other medical services, and had lower rates of hospital death than those not receiving palliative care. Similarly, a nationwide five-year cohort study in Taiwan by Chen et al. [6] found that palliative care reduced futile or burdensome interventions in dementia patients, though tube feeding remained an exception. Subgroup analysis of dementia patients without cancer showed that palliative care primarily reduced the risk of cardiopulmonary resuscitation. Conversely, a U.S. randomized controlled trial in hospitalized advanced dementia patients receiving palliative care found no significant impact on tube feeding, mechanical ventilation, or do-not-resuscitate orders [27].
Several factors may explain these discrepancies. First, variations in patient comorbidities can influence the relationship between palliative care and medical service use. Taiwanese studies report differing patterns in life-sustaining interventions depending on the primary diagnosis, such as dementia versus cancer [28]. Patients with dementia generally experience higher hospital and ICU admission rates and longer stays than cancer patients [6, 29], suggesting that palliative care’s effect on reducing burdensome treatments may be more evident in patients with cancer. Additionally, cancer prevalence was higher among study participants than in dementia patients not receiving palliative care [6], implying that having a cancer diagnosis could act as a protective factor against aggressive interventions.
Second, the absence of standardized palliative care guidelines may contribute to variability in care practices across studies, affecting the quality and consistency of interventions. Research on staff perspectives in dementia palliative care highlights that limited guidelines often lead to fragmented or inconsistent care [1, 9]. Cultural attitudes toward death and end-of-life care also influence palliative care delivery. In Taiwan, Confucian, Taoist, and Buddhist traditions shape older adults’ perspectives on autonomy, with family-oriented decision-making playing a central role [30]. Consequently, enrollment in palliative care often requires respecting family-based decisions, with professionals facilitating communication between residents and families regarding end-of-life preferences [30].
Regional differences in care and patient preferences
Studies in Taiwan have indicated that advanced dementia patients in Eastern countries often undergo more aggressive treatments during the final year of life compared with their Western counterparts [29]. Additionally, discrepancies frequently exist between patients’ and caregivers’ preferences regarding end-of-life care decisions [23, 31]. In contrast, research from North America [32, 33] and Europe [34, 35] reports a lower prevalence of tube feeding in end-stage dementia patients, ranging from approximately 2% to 25%, compared with studies in Asia, where over 50% of dementia patients receive enteral feeding [6, 35].
Our study focused on a relatively homogeneous group of patients without cancer and demonstrated that providing education and counseling on the terminal nature of dementia, its disease course, and the core principles of palliative care can enhance quality of life for both patients and caregivers. Furthermore, implementing palliative care in this population significantly reduced burdensome medical interventions.
Potential risk factors for mid-term mortality
This study did not identify significant mortality risk factors among advanced dementia patients receiving palliative care, aligning with previous research findings. The absence of reliable prognostic tools for estimating survival duration in dementia complicates decisions regarding the optimal timing for palliative care referral and the allocation of healthcare resources [1, 6, 10]. Under such conditions, patients, families, and clinicians may struggle to recognize dementia as a terminal illness. Survival studies in dementia have reported variable results, with mean or median survival ranging approximately from 3 to 10 years [7].
Previous research has proposed potential prognostic factors for mortality in dementia. For example, a U.S. study [36] identified cancer, diabetes, organ failure, and mechanical ventilation as factors influencing hospice referral among dementia patients. The U.S. National Hospice and Palliative Care Organization developed criteria for survival prediction and Medicare hospice eligibility, suggesting that advanced-stage patients (FAST stage 7c) with nutritional issues (e.g., >10% weight loss) or medical complications (e.g., recurrent sepsis, pressure ulcers) are at higher risk of dying within six months [10]. However, the predictive accuracy of these criteria has been questioned [18, 21]. Mitchell et al. subsequently developed the Mortality Risk Index [21] and the Advanced Dementia Prognostic Tool [18], based on 12 variables—age, sex, nursing home stay, shortness of breath, pressure ulcers, functional status, bedfast status, insufficient oral intake, bowel incontinence, BMI, recent weight loss, and congestive heart failure—with moderate predictability for six-month mortality among nursing home residents. The applicability of these tools to non-nursing home populations remains untested. Overall, no global consensus exists regarding reliable prognostic measures in dementia [1, 7], and our study reinforces this uncertainty.
In univariate analysis, we observed that patients with multiple hospital admissions prior to hospice entry may have a higher risk of six-month mortality, suggesting that these individuals had multiple health issues and were more vulnerable. It is reasonable to infer that patients with advanced disease and poor medical status are at greater risk of adverse outcomes.
Limitations
This study has several limitations. First, the patient cohort was relatively small, limiting statistical power. As an exploratory study, it investigated potential risk factors for mid-term mortality, highlighting the need for larger studies to confirm these findings. Second, the study was conducted in a single nursing home in a major Taiwanese city, limiting generalizability to the broader population. Nevertheless, unlike many previous studies, this research involved a homogeneous cohort of dementia patients without complex comorbidities, all receiving standardized care.
Conclusion
This study provides important clinical insights for professionals delivering palliative care to patients with advanced dementia. Our findings demonstrate a substantial reduction in medical service use—including hospital visits, prescribed medications, hospitalizations, and emergency department visits—following the introduction of palliative care. However, no significant mortality risk factors were identified, which limits the ability to determine the optimal timing for palliative care referral and resource allocation. The results underscore the value of an integrated palliative care approach for terminal dementia patients in nursing homes. Future research involving larger cohorts is needed to identify and stratify potential prognostic factors for mortality in this population.
Acknowledgments: None
Conflict of interest: None
Financial support: None
Ethics statement: None