A prior simulation-based investigation among medical professionals using manikins demonstrated that a cardiopulmonary resuscitation (CPR) coaching strategy yielded notable improvements in CPR quality compared with real-time audiovisual feedback from a defibrillator monitor. The objective of the current research was to determine whether these outcomes could be replicated in an expanded, multicenter study involving first responders. A multicenter, block-randomized trial was conducted among French firefighters. Rescuers were allocated into three distinct cohorts (n = 36 per group): a CPR coaching group, a defibrillator monitor group, or an unassisted control group. Every participant executed three separate 2-min sequences of external chest compressions using an adult cardiac arrest simulator, which recorded CPR quality, compression rate, chest recoil, and compression depth. A cohort of 108 participants was recruited across two distinct facilities; a single participant dropped out. During the second external chest compression sequence, the CPR coaching cohort demonstrated a significantly higher level of CPR quality than the defibrillator monitor cohort (median 99% [interquartile range (IQR) 99–100] vs 99% [78–99]; P = 0.0022). This statistical discrepancy remained evident during the third sequence (P = 0.0017). Compared with the unassisted control cohort, the quality of CPR in the CPR coaching group was markedly enhanced across both evaluation sequences (P < 0.001). In contrast, the defibrillator monitor cohort showed no statistically significant difference compared with the control group. This investigation validated the outcomes of our earlier project involving healthcare practitioners, confirming that CPR coaching is superior to defibrillator monitor feedback for improving CPR quality in a simulated environment with lay rescuers.
Introduction
Annually, within France, approximately 50,000 citizens suffer from an out-of-hospital cardiac arrest (OHCA) [1]. Across Europe, the 30-day survival probability ranges from 6% to 18% [2, 3]. Prompt administration of high-quality CPR is a primary determinant of post-OHCA survival, prompting ongoing investigations into methods to optimize the quality of compressions [4, 5]. Real-time CPR feedback generated by automated external defibrillators or defibrillator monitors (DMs) is among the most frequently deployed modalities intended to assist external chest compressions. The guidelines set forth by the International Liaison Committee on Resuscitation advocate integrating real-time audiovisual feedback and prompt technologies into clinical resuscitation as part of broader quality optimization initiatives. Nonetheless, investigations evaluating real-time CPR feedback have yielded inconsistent outcomes within clinical settings. Consequently, the isolated application of real-time audiovisual feedback and prompt instruments is not advised [6].
The use of real-time, on-scene guidance during resuscitative efforts by an external specialist, typically designated as CPR coaching, was evaluated in a 2025 systematic review that identified only 7 studies, only 1 of which focused on adult cohorts [7]. The investigators concluded that while CPR coaching demonstrated encouraging improvements in resuscitation quality, the strategy required further exploration. The AMACE investigation [8] built upon this body of evidence by evaluating an adult external chest compression CPR coaching algorithm against a defibrillator monitor during a manikin-based simulation involving emergency medical service personnel. Pronounced advancements in both overall CPR quality and compression pacing were detected in the CPR coaching cohort relative to the DM cohort. To build on these encouraging outcomes and evaluate the practical utility of this algorithm among first responders trained in basic life support, the current investigation, designated CADENCE (Comparison of Aids and Devices in External Cardiac Massage Enhancement), was conducted.
The primary intent of this study was to evaluate CPR quality when utilizing real-time feedback from a DM compared to CPR directed by the CPR coaching approach within a simulation-based framework featuring firefighters. Secondary objectives involved comparing the two distinct interventions under conditions of muscular exhaustion, as well as benchmarking their outcomes against an unassisted control cohort to determine a baseline estimation of the raw efficacy of each modality.
Materials and Methods
Study design and participant population
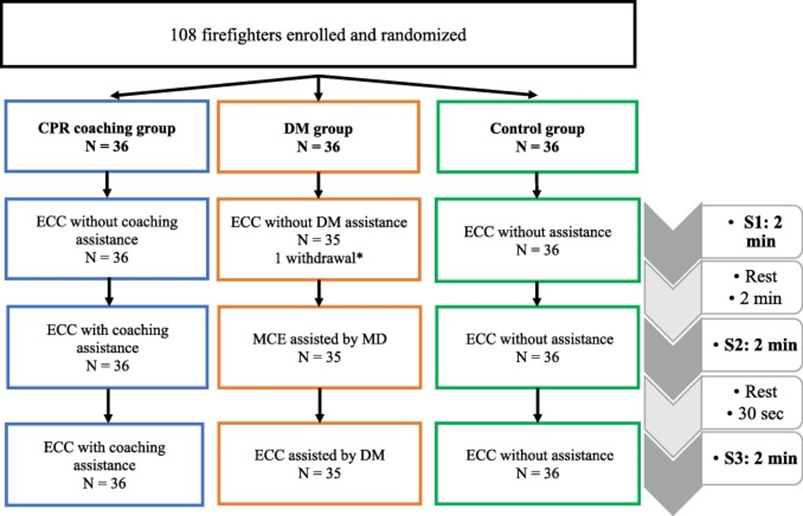
An open-label, multicenter, randomized controlled superiority study was conducted from September 2024 to February 2025 at two separate French fire and rescue installations in Normandy. Rescuers were assigned to one of three parallel arms: (i) an unassisted control arm, (ii) an arm supported by a defibrillator monitor (DM), and (iii) an arm supported by a human guide utilizing the CPR coaching strategy formulated in the AMACE investigation [8]. Each individual performed three separate 2-min external chest compression (ECC) blocks using a simulator manikin. The 2-min duration for the compression blocks was chosen for pragmatic reasons to match conventional real-world protocols, in which rescuer changeovers routinely occur every 2 minutes. The initial block (S1) was completed without any external guidance by all arms at the start of the study. This was succeeded by a 2-min recovery interval to facilitate partial recuperation of rescuer stamina and to replicate a standard personnel swap during ECC. The second block (S2) was subsequently executed with the assistance of the designated device or strategy. Following the completion of S2, a brief 30-s recovery pause was implemented to restrict physical recuperation and sustain muscular exhaustion—thereby mirroring real-world CPR rotation intervals—before executing the third ECC block (S3) under identical parameters to S2. No modifications were made to the initial study protocol after the trial was launched.
Ethics
The investigation received authorization from the Local Committee for Ethics and Health Research of the University of Caen Normandy (ID# 5094). Before enrollment, all candidates were provided with both written and verbal details regarding the study goals and participant rights. Informed consent was obtained from each individual before their involvement.
Inclusion criteria
Professional firefighters aged \ge 18 years who routinely administer ECC were deemed eligible for enrollment. Candidates were required to be free from any physical or psychological limitations that might compromise their capacity to execute the required physical task. Every participant held a valid basic life support certification that met French civil security training standards. The participants had no role in the design, execution, or analysis of the research project.
Randomization
Participants were manually allocated in a 1:1:1 ratio to one of the three study arms: the DM arm, the CPR coaching arm, or the unassisted control arm. Randomization was stratified by testing center and conducted in blocks of 12 individuals. Within each facility, sets of 12 identical, sealed, non-transparent envelopes were prepared in advance, with four allocated to each treatment branch. For each enrolled individual, the participant chose a single envelope at random from the prepared set. The research staff remained blind to the group assignments until the selected envelope was unsealed, thereby maintaining strict allocation concealment.
Intervention
For the monitor condition, rescuers utilized an X Series® unit (Zoll®, Chelmsford, Massachusetts, USA), an apparatus that incorporates a hand-mounted accelerometer to evaluate compression mechanics. This tool provides instant feedback on performance parameters via a digital readout of key variables (rate, depth, expansion), an audible metronome, and vocal directives. A study investigator supervised each device-assisted sequence. Following the conclusion of S1, fire service personnel received a standardized operational brief on the X Series unit and its interface. The monitoring investigator resolved any technical questions before stepping away, leaving the rescuer to depend solely on the electronic device's prompts during cycles S2 and S3.
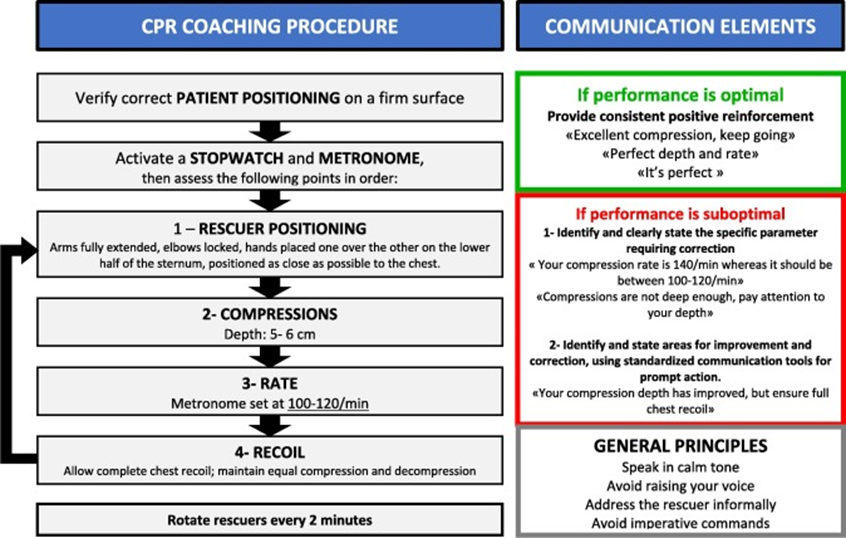
Participants in the coached condition received direction that matched the formal algorithm developed for the AMACE study (Figure 1). This protocol, developed in compliance with European Resuscitation Council standards [9], was structured by two primary investigators and was unquestioningly validated by a panel of four independent emergency medicine physicians. Refined in partnership with an academic social psychology facility, the algorithm incorporates specific psychological variables—namely self-efficacy, perceived locus of control, and social support frameworks—to enhance the interaction between the coach and the rescuer. The coaching role, operationalized according to Hunt et al. [10], was filled by emergency physicians with extensive practical experience in out-of-hospital resuscitation. An acoustic metronome calibrated to 110/min supported the process. In cases of suboptimal compression technique, the guide issued standardized corrections according to the communication strategies embedded in the algorithm. When the technique met the required parameters, the guide delivered periodic positive reinforcement while continuing silent, algorithm-directed monitoring, avoiding extraneous verbalizations that might cause cognitive overload for the rescuer.
|
|
|
Figure 1. Coaching algorithm developed in the AMACE study. (cm: centimeters, ECC: external chest compressions, min: minutes). |
Subjects randomized to the control condition completed the cycles entirely unassisted; the overseeing investigator provided no input beyond signaling the start and termination of each testing cycle.
Outcome measures
The trial used Little Anne anatomical models (Laerdal®, Stavanger, Norway), which are a standard instrument in the out-of-hospital simulation literature [11-13]. Resuscitation parameters were captured via integrated Laerdal® QCPR diagnostic software, a platform frequently utilized in simulation studies to log individual physical actions and generate an aggregated overall performance percentage based on compression rate, mechanical depth, and chest wall expansion [11, 13-20].
The primary metric of interest was overall resuscitation quality, measured via the proprietary QCPR composite calculation score (QECC). This percentage index (where 100% represents flawless execution) is derived according to European Resuscitation Council parameters by combining depth, pacing, and chest recoil variables. While widely deployed in professional training settings, this composite score has not undergone formal independent validation. Secondary metrics consisted of the isolated percentage scores for pacing accuracy, depth accuracy, and recoil compliance. For each separate variable, the software calculates the exact percentage of total compressions that fall strictly within the target windows mandated by contemporary resuscitation guidelines. Per European Resuscitation Council criteria, these optimal bands were defined as a pacing frequency of 100–120 compressions/min, an internal displacement depth of ≥ 5 cm, and unrestricted chest wall recoil to the natural baseline state; final values reflect the percentage of compressions meeting these thresholds.
The primary objective was to detect differences in the QECC index between the guided-coaching and monitor-assisted cohorts during cycle S2. The initial secondary objective focused on comparing the standalone depth, rate, and recoil percentages between the coached and monitor groups during S2. Additional secondary endpoints involved five separate intergroup comparisons: coaching versus monitor during S3, coaching versus unassisted control during S2 and S3, and monitor versus unassisted control during S2 and S3.
Statistical analysis
A formal a priori sample size calculation was not conducted for this exploratory study.
Raw frequencies and percentage distributions characterize categorical datasets; continuous variables are summarized by median and interquartile range (IQR: 25th–75th percentiles). The primary endpoint evaluation comparing the QECC index between the coaching and monitor groups during S2 was executed via a Mann-Whitney U test. To evaluate variation across specific percentiles of the QECC distribution between the two active cohorts (specifically the 25th, 15th, and 10th percentiles), 95% confidence intervals were generated using a bias-corrected accelerated (BCa) bootstrap. Parallel Mann-Whitney U tests were deployed to evaluate all secondary intergroup combinations, with the resulting p-values adjusted for family-wise error rates using the Bonferroni–Holm step-down method based on the total number of parallel hypotheses tested. All data calculations were run on an intention-to-treat (ITT) basis. No interim data reviews were integrated into the study timeline. For the single participant on the monitor arm who withdrew during the baseline cycle (S1), an idealized score of 100% was intentionally assigned to all four operational quality metrics; this approach ensured the most conservative possible outcome relative to the trial's primary alternative hypotheses. All computational operations were run by the Biostatistics and Clinical Research Unit at the University Hospital of Caen using IBM SPSS Statistics v23. A two-sided alpha level of P < 0.05 established statistical significance. Anonymized raw datasets can be acquired upon a formal request sent to the corresponding author.
Results and Discussion
Over the course of the recruitment window, 108 candidates met the inclusion criteria, and all volunteered to participate. Subjects were evenly distributed across three parallel groups of 36. One subject assigned to the monitor cohort had to exit the protocol prematurely due to active emergency service calls. All other randomized individuals successfully fulfilled the three sequential compression protocols. The comprehensive participant flowchart is structured in Figure 2.
|
|
|
Figure 2. Participant allocation and session flow of the CADENCE study. (CPR coaching: cardiopulmonary resuscitation coaching, ECC: external chest compressions, DM: defibrillator monitor, min: minutes, s: seconds, S1: first ECC session, S2: second ECC session, S3: third ECC session. Withdrawal due to service requirements. |
Population characteristics
The median age of the cohorts was calculated at 38.5 years [IQR 29.5–44.5] for the guided coaching arm, 38.0 years [IQR 29.0–47.0] for the monitor arm, and 40.5 years [IQR 36–46.0] for the unassisted baseline arm. Male subjects accounted for 88.9% of both the coaching and monitor cohorts and 100% of the control group. The median length of occupational emergency service experience was 20 years [IQR 10–25] for the coached rescuers, 19 years [IQR 12–25] for the monitor-guided rescuers, and 21 years [IQR 14–27] for the control personnel. Initial resuscitation quality scores during the unassisted S1 sequence were uniform across the three study arms, with the notable exception of compression pacing; here, the baseline median score was profoundly depressed in the group assigned to future coaching (47% [IQR 4–87]) compared to the group assigned to future monitor use (90% [IQR 49–100]). Comprehensive baseline demographics are organized in Table 1.
Table 1. Participant characteristics. Quantitative variables are expressed as medians with interquartile ranges. Abbreviations: DM = defibrillator monitor; QECC = QCPR composite score; S1 = first session without assistance.
|
Empty cell |
Control |
DM |
Coaching |
|
Age (years) |
40.5 [36.0–46.0] |
38.0 [29.0–47.0] |
38.5 [29.5–44.5] |
|
Sex |
|
|
|
|
Male |
36 (100%) |
32 (88.9%) |
32 (88.9%) |
|
Female |
0 (0%) |
4 (11.4%) |
4 (11.1%) |
|
Professional experience (Years) |
21 [14–27] |
19 [12–25] |
20 [10–25] |
|
ECC quality S1 |
|
|
|
|
QECC (%) |
97 [69–99] |
98 [88–99] |
95 [88–99] |
|
Depth (%) |
100 [100–100] |
100 [100–100] |
100 [100–100] |
|
Rate (%) |
70 [4–95] |
90 [49–100] |
47 [4–87] |
|
Full chest recoil (%) |
100 [40–100] |
87 [22–100] |
94 [35–100] |
Primary outcome
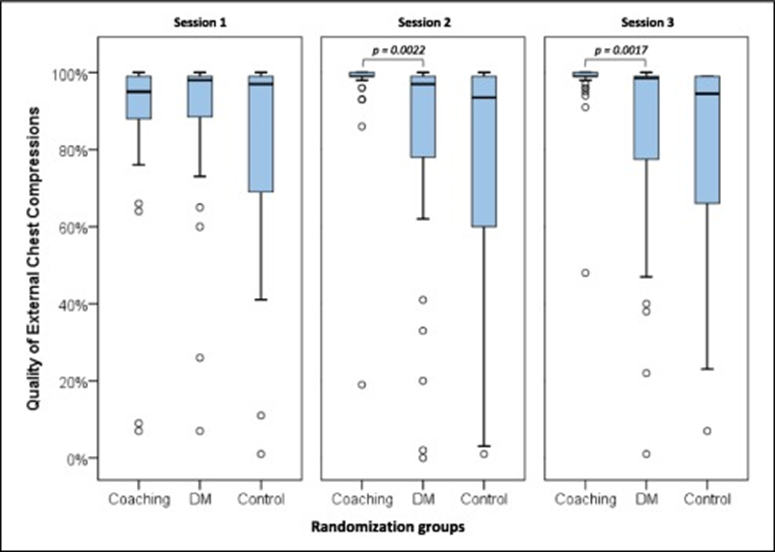
During the S2 sequence, the overall standard of resuscitation, quantified via the composite QCPR index (QECC), was substantially superior within the CPR coaching arm compared to the monitor arm (median [IQR]: 99% [99–100] vs. 98.5% [77.5–99]; P = 0.0022). While the central median values converged closely, the first-quartile metric showed a pronounced elevation in the manually coached cohort, with a 25th percentile discrepancy of 21.5% (95% confidence interval [CI]: 1–52%). This variation expanded further across lower tiers of the distribution, reaching 47% (95% CI = 10%–60%) at the 15th percentile and 55% (95% CI = 23%–94%) at the 10th percentile; this pattern illustrates a highly condensed data distribution favoring elevated scores within the coached cohort. Table 2 compiles the data for the primary outcome measure, while Figure 3 displays the longitudinal QECC outcomes across sequences S1 and S2.
Table 2. Primary and secondary outcome results of the CADENCE study.
|
P-values* |
|
|
(3) |
(2) |
(1) |
|
|
(2)–(3) |
(1)–(3) |
(1)–(2) |
Control |
DM |
Coaching |
|
|
CPR quality S2 |
|
|
|
|
|
|
|
QECC (%) |
0.45 |
< 0.001 |
0.0022 |
95 [66–99] |
99 [78–99] |
99 [99–100] |
|
Depth (%) |
0.67 |
0.62 |
0.32 |
100 [100–100] |
100 [100–100] |
100 [100–100] |
|
Rate (%) |
0.054 |
< 0.001 |
0.044 |
51 [1–98] |
95 [58–100] |
99 [97–100] |
|
Full chest recoil (%) |
0.52 |
0.32 |
0.0048 |
100 [26–100] |
86 [25–100] |
100 [95–100] |
|
CPR quality S3 |
|
|
|
|
|
|
|
QECC (%) |
0.34 |
< 0.001 |
0.0017 |
94 [60–99] |
97 [78–99] |
99 [99–100] |
|
Depth (%) |
0.11 |
0.24 |
0.36 |
100 [100–100] |
100 [100–100] |
100 [100–100] |
|
Rate (%) |
0.11 |
< 0.001 |
0.0047 |
61 [1–99] |
94 [48–100] |
100 [99–100] |
|
Full chest recoil (%) |
0.11 |
0.24 |
< 0.001 |
100 [63–100] |
57 [12–100] |
100 [100–100] |
*P-values for secondary outcomes were adjusted for multiple comparisons (CPR coaching: cardiopulmonary resuscitation coaching. Abbreviations: DM = defibrillator monitor; ECC = external chest compressions; QECC = QCPR composite score; S2 = second session with the assigned intervention; S3 = third session with the assigned intervention).
|
|
|
Figure 3. Median CPR quality (QECC) values with interquartile ranges are shown for each group across the three sessions, illustrating sustained superiority of CPR coaching over DM and control. Abbreviations: CPR = cardiopulmonary resuscitation; ECC = external chest compressions; DM = defibrillator monitor; QECC = QCPR composite score; S1 = session before intervention; S2 = first session with intervention; S3 = second session with intervention. |
Secondary outcomes
Throughout the S2 segment, the coached group exhibited a significantly higher accuracy rate for compression pacing than the monitor group (median [IQR]: 99% [97–100] vs. 95% [58–100]; P = 0.044), alongside superior compliance for full chest wall expansion (100% [95–100] vs. 86% [25–100]; P = 0.0048). Displacement depth demonstrated no meaningful statistical divergence, with both groups recording identical medians of 100% [100–100] (P = 0.32). Moving into the S3 evaluation, the performance gap in QECC between the manual coaching and device-guided cohorts widened (coaching: 99% [99–100] vs. DM: 97% [78–99]; P = 0.0017). Similarly, both compression pacing (P = 0.005) and full decompression recoil (P < 0.001) remained significantly optimized within the coached cohort.
When benchmarked against the unassisted control arm, the coaching modality demonstrated clear superiority for both the aggregate QECC index (P < 0.001) and pacing accuracy (P < 0.001) across both S2 and S3 assessments. Mechanical chest recoil was elevated but did not cross the threshold for statistical divergence when comparing coaching to control in S2 (P = 0.32) or S3 (P = 0.24). Compression depth remained uniform across both arms in all sessions. Finally, no statistically significant differences were identified between the monitor-assisted and control cohorts regarding the QECC index in S2 (P = 0.45) or S3 (P = 0.34), nor across any discrete physical parameters in either session. The secondary endpoint datasets are compiled within Table 2, and a longitudinal representation of QECC metrics across all three intervals for the three study arms is provided in Figure 3.
This trial, conducted with fire service personnel in a simulated setting, confirms that the resuscitation algorithm designed for the AMACE study results in significantly higher resuscitation quality, as measured by the QCPR composite score (QECC), compared with an automated monitor device [8]. While statistical differences in composite QECC metrics between the coached and device-guided groups were significant across both S2 and S3, translating these small absolute adjustments into clinical relevance requires a measured perspective. The proprietary configuration of the QECC algorithm limits the straightforward translation of narrow score differences into clinical settings. Crucially, the recorded experimental effect was not driven by shifts in median performance thresholds, but rather by substantial gains in the lower percentiles of the data distribution. This pattern reveals that manual direction primarily optimized execution among participants exhibiting lower baseline resuscitation skills.
This observation is reinforced by corresponding gains noted in standalone objective parameters, most notably compression pacing and complete chest decompression. The results indicate that on-scene instruction is highly effective at arresting declines in compression mechanics during extended resuscitative efforts. However, further verification in active clinical cardiac arrest scenarios is necessary. These tracking differences became even more distinct when compressions were performed under the influence of advanced physical fatigue during sequence S3. Pacing accuracy and uninhibited chest decompression are established cornerstones of effective resuscitation, maximizing systemic blood flow, right atrial return, and myocardial perfusion, which directly influence patient survival rates [21, 22]. Compared with the unassisted baseline cohort, manual coaching produced significant improvements in both composite scores (QECC) and pacing accuracy during S2 and S3. In contrast, isolated device monitoring provided no measurable benefit over baseline controls.
These observations align with the data gathered in the initial AMACE pilot trial [8], which analyzed the identical coaching algorithm against a defibrillator monitor using a simulation sample of 39 emergency medical practitioners. That baseline study noted significantly elevated QECC scores (P = 0.010) and compression pacing metrics (P = 0.0012) in favor of the coached cohort. In contrast, decompression recoil metrics trended upward but did not reach statistical significance (P = 0.080). The refinement of interactive human factors represents a core driver behind the positive outcomes generated by physical coaching. Shortly before the publication of the AMACE data, Lauridsen et al. [7] conducted a systematic evaluation of manual coaching during cardiopulmonary resuscitation, concluding that although the strategy showed considerable promise, further research was warranted. Taken together, the AMACE and CADENCE trials substantiate those early hypotheses and frame physical coaching as a highly effective approach for improving out-of-hospital resuscitation pathways.
Historical literature focused on maximizing resuscitation delivery has predominantly evaluated structural training frameworks, automated electronic feedback, or telephone dispatcher-guided protocols, frequently logging software-derived performance indices among university cohorts, non-professionals, or clinical staff [11, 13, 18, 23]. These projects typically relied on short, highly regulated scenarios and omitted the deployment of live, human instruction directly at the point of care. Consequently, high-level evidence evaluating live, on-scene manual coaching during adult resuscitation has remained remarkably sparse. The CADENCE project builds on this foundation by evaluating a regulated human-instruction algorithm with professional first responders under conditions of cumulative physical exhaustion, recording both integrated and component physical endpoints. Variances in participant experience, testing duration, support modalities, and primary outcome metrics across independent trials likely account for the divergent effects reported and may explain the distribution patterns documented in this study.
At present, coaching interventions are most frequently delivered remotely via telephone networks, an approach validated by a substantial body of evidence. Nevertheless, the lack of immediate visual oversight regarding a rescuer's real-time actions can significantly impede active correction and monitoring. Remote guidance can also be compromised by technical constraints (such as hardware availability, cellular network stability, or power outages) and environmental factors (such as ambient noise or localized chaos) that diminish its absolute utility [24-28]. Lastly, it fails to tap into the full range of human interaction channels, including physical and nonverbal cues. Conversely, the manual coaching methodology introduced in the AMACE trial circumvents these limitations. However, it demands the physical presence of a trained instructor, which is rarely achievable during the initial stages of a cardiac arrest event. Consequently, physical on-site coaching could serve as a vital adjunct to telephone-based guidance, assuming the oversight responsibilities initiated remotely at the start of an OHCA event to establish a continuous chain of supervision that enhances rescuer performance and clinical outcomes.
In both the AMACE and CADENCE trials, CPR coaching was delivered by emergency physicians. Within the French emergency framework, specialized medical teams can require up to 20 minutes to arrive at an emergency scene [29]. In contrast, first responder crews reach the site in approximately 13 minutes on average [30, 31]. Delegating the execution of CPR coaching to qualified first responders before the arrival of advanced medical personnel could therefore serve as a critical refinement to the baseline AMACE framework.
Several study limitations must be noted. First, the evaluation cycles were constrained to 2 minutes to reflect conventional rotation protocols in France accurately; while this choice preserves ecological validity, it might limit the generalizability of the findings to extended, uninterrupted resuscitation sequences and could have minimized the observed variance between groups. Second, physical exhaustion during the S3 sequence was not measured via objective physiological metrics, and the brief rest window may not perfectly replicate the exact fatigue curves induced by protracted continuous CPR. Third, the primary endpoint was dependent on the QCPR composite score (QECC), generated by a proprietary algorithm that lacks transparency and a direct clinical equivalent. To improve the overall interpretability of the data, however, the discrete parameters of this composite measure (displacement depth, pacing rate, and chest recoil) were independently scrutinized as secondary outcomes.
Furthermore, because the QCPR platform only logged the percentage of chest compressions matching pre-established target boundaries, analyzing the mean absolute values for compression depth, pacing, and recoil was not possible. To better validate these conclusions, prospective investigations utilizing more transparent, comprehensive parameters, such as the "overall excellent CPR" index [32, 33], would be highly valuable. Finally, while simulation frameworks are a conventional methodology for testing CPR quality-optimization mechanisms, active real-world resuscitation dynamics can diverge significantly, and this study protocol was not prospectively registered.
Conclusion
In this simulation-centered investigation, the deployment of CPR coaching via the AMACE-designed framework yielded superior resuscitation quality among fire service personnel compared with automated device-driven feedback. The manual coaching strategy appears to be a cost-effective, straightforward, and flexible methodology that can be adapted across diverse rescue personnel and tactical environments. These outcomes justify subsequent investigative efforts to optimize the practical implementation of CPR coaching, integrate it with telephone-dispatcher-directed systems, and analyze its definitive impact on active out-of-hospital cardiac arrest survival metrics.
Acknowledgments: We gratefully acknowledge Zoll® for providing the equipment, the Calvados Fire and Rescue Service, Nicolas Faures for his valuable support with the literature review, and the Calvados Medical Rescue and Health Service, particularly Lieutenant-Colonel Le Houssel and Commander Hamelin.
Conflict of interest: None
Financial support: None
Ethics statement: None