Individuals receiving palliative care often face substantial symptom burdens that affect both themselves and their families. Emotional distress, including depression and anxiety, should not be considered a normal part of advanced illness; it requires routine assessment, timely intervention, and ongoing monitoring. Psychological distress has been associated with worse physical symptoms, increased suffering, and higher mortality in patients with cancer. Comprehensive yet concise tools are needed to capture both physical and psychosocial needs, and the Integrated Palliative care Outcome Scale (IPOS) is one such measure. This study aimed to evaluate the palliative care needs of patients and to examine how accurately IPOS items related to anxiety and depression identify psychological distress. A multicentre observational study was conducted in nine Portuguese healthcare settings using convenience sampling. Eligible participants were adults (≥18 years) with a diagnosis of incurable or life-limiting illness who were cognitively able to consent. Patients experiencing acute distress or cognitive impairment were excluded. Descriptive statistics summarized participant characteristics. The diagnostic performance of IPOS anxiety and depression items was evaluated against the Hospital Anxiety and Depression Scale (HADS) using Receiver Operating Characteristic (ROC) curves and Area Under the Curve (AUC) analysis. Of 1,703 individuals screened between July 2015 and February 2016, 135 (7.9%) met inclusion criteria. The majority were excluded for being healthy (75.2%), largely from high-volume primary care centres. Participants had a mean age of 66.8 years (SD 12.7), with 43% female, and 80.7% had a cancer diagnosis. The most frequently reported concerns included anxiety among family or friends (36.3%), personal anxiety about illness (13.3%), and feelings of depression (9.6%). Applying a threshold score of 2/3, the IPOS items for anxiety and depression achieved AUC values above 70%, demonstrating acceptable screening accuracy. Psychological, familial, and spiritual needs were the most prominent concerns among this palliative population, highlighting that physical symptoms may be better managed than non-physical issues. Routine implementation of the IPOS could support healthcare teams in identifying and monitoring psychosocial distress, improving holistic, patient-centred care for both patients and their families.
Introduction
Palliative care adopts a holistic approach that can be introduced early alongside disease-directed treatments [1], aiming to alleviate both physical and non-physical symptoms for patients and their families [2–7]. While physical symptoms are often easier for healthcare professionals, patients, and caregivers to identify, non-physical symptoms can equally impair quality of life and contribute to suffering [8]. Evidence from a rapid systematic review indicates that psychological interventions in patients with long-term conditions can significantly improve at least one quality of life outcome, with effects maintained at follow-up [9]. Similarly, Ann-Yi S and colleagues reported that 24% of palliative inpatients and 19% of outpatients at a major cancer centre benefited from psychological services [8]. Psychological distress has also been associated with more severe physical symptoms, increased suffering, and higher mortality among cancer patients [10, 11]. Consequently, these needs should be assessed using validated outcome measures, and interventions tailored accordingly [12, 13].
Depression and psychological distress exemplify needs that should not be normalized in advanced disease [14]. Rather, they require systematic screening, diagnosis, and follow-up through appropriate pharmacologic, psychological, psychiatric, or combined interventions [14]. Patient-reported outcome measures are the preferred tools for assessing subjective symptoms, as patients are best positioned to describe their experiences. In cases of cognitive impairment, proxy-reported versions may be employed [15–19]. These instruments are generally brief yet multidimensional, with certain items usable to screen for common palliative needs [20].
The present study aimed to identify the primary palliative care needs of patients receiving care in Portuguese healthcare settings and to evaluate the screening performance of two IPOS items related to psychological distress [21, 22]. We hypothesized that: 1) anxiety and depression items would score highest among non-physical symptoms, and 2) the Area Under the Curve (AUC) for IPOS Item 3 (anxiety) and Item 5 (depression) would exceed 0.7 when compared to the Portuguese Hospital Anxiety and Depression Scale (HADS) subscale scores [23].
Materials and Methods
Patients and settings
This multicentre observational study collected data from nine Portuguese healthcare centres spanning northern to southern regions and urban to rural locations to enhance generalizability, using convenience sampling. Participating centres included seven hospital-based palliative care services, one oncology service, and one primary care facility. All patients attending these services were screened for eligibility by local healthcare professionals.
Inclusion criteria were: age ≥18 years, ability to provide informed consent as assessed by the clinician, diagnosis of an incurable, potentially life-threatening illness, and fluency in Portuguese. Exclusion criteria included patients experiencing distress that prevented sustained conversation or those with cognitive impairment, as judged by the clinician. A standard operating procedures manual was distributed to all centres, with a local facilitator/champion overseeing adherence. The full study protocol has been published elsewhere [19].
Measures
The study used the patient-reported Portuguese version of the IPOS, which had been culturally adapted and validated for European Portuguese [21, 22]. The adaptation process involved two independent translators (clinical and non-clinical) producing initial versions, which were reconciled into a consensus version by two independent reviewers blinded to the original IPOS. This version underwent back-translation by two additional independent translators and subsequent reconciliation. Three clinical reviews were performed by a specialist palliative care physician, a specialist nurse, and a non-clinical researcher—resulting in the final Portuguese version. Discrepancies in verb tense, word choice, and response category phrasing were resolved through discussion during translation and clinical review stages.
Measures
A Portuguese adaptation of the Integrated Palliative care Outcome Scale (IPOS) was developed and evaluated for psychometric properties. Internal consistency, excluding open-ended items, showed Cronbach’s alpha values ranging from 0.68 to 0.72. Inter-rater reliability between patients and healthcare professionals was assessed using intraclass correlation coefficients (ICC), which were highest for mobility (ICC = 0.726) and lowest for practical problems (ICC = 0.088). Construct validity was supported through convergent and divergent validity analyses, with Spearman’s rho ranging from 0.390 to 0.631 (p ≤ 0.000). The instrument also demonstrated sensitivity to change, as Wilcoxon signed-rank tests revealed significant differences in three symptoms between T1 and T2.
The IPOS is a concise, 19-item, multidimensional tool capturing core concerns in palliative care. Item 1 is an open-ended question asking respondents to identify their three main problems or worries in the past week (these free-text data are not reported here). Items 2–9 employ a 5-point Likert scale (0 = not at all, 1 = slightly, 2 = moderately, 3 = severely, 4 = overwhelmingly). Item 2 lists ten common physical symptoms, with the option to add up to three additional symptoms. Item 3 addresses anxiety, Item 4 asks about family or friends’ worry, and Item 5 pertains to depression. Item 6 relates to feelings of peace, Item 7 to sharing emotions with significant others, Item 8 to information needs, and Item 9 to practical problems arising from illness. The patient version includes an additional question asking whether the questionnaire was completed independently or with assistance. A footnote at the end encourages patients to discuss any concerns with their healthcare professional, enhancing the tool’s real-time clinical utility.
The Portuguese version of the Hospital Anxiety and Depression Scale (HADS) is a 14-item screening tool, divided into anxiety and depression subscales with seven items each, using a 4-point Likert response format. A cut-off score of 11 is recommended for both subscales. The instrument has been validated as reliable for assessing anxiety and depression across diverse medical populations [23].
Analysis
Data quality was first examined, and Little’s MCAR test confirmed that missing data were missing completely at random. Descriptive statistics were used to summarize demographic and clinical characteristics. All IPOS psychological, emotional, and spiritual items (Items 3–7) were compared to the Portuguese HADS. Receiver operating characteristic (ROC) curves were generated to determine the two IPOS items with the highest discriminant ability, and a cut-off score of 2/3 was selected after preliminary evaluation. Sensitivity, specificity, positive predictive value (PPV), negative predictive value (NPV), false positive rate (FPR), false negative rate (FNR), and positive and negative likelihood ratios weighted by prevalence were calculated. Thresholds of ≥70% were considered acceptable and ≥80% high for sensitivity, specificity, PPV, and NPV; FPR and FNR ≤30% were considered low. All analyses used 95% confidence intervals. No formal sample size calculation was performed, as prior literature using the Palliative care Outcome Scale and HADS involved secondary analyses of multiple datasets rather than IPOS-specific evaluation.
Ethics
Ethical approval was obtained from all relevant research ethics committees, in accordance with the 1964 Helsinki Declaration and its later amendments. All participants provided written informed consent. Data were analyzed using SPSS version 22 (IBM Corp., Armonk, NY).
Results and Discussion
Between July 1, 2015, and February 2016, 1703 individuals were screened, predominantly at a primary healthcare facility. Of these, 18 patients (1.1%) declined participation, and 140 (8.2%) were excluded. A total of 135 patients (7.9%) met inclusion criteria and were enrolled in the study (Table 1).
Table 1. Patients screened and included in the study by participating centre.
|
Participating Service |
Number Screened (N, % of Total Screened) |
Number Included (N, % of Total Included) |
|
Oncology Hospital Service |
78 (4.6%) |
25 (18.5%) |
|
Palliative Care Service 1 (North) |
96 (5.6%) |
9 (6.7%) |
|
Palliative Care Service 2 (North) |
28 (1.6%) |
17 (12.6%) |
|
Palliative Care Service 3 (South) |
18 (1.1%) |
1 (0.7%) |
|
Palliative Care Service 4 (North) |
77 (4.5%) |
24 (17.8%) |
|
Palliative Care Service 5 (South) |
64 (3.8%) |
17 (12.6%) |
|
Primary Care Centre 1 (South) |
119 (7.0%) |
3 (2.2%) |
|
Primary Care Centre 2 (South) |
1177 (69.1%) |
25 (18.5%) |
|
Palliative Care Service 6 (Central) |
46 (2.7%) |
14 (10.4%) |
|
Total |
1703 (100%) |
135 (100%) |
The predominant reason for exclusion was that patients were considered healthy, accounting for 75.2% of screened individuals. This outcome was anticipated, as the primary care centre screened the majority of participants, reflecting its high daily patient volume, most of whom were healthy. Among the included sample (n = 135), the mean age was 66.8 years (SD = 12.7), with 58 patients (43%) being female. Educational attainment was low for many participants, with 74 (54.8%) having up to four years of formal education, and 74 (54.8%) resided in the Northern region of Portugal. The majority of patients (n = 109; 80.7%) had a cancer diagnosis and were recruited primarily from the seven hospital-based palliative care services (Table 2).
Table 2. Demographic and clinical information of participants Demographic and clinical information N(%).
|
Category |
Subcategory |
Value |
|
Mean Age (years, SD) |
|
66.8 (12.7) |
|
Gender |
Male |
77 (57%) |
|
Education (Years) |
|
|
|
|
Reads and writes |
5 (3.7%) |
|
|
4 years |
81 (60%) |
|
|
6 years |
20 (14.8%) |
|
|
9 years |
10 (7.4%) |
|
|
10 years to college |
19 (14%) |
|
Geographical Region |
|
|
|
|
North |
74 (54.8%) |
|
|
Central |
25 (18.5%) |
|
|
South |
36 (26.7%) |
|
Area |
|
|
|
|
Urban |
94 (69.6%) |
|
|
Peri-urban |
31 (23%) |
|
|
Rural |
10 (7.4%) |
|
Place of Care |
|
|
|
|
Primary care |
28 (20.7%) |
|
|
Hospital services |
25 (18.5%) |
|
|
Palliative care services |
82 (60.7%) |
|
Cancer Diagnosis |
|
109 (80.7%) |
|
Phase of Illness |
|
|
|
|
Stable |
64 (47.4%) |
|
|
Unstable |
28 (20.7%) |
|
|
Deteriorating |
43 (31.9%) |
|
|
Terminal |
0 (0%) |
|
Surprise Question (Life Expectancy) |
|
|
|
|
> 1 year |
37 (27.4%) |
|
|
6 months to 1 year |
45 (33.3%) |
|
|
< 6 months |
48 (35.6%) |
Table 3 outlines the main reasons for participant ineligibility and exclusion. Most patients (n = 98, 72.6%) were invited to participate during external consultations. Of those included, nearly one-third (31.1%) completed the questionnaires independently, without external assistance.
Table 3. Reasons for ineligibility and exclusion.
|
Category |
Reason for Ineligibility/Exclusion |
Number (N, %) |
|
Ineligible |
|
|
|
|
Under 18 years |
91 (5.9%) |
|
|
Does not understand Portuguese |
1 (0.06%) |
|
|
Cannot read or write |
78 (5.0%) |
|
|
Illness with potential for cure |
3 (0.2%) |
|
|
Healthy |
1165 (75.2%) |
|
|
No reason provided |
72 (4.6%) |
|
Excluded |
|
|
|
|
Distress |
52 (3.4%) |
|
|
Cognitive deterioration |
73 (4.7%) |
|
|
No reason provided |
15 (0.9%) |
|
Total |
|
1550 (100%) |
Analysis of missing data indicated that values were missing at random (Little’s MCAR test: Chi-Square = 2452.946, DF = 2398, p = .213). Missingness across items ranged from 1 to 5%, which is considered manageable, with rates below 1% regarded as trivial and those exceeding 15% potentially compromising interpretability [24]. Given the non-parametric distribution typical of palliative care populations, missing values were addressed using median imputation.
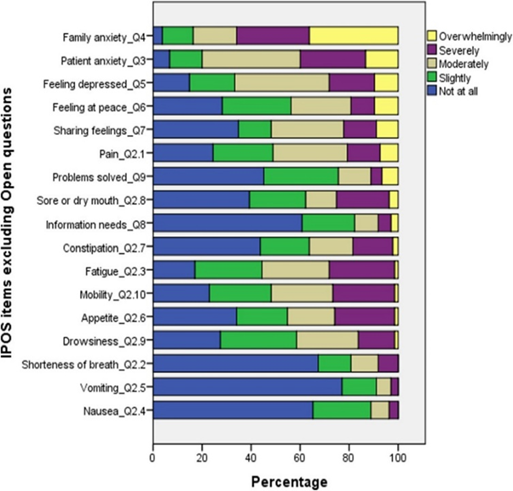
Regarding the prevalence of patient needs, the IPOS items with the highest proportion of severe concern (=4) were: family or friends being anxious or worried (36.3%), feeling anxious about illness (13.3%), feeling depressed (9.6%), feeling at peace (9.6%), sharing feelings (8.9%), and pain (7.4%). Conversely, items with the lowest prevalence (=0) included vomiting (77%), shortness of breath (67.4%), nausea (65%), information needs (60.7%), practical problems (45.2%), and constipation (43%) (Figure 1).
|
|
|
Figure 1. IPOS scores for prevalence of main palliative needs |
Screening for anxiety and depression
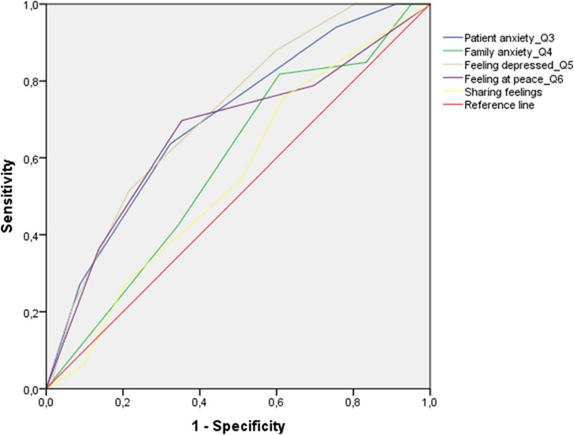
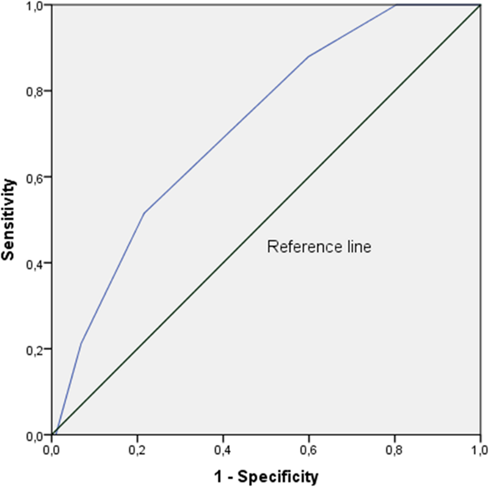
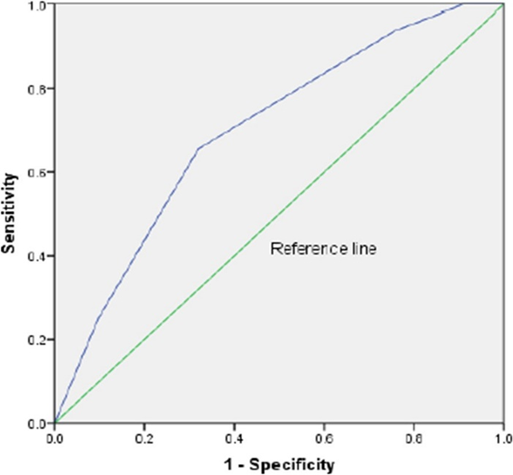
Items 3 (anxiety) and 5 (depression) demonstrated the highest areas under the curve (AUC) (Figure 2). The prevalence of depression was 24.4% (95% CI: 17.6–32.7%), with an AUC of 0.72 (95% CI: 0.62–0.81, p < 0.001) (Figure 3). For this item, sensitivity was 51.5% and specificity was 78.4%, with a positive predictive value (PPV) of 43.6% and a negative predictive value (NPV) of 83.3%. Regarding anxiety, the prevalence was 23.7% (95% CI: 16.9–31.9%), and the AUC was 0.70 (95% CI: 0.60–0.80, p < 0.001) (Figure 4). Sensitivity and specificity were 65.6% and 68.0%, respectively, while PPV and NPV were 38.8% and 86.4% (Table 4).
|
|
|
Figure 2. Area Under the Curve for IPOS items 3 to 7 |
|
|
|
Figure 3. Area Under the Curve for Portuguese IPOS item 5, depression |
|
|
|
Figure 4. Area Under the Curve for Portuguese IPOS item 3, anxiety |
Table 4. Estimated Values for items 3 and 5, cut-off 2/3, against the HADS subscales, using cut-off 10/11.
|
|
Sens (%) |
CIs (%) |
Spec (%) |
CIs (%) |
PPV (%) |
CIs (%) |
NPV (%) |
CIs (%) |
FPR (%) |
CIs (%) |
FNR (%) |
CIs (%) |
Ratios + |
CIs (%) |
Ratios - |
CIs (%) |
|
Item 3 – anxiety Prevalence: 23.7% (C.I. 16.9–31.9%) |
65.6 |
0.47–0.81 |
68.0 |
0.58–0.77 |
38.8 |
0.26–0.53 |
86.4 |
0.77–0.93 |
0.61 |
0.47–0.74 |
0.14 |
0.07–0.23 |
0.64 |
0.43–0.95 |
0.16 |
0.09–0.27 |
|
Item 5 – depression Prevalence: 24.4% (C.I. 17.6–32.7%) |
51.5 |
0.34–0.69 |
78.4 |
0.69–0.86 |
43.6 |
0.28–0.60 |
83.3 |
0.74–0.90 |
0.56 |
0.40–0.72 |
0.17 |
0.10–0.26 |
0.78 |
0.49–1.21 |
0.2 |
0.13–0.31 |
In this study, the predominant palliative care needs identified among patients were psychological, family-related, and spiritual. The Integrated Palliative care Outcome Scale (IPOS) proved effective in systematically capturing these needs. Notably, clinical teams appeared to address physical symptoms adequately, which is encouraging. Evidence suggests that once physical needs are managed, non-physical concerns become more salient and should be systematically assessed and addressed using patient-centered outcome measures [25, 26].
Among non-physical concerns, the most frequently reported issue was anxiety experienced by family or friends (36.3%), reflecting the central role of family in Portuguese culture and the common practice of involving family in healthcare decisions. Patient-reported anxiety and depression were the next most prevalent concerns, despite the exclusion of individuals in obvious distress. This aligns with existing literature indicating that anxiety often arises in patients with advanced disease due to diagnostic, treatment, and prognostic uncertainty [14], and that depression is also common in this population [27]. The prevalence rates observed in our study are consistent with findings from Ann-Yi S. et al. though that study focused exclusively on cancer patients [8]. Symptom clusters, combining physical and non-physical needs, are commonly observed in both cancer and non-cancer populations [28, 29]. The observed prevalence of depression in our cohort (24.4%) was higher than that reported in Antunes et al. using a single-item Palliative care Outcome Scale (17.5%, 95% CI 14.1–21.6%) [21], but lower than the 30% estimated by Hotopf et al. for depressive disorders in advanced disease [30].
The screening performance of IPOS items for anxiety (item 3) and depression (item 5) was acceptable, with AUC values exceeding 0.70, although the lower confidence interval limits were slightly below this threshold. Using a cut-off of 2/3, sensitivity was modest, indicating limited ability to identify true positive cases; however, specificity and negative predictive value were strong. These findings suggest that these IPOS items are particularly effective in ruling out true negative cases, an important component of screening [31], reinforcing the external validity of IPOS in this context.
A key limitation of the study was the absence of a diagnostic gold standard, such as a structured psychiatric interview based on the DSM-5, due to resource constraints. Instead, the HADS was used, which, while widely accepted and extensively validated for both clinical and research purposes, remains a screening rather than diagnostic tool.
Systematic use of the Portuguese IPOS could assist clinical teams in monitoring and addressing both physical and non-physical needs of patients and families. Specifically, items 3 and 5 appear suitable for screening patients with advanced illness, particularly to exclude those without anxiety or depression [31, 32].
Conclusion
Patient-centered outcome measures serve as valuable communication tools, providing a shared language for patients, families, healthcare professionals, institutions, and policymakers, ultimately supporting evidence-informed care. Establishing the screening properties of these tools enables not only improved clinical care but also the conduct of rigorous research. This study demonstrates that the Portuguese IPOS is effective in identifying psychological needs and can be reliably used to screen patients with advanced disease for anxiety and depression.
Acknowledgments: None
Conflict of interest: None
Financial support: None
Ethics statement: None