Regional cerebral oxygen saturation (rSO₂) offers a non-invasive indicator of brain perfusion. Despite its potential, the dynamics of rSO₂ during pre-hospital management of out-of-hospital cardiac arrest (OHCA) patients remain poorly understood. This study explored whether different temporal patterns of rSO₂ were linked to clinical outcomes. Between June 2013 and December 2019 in Osaka City, Japan, emergency life-saving technicians (ELTs) used portable devices to measure rSO₂ in OHCA patients. Serial changes were classified as type 1 (progressively increasing) or type 2 (stable or decreasing). Cases where monitoring began after return of spontaneous circulation (ROSC) were excluded. Outcomes included prehospital ROSC, survival to hospital admission, 1-month survival, and favorable neurological status (Cerebral Performance Category [CPC] 1–2). Among 87 patients analyzed, 40 exhibited type 1 patterns (median age 80.5 years, 50% male) and 47 type 2 patterns (median age 81 years, 59.6% male). After adjusting for potential confounders, type 1 patients were significantly more likely to achieve prehospital ROSC (27.5% vs. 4.3%; adjusted odds ratio [AOR] 5.67, 95% CI 1.04–30.96, p = 0.045) and survive to hospital admission (42.5% vs. 12.8%; AOR 3.56, 95% CI 1.11–11.43, p = 0.033). No statistically significant differences were observed in 1-month survival or neurological outcomes. An increasing trend in rSO₂ during pre-hospital resuscitation correlates with higher rates of ROSC and survival to admission. Real-time cerebral oxygen monitoring in the field may help optimize resuscitation approaches.
Introduction
Regional cerebral oxygen saturation (rSO₂) is a non-invasive indicator of cerebral perfusion that has been widely studied in resuscitation research [1–3]. Unlike single measurements, tracking the serial changes in rSO₂ over time may provide more meaningful insights into a patient’s condition [4–6]. Although several studies have suggested that measuring rSO₂ at hospital arrival can help predict neurological outcomes in out-of-hospital cardiac arrest (OHCA) patients [7–9], our previous work has shown that rSO₂ values can fluctuate considerably depending on the patient’s status at the time of measurement [3, 5, 6].
Most commercially available near-infrared spectroscopy (NIRS) devices are designed based on Ito et al.’s model, which assumes a fixed venous-to-arterial ratio in the cerebral cortex of roughly 70/30% or 75/25% [10–12]. However, evidence indicates that this ratio is not constant across patients [13], suggesting that using a fixed model may be suboptimal for device validation. Furthermore, rSO₂ values are affected by physiological variables such as cardiac output, PaCO₂, and pH, and measurements can differ between devices even for the same patient [14, 15]. Therefore, assessing relative changes from an individual patient’s baseline is considered more reliable.
In the prehospital setting, there is limited evidence on how rSO₂ changes during cardiopulmonary resuscitation (CPR) in OHCA patients [16,17]. To address this, we developed a portable rSO₂ monitor (HAND ai TOS®; TOSTEC CO., Tokyo, Japan), small enough for use in the field (170 × 100 × 50 mm; 600 g). Since 2013, emergency life-saving technicians (ELTs) have been able to perform prehospital rSO₂ monitoring, marking the first such implementation worldwide [5, 18]. Preliminary findings published in 2016 highlighted the importance of monitoring serial rSO₂ changes during prehospital CPR and suggested its potential for informing new resuscitation strategies [5]. Building on this growing registry of OHCA patients, the present study aims to investigate the association between patterns of serial rSO₂ changes in the prehospital setting and patient outcomes.
Materials and Methods
Study design, participants, and setting
We conducted a prospective observational study enrolling adults (≥18 years) who experienced out-of-hospital cardiac arrest (OHCA) and had measurable cerebral rSO₂, treated by emergency life-saving technicians (ELTs) in Osaka City, Japan, between June 2013 and December 2019. Osaka City, situated in central Japan, spans 225.30 km² and had a population of 2,746,983 in 2020 [19]. Of the city’s 63 EMS ambulance teams, nine were gradually equipped with portable rSO₂ monitoring devices, beginning with a single unit and expanding as the study progressed. Patients whose rSO₂ measurements began after return of spontaneous circulation (ROSC) were excluded from the analysis.
CPR was administered by ELTs according to the Japan Resuscitation Council Guidelines (2010 or 2015), which are based on the International Liaison Committee on Resuscitation recommendations [20, 21]. The rSO₂ sensor was applied to the patient’s forehead by the ELTs, and treatment decisions were made independently of the rSO₂ readings.
We collected detailed pre-hospital information from EMS records, including age, sex, initial cardiac rhythm, bystander CPR status, and ambulance response times. Corresponding in-hospital outcomes were obtained from the treating facilities in accordance with the Utstein reporting style. Pre-hospital rSO₂ data were subsequently merged with the clinical database for analysis. The study protocol was approved by the Ethics Committee of Osaka University Graduate School of Medicine (No. 12446-7), and the requirement for informed consent was waived due to the patients’ critical condition.
Portable rSO₂ monitoring system
For this study, we used a portable near-infrared spectroscopy (NIRS) device, HAND ai TOS® (TOSTEC CO., Tokyo, Japan), previously developed for field use [5, 18]. This device has not received regulatory approval from the Medicines and Healthcare Products Regulatory Agency (MHRA) or the U.S. Food and Drug Administration (FDA). HAND ai TOS measures cerebral oxygen saturation by emitting three near-infrared wavelengths that are selectively absorbed by oxyhemoglobin and deoxyhemoglobin. The light penetrates roughly 3 cm beneath the skin, and a photodiode captures the reflected signal, providing an estimate of hemoglobin oxygenation primarily in the cerebral cortex.
Evaluation of serial rSO₂ changes
The portable monitoring system allows rSO₂ measurements every second without requiring arterial pulsation, enabling continuous assessment in patients with cardiopulmonary arrest (CPA). Two rSO₂ readings, one from each hemisphere, were recorded simultaneously, and the mean value was used for analysis. In a prior study involving 15 healthy adults (10 men, 5 women; mean age 43.2 ± 8.9 years), the normal cerebral rSO₂ range was established as 71.2 ± 3.9% on room air [22]. For this study, serial rSO₂ patterns were classified into two categories: type 1, defined as an increase of at least 5% from the initial measurement, and type 2, defined as a non-increasing pattern.
Endpoints
The primary outcome was prehospital return of spontaneous circulation (ROSC). Secondary outcomes included survival to hospital admission, 1-month survival, and favorable neurological outcome, defined as Cerebral Performance Category (CPC) 1 or 2.
Drop phenomenon
During monitoring, we observed instances of a sudden, marked decrease in rSO₂, which we termed the “drop phenomenon,” potentially reflecting acute cerebral circulatory failure. Patients exhibiting this phenomenon were analyzed separately to evaluate its clinical significance.
Statistical analysis
Continuous variables were compared using the Wilcoxon rank-sum test, while categorical variables were analyzed with the chi-square or Fisher’s exact test, as appropriate. Multivariable logistic regression was performed to identify factors associated with study outcomes, with adjusted odds ratios (AORs) and 95% confidence intervals (CIs) reported. Potential confounders—selected based on prior literature and biological plausibility—included age, sex, witness status, and bystander CPR. Statistical significance was defined as p < 0.05. All analyses were conducted using JMP Pro 13 (SAS Institute Inc., Cary, NC, USA).
Results and Discussion
Patient characteristics
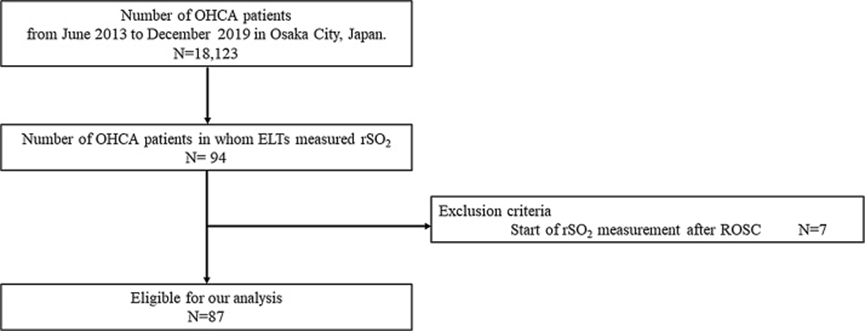
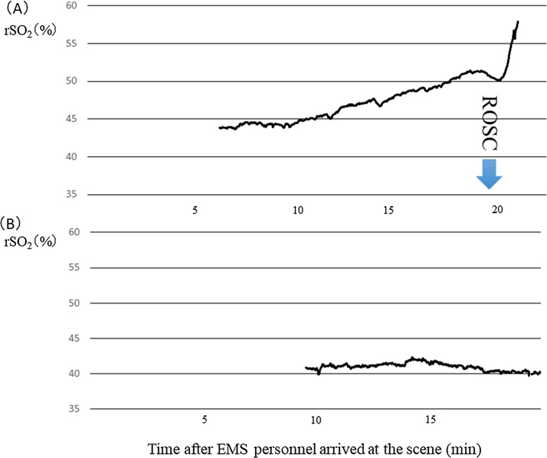
Figure 1 illustrates the flow of patients included in this study. During the study period, a total of 18,123 OHCA cases occurred in Osaka City, of which 94 patients were enrolled for rSO₂ monitoring. Seven patients were excluded because measurements began after return of spontaneous circulation (ROSC). Representative examples of type 1 and type 2 serial rSO₂ patterns are shown in Figure 2.
Table 1 summarizes the characteristics of patients who had not achieved ROSC at the start of rSO₂ monitoring. In total, 87 patients were included in the analysis: 40 patients exhibited type 1 (increasing rSO₂) patterns (median age 80.5 years [IQR 72–85.5], 50.0% male), and 47 patients exhibited type 2 (non-increasing rSO₂) patterns (median age 81 years [IQR 71–84], 59.6% male). The proportions of patients with witnessed arrest and those receiving adrenaline administration by ELTs were significantly higher in the type 1 group compared with type 2 (p = 0.003 and p = 0.001, respectively).
|
|
|
Figure 1. Patient flow, OHACA, out-of-hospital cardiac arrest; rSO2, regional saturation of oxygen; ELTs, emergency life-saving technicians |
|
|
|
Figure 2. Representative examples of serial cerebral rSO₂ changes |
(A) Type 1: Increasing pattern. A 95-year-old woman with pulseless electrical activity (PEA) on initial ECG (witnessed [+]; bystander CPR: unknown) showed gradually rising rSO₂ values, ultimately achieving ROSC. After ROSC, her rSO₂ increased more sharply than before.
(B) Type 2: Non-increasing pattern. A 33-year-old man with asystole on initial ECG (witnessed [–]; bystander CPR [–]) showed no rise in rSO₂ values and did not achieve ROSC in the prehospital setting.
Abbreviations: CPR, cardiopulmonary resuscitation; ECG, electrocardiogram; EMS, emergency medical service; PEA, pulseless electrical activity; ROSC, return of spontaneous circulation; rSO₂, regional cerebral oxygen saturation.
Table 1. Characteristics of patients without ROSC when ELT started rSO2 monitoring
|
Characteristic |
Type 1: Increasing pattern (n = 40) |
Type 2: Non-increasing pattern (n = 47) |
p-value |
|
Sex, male |
20 (50.0%) |
28 (59.6%) |
0.395 |
|
Age, years, median (IQR) |
80.5 (72–85.5) |
81 (71–84) |
0.932 |
|
Initial cardiac rhythm, n (%) |
0.097 |
||
|
Venticular fibrillation (VF) |
5 (12.5%) |
3 (6.4%) |
|
|
Pulseless electrical activity (PEA) |
16 (40.0%) |
11 (23.4%) |
|
|
Asystole |
19 (47.5%) |
33 (70.2%) |
|
|
Witnessed arrest, n (%) |
0.003 |
||
|
Yes |
25 (62.5%) |
14 (29.8%) |
|
|
No |
15 (37.5%) |
33 (70.2%) |
|
|
Bystander CPR, n (%) |
0.735 |
||
|
Yes |
21 (52.5%) |
21 (44.7%) |
|
|
No |
16 (40.0%) |
21 (44.7%) |
|
|
Unknown |
3 (7.5%) |
5 (10.6%) |
|
|
Adrenaline (epinephrine) administered by ELT, n (%) |
0.001 |
||
|
Yes |
16 (40.0%) |
4 (8.5%) |
|
|
No |
24 (60.0%) |
41 (87.2%) |
|
|
Unknown |
0 (0%) |
2 (4.3%) |
|
|
Initial rSO₂, %, median (IQR) |
42.1 (35.6–47.8) |
45.6 (40.1–49.7) |
0.114 |
|
“Drop phenomenon” observed, n (%) |
0.330 |
||
|
Yes |
3 (7.5%) |
1 (2.1%) |
|
|
No |
37 (92.5%) |
46 (97.9%) |
CPR, cardiopulmonary resuscitation; ELT, emergency life-saving technician; IQR, interquartile range; PEA, pulseless electrical activity; ROSC, return of spontaneous circulation; rSO2, regional saturation of oxygen; VF, ventricular fibrillation.
Comparison of Outcomes by Serial rSO₂ Pattern
Table 2 presents the outcomes according to the type of serial cerebral rSO₂ change, analyzed using multivariable logistic regression. Patients with type 1 (increasing) rSO₂ patterns had significantly higher rates of prehospital ROSC (11/40 [27.5%] vs. 2/47 [4.3%]; adjusted odds ratio [AOR] 5.67, 95% CI 1.04–30.96, p = 0.045) and survival to hospital admission (17/40 [42.5%] vs. 6/41 [12.8%]; AOR 3.56, 95% CI 1.11–11.43, p = 0.033) compared with type 2 (non-increasing) patterns. No significant differences were observed for 1-month survival (5/40 [12.5%] vs. 1/47 [2.1%]; AOR 3.21, 95% CI 0.32–32.72, p = 0.324) or favorable neurological outcome (CPC 1–2: 3/40 [7.5%] vs. 0/47 [0%]).
Table 2. Outcomes by type of serial change in cerebral rSO2
|
Outcome |
Type 1: Increasing pattern (n = 40) |
Type 2: Non-increasing pattern (n = 47) |
Crude OR (95% CI) |
p-value |
Adjusted OR* (95% CI) |
p-value |
|
Pre-hospital ROSC |
27.5% (11/40) |
4.3% (2/47) |
8.53 (1.76–41.32) |
0.008 |
5.67 (1.04–30.96) |
0.045 |
|
Alive at hospital admission |
42.5% (17/40) |
12.8% (6/47) |
5.05 (1.75–14.60) |
0.003 |
3.56 (1.11–11.43) |
0.033 |
|
1-Month survival |
12.5% (5/40) |
2.1% (1/47) |
6.57 (0.73–58.81) |
0.092 |
3.21 (0.32–32.72) |
0.324 |
|
Favorable neurological outcome (CPC 1–2) |
7.5% (3/40) |
0% (0/47) |
Not calculable |
– |
Not calculable |
– |
ORs were calculated for Increasing type vs. Non-increasing type.
CPR, cardiopulmonary resuscitation; CPC, Cerebral Performance Category; OR, odds ratio; CI, confidence interval; ROSC, return of spontaneous circulation; rSO2, regional saturation of oxygen.
*Adjusted for age, sex, witness and bystander CPR.
Drop phenomenon
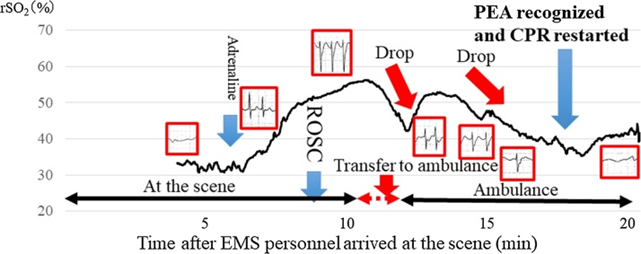
The “drop phenomenon” was observed in 6 of the 94 OHCA patients. A representative case is illustrated in Figure 3: an 82-year-old woman presenting with pulseless electrical activity (PEA) on initial ECG (witnessed [+]; bystander CPR [+]) exhibited gradually increasing rSO₂ values and initially achieved ROSC. However, during transport, despite the presence of QRS complexes on her ECG, her rSO₂ suddenly decreased. This prompted the ELT to recognize recurrent PEA and resume CPR.
Similarly, the other five patients initially achieved ROSC but experienced a sudden decline in rSO₂, after which the ELTs identified PEA and restarted resuscitation. Notably, the drop phenomenon occurred only in patients who had already achieved ROSC. Table 3 summarizes the characteristics of these six patients who experienced this phenomenon.
|
|
|
Figure 3. Representative case of the “drop phenomenon” in serial rSO₂ monitoring |
An 82-year-old woman with pulseless electrical activity (PEA) on initial ECG (witnessed [+]; bystander CPR [+]) showed a gradual increase in rSO₂ and initially achieved ROSC. During transport, although her ECG still displayed QRS complexes, her rSO₂ suddenly dropped. The ELT recognized recurrent PEA and resumed CPR.
Abbreviations: CPR, cardiopulmonary resuscitation; ECG, electrocardiogram; ELT, emergency life-saving technician; PEA, pulseless electrical activity; ROSC, return of spontaneous circulation; rSO₂, regional cerebral oxygen saturation.
Table 3. Characteristics of the 6 patients with ‘Drop phenomenon’ in the serial change of rSO2 values
|
Case |
Sex |
Age |
Bystander CPR |
Administration of adrenaline by ELT |
Initial rSO2 value |
Prehospital ROSC |
Alive at hospital admission |
1-month survival |
CPC 1 or 2 |
Initial rhythm |
Witness |
|
1* |
Female |
82 |
– |
+ |
31.0 |
Yes |
Yes |
No |
No |
PEA |
+ |
|
2 |
Male |
64 |
– |
+ |
40.5 (after ROSC) |
Yes |
No |
No |
No |
PEA |
+ |
|
3 |
Male |
58 |
– |
– |
50.3 |
Yes |
Yes |
No |
No |
PEA |
+ |
|
4 |
Male |
81 |
+ |
– |
40.0 |
Yes |
Yes |
No |
No |
PEA |
+ |
|
5 |
Male |
79 |
– |
– |
53.3 |
Yes |
No |
No |
No |
PEA |
+ |
|
6 |
Male |
95 |
– |
– |
51.5 (after ROSC) |
Yes |
Yes |
No |
No |
PEA |
+ |
CPR, cardiopulmonary resuscitation; CPC, Cerebral Performance Category; ELT, emergency life-saving technician; PEA, pulseless electrical activity; ROSC, return of spontaneous circulation; rSO2, regional saturation of oxygen (*Figure 3).
In this study, we found that the pattern of serial changes in cerebral rSO₂, as measured by emergency life-saving technicians (ELTs) in the prehospital setting, was significantly associated with prehospital ROSC and survival to hospital admission. To our knowledge, this is the first study to examine serial rSO₂ patterns in OHCA patients outside the hospital. Our findings provide insight into dynamic cerebral oxygenation changes during resuscitation and may inform new prehospital strategies, such as real-time monitoring to guide triage or the selection of the most appropriate receiving hospital.
Multivariable logistic regression demonstrated that patients with type 1 (increasing) rSO₂ patterns had significantly higher rates of prehospital ROSC and survival to admission compared with type 2 (non-increasing) patterns (Table 2). Previous studies have suggested that combining baseline rSO₂ with the magnitude of its rise over time may serve as a useful index for predicting ROSC and guiding CPR [3]. Increasing rSO₂ patterns during prehospital resuscitation have also been reported by Genbrugge et al. [16] and Prosen et al. [17]. However, Prosen et al. evaluated rSO₂ only in the five minutes preceding ROSC, limiting observations before patient transport. Unlike our portable monitor, the INVOS oximeter they used is not easily deployed in the field [5, 17]. Moreover, these prior studies focused primarily on absolute rSO₂ values, whereas our study emphasizes the trajectory and pattern of change rather than single measurements.
Our results, along with these previous reports [16,17], highlight the limitations of one-time rSO₂ measurements. Values fluctuate with the patient’s physiological status even before hospital arrival, and initial rSO₂ values did not differ significantly between type 1 and type 2 patterns in our cohort (p = 0.114; Table 1).
Some studies suggest that rSO₂ increases before ROSC may reflect CPR quality [23, 24]. While small rises in rSO₂ may occur during effective CPR in patients who ultimately do not achieve ROSC [4], overall, pre-ROSC increases are not consistently linked to CPR performance. Parnia et al. reported that rSO₂ did not rise in non-ROSC in-hospital cardiac arrest patients, despite early high-quality CPR [25]. In our study, trained ELTs performed CPR, raising the question: what does an rSO₂ increase before ROSC signify? We hypothesize that such increases may indicate early cardiac activity, with a gradual return of spontaneous heartbeat preceding full ROSC. Once ROSC occurs, the pulse returns, and rSO₂ values rise sharply, as illustrated in Figure 2. Further studies are needed to confirm this hypothesis and elucidate the underlying physiological mechanisms.
In contrast, patients exhibiting a type 2 (non-increasing) rSO₂ pattern had very poor outcomes, with prehospital ROSC of 4.3%, survival to hospital admission of 12.8%, 1-month survival of 2.1%, and no patients achieving CPC 1–2 (Table 2). Previous work by Takegawa et al. reported minimal rSO₂ increases during CPR in patients lacking sonographic cardiac activity or in those with Stanford type A aortic dissection [26]. We did not specifically assess whether such conditions were present among our type 2 patients. Further research is warranted to identify the clinical characteristics of patients displaying a non-increasing rSO₂ pattern. In the future, rSO₂-based transport criteria may help optimize hospital selection and resource allocation.
Another notable finding was the identification of the “drop phenomenon” (Figure 3, Table 3), characterized by a sudden decrease in rSO₂ that may reflect abrupt cerebral hypoperfusion. Figure 3 illustrates the relationship between ECG waveforms and serial rSO₂ changes. In the prehospital setting, ELTs can monitor ECG but cannot continuously assess pulse. Detecting a drop phenomenon could prompt more frequent pulse checks and earlier recognition of pulseless electrical activity (PEA), representing one of the most valuable potential benefits of prehospital rSO₂ monitoring.
This study has several limitations. First, rSO₂ monitoring was not blinded, raising the possibility that observed values could have influenced CPR performance. Second, the limited availability and high cost of monitors prevented universal monitoring of all CPA patients during the study period. Third, the low number of ventricular fibrillation cases limited analysis of initial ECG rhythms. Fourth, we could not compare rSO₂ measurements with alternative perfusion markers, such as end-tidal CO₂. Fifth, rSO₂ values may increase in the final 1–2 minutes before ROSC, potentially reflecting the onset of spontaneous circulation prior to measurement.
Conclusion
An increasing pattern of serial rSO₂ changes (type 1) was significantly associated with prehospital ROSC and survival to hospital admission. Continuous prehospital monitoring of cerebral rSO₂ may facilitate earlier recognition of resuscitation status and could inform the development of new strategies to improve outcomes in OHCA patients.
Acknowledgments: We gratefully acknowledge the devoted cooperation of the Osaka Municipal Fire Department.
Conflict of interest: None.
Financial support: This work was supported by JSPS KAKENHI Grant NumberJP19H03758.
Ethics statement: None.