The primary goal of palliative care is to improve the quality of life of individuals confronting terminal medical conditions, alongside supporting their families. In home care settings, relatives typically assume the core caregiving responsibilities, making it paramount to verify their capacity to provide care safely and effectively. This investigation was designed to culturally translate the Care Competency Scale for Family Caregivers in Home Palliative Care (CCSHPC) into Turkish and analyze its measurement characteristics. A methodological research design was deployed, focusing on the primary relatives of individuals receiving palliative support at home. Information was gathered through in-person interviews at the participants’ residences. Evaluating the measurement properties of the Turkish CCSHPC involved testing for content validity, structural validity, and consistency over time. The Turkish adaptation of the CCSHPC displayed strong content validity. Both exploratory and confirmatory factor modeling validated a stable, six-dimensional framework that mirrored the original tool. The instrument also demonstrated satisfactory internal consistency and test–retest stability, confirming its capacity to generate valid and reproducible evaluations of caregiving proficiency within the Turkish population. The Turkish variant of the CCSHPC is a valid and stable tool for assessing caregiving aptitude among relatives providing home-based palliative care. This instrument can be utilized by clinicians to pinpoint specific training and support gaps for relatives, thereby informing the creation of customized nursing care plans.
Introduction
Palliative care is an all-encompassing, interdisciplinary approach that seeks to optimize the comfort and well-being of individuals with life-limiting illnesses and their families by addressing physical, psychological, social, and spiritual concerns [1]. Delivering this specialized care at home has become increasingly vital, particularly for individuals battling advanced chronic conditions or end-of-life illnesses, as it ensures uninterrupted symptom control and mitigates the need for hospital stays [2].
Family members serve as the backbone of home-based palliative services. In many regions where professional medical assistance is sparse, these relatives manage intricate daily medical and comfort tasks, frequently resulting in bodily exhaustion, emotional distress, social withdrawal, and financial difficulties [3]. Such hardships often multiply when the relative lacks adequate preparation for caregiving. A deficit in caregiving capability can jeopardize both the relative’s health and patient-centered outcomes, including pain management, symptom stabilization, and overall quality of life [4].
Care competence encompasses the baseline knowledge, practical skills, personal attitudes, and self-belief required of an informal caregiver to carry out safe, productive care procedures [5]. Research indicates that higher proficiency levels are associated with better symptom regulation, fewer medical complications, and improved patient well-being [6]. Furthermore, competent caregiving minimizes overall strain and burnout for families while reducing their reliance on emergency professional interventions.
Despite the critical nature of this concept, Turkey lacks a validated instrument tailored to quantify the specific caregiving capabilities of relatives delivering home-based palliative care, especially concerning pain and symptom monitoring. Most local literature focuses heavily on caregiver strain, anxiety, or life satisfaction rather than direct capability [7]. Additionally, distinct cultural norms surrounding family obligations, societal values, and care traditions mean that international assessment tools cannot be applied directly without thorough cultural adaptation. This highlights a clear gap for a reliable, validated instrument calibrated for the Turkish community.
The progression of home palliative care is multifaceted, fundamentally reshaping the lives of both the patient and their family. The information, practical skills, and reassurance provided by a caregiver directly impact the quality, safety, and durability of domestic health services [8]. Consequently, objective assessment instruments that gauge caregiving capability are vital for clinical tracking, academic instruction, and field research, yet Turkey currently lacks a culturally modified metric for this task.
To address this issue, this investigation sought to adapt the “Care Competency Scale for Family Caregivers in Home Palliative Care” (CCSHPC)—originally authored in China—into Turkish and to test its psychometric attributes [9]. It is anticipated that this validated version will assist professionals in identifying educational gaps among relatives and aid in structuring targeted support initiatives within domestic palliative care.
Materials and Methods
Population and sample of the study
A methodological approach was employed to execute this study. The baseline population comprised primary informal caregivers for 682 patients receiving domestic palliative care through a state hospital’s home health department in Kütahya, Turkey, between September 15 and November 15, 2025. Following an evaluation of the eligibility benchmarks (acting as a caregiver for a domestic palliative patient, n = 41; holding primary or first-degree care status, n = 85; proficiency in reading and interpreting Turkish, n = 17) alongside the exclusion parameters (employment as a professional health practitioner, n = 4; presenting with intellectual or cognitive deficits, n = 19; working within institutional care facilities, n = 12), a total of 178 individuals were dropped for failing to meet the study criteria. Next, 62 participants were removed due to missing data fields, and 22 were omitted due to duplicate database entries. This left a final analytical sample size of 420 family caregivers.
Power analysis for sample size calculation was performed using G*Power 3.1. Factoring in a moderate effect size (f = 0.30), α = 0.05, and a statistical power level of 0.99, the minimum necessary cohort size was determined to be 358 subjects [10]. Moreover, meeting established criteria for instrument adaptation research (which mandate at least 5–10 respondents per scale item), the final assembly of 420 caregivers was deemed entirely sufficient for rigorous psychometric validation [11].
Study candidates were purposively sampled from the hospital’s home health registry, emphasizing participant accessibility, willingness to cooperate, and hands-on participation in daily care tasks [12].
The baseline inclusion requirements for this study were:
The exclusion parameters were established as follows:
Data collection tools
Personal information form
A questionnaire developed by the investigators, comprising 7 items, was used to record the demographic and clinical profiles of both family caregivers and their patients.
Care Competency Scale for Family Caregivers in Home Palliative Care (CCSHPC)
The CCSHPC, developed by Wang et al., was used to assess the quality of care provision. The instrument consists of 29 items distributed across six dimensions: care knowledge, daily care skills, special care skills, caregiving qualities, self-care practices, and acquisition of social supports and resources. Responses are recorded on a 5-point Likert scale, with higher scores indicating greater caregiving proficiency [9]. Written authorization to execute the Turkish adaptation was secured from the primary author.
Zarit Burden Interview (ZBI)
The level of strain experienced by caregivers was quantified utilizing the Turkish adaptation of the ZBI. This 22-item instrument uses a 5-point Likert scale (0–4), yielding cumulative scores ranging from 0 to 88; higher scores indicate greater perceived strain. The ZBI was utilized as an external benchmark to assess the convergent validity of the CCSHPC [13, 14].
Data collection
Following informed consent, in-person interviews were conducted in respondents’ residences over 2 months. Every interview lasted roughly 40 minutes and involved completing the demographic questionnaire and the evaluation instruments.
Given the sensitive and fragile status of informal caregivers within palliative services, data collection was conducted with heightened ethical awareness. Respondents were explicitly notified of their right to opt out of the research project at any stage without obligation or explanation. Whenever indicators of psychological distress became apparent, the interview session was either paused or permanently halted, at the respondent’s discretion.
Data assessment
Statistical analyses were performed using SPSS version 25 and AMOS version 22. Exploratory Factor Analysis (EFA) alongside consistency testing was executed via SPSS, whereas Confirmatory Factor Analysis (CFA) was carried out through AMOS. The threshold for statistical significance was set at P = 0.05.
Receiver Operating Characteristic (ROC) curves were generated using the ZBI outcomes as an external reference point to determine how effectively the CCSHPC differentiates among varying severities of caregiver strain (thresholds set at 20, 40, and 60). This ROC analysis was modeled to establish clinically meaningful cut-off thresholds for the CCSHPC, tying its measurement capacity to practical healthcare decisions by evaluating how accurately it distinguishes among caregivers experiencing disparate levels of strain. Sensitivity, specificity, and Area Under the Curve (AUC) statistics were determined, and the ideal diagnostic thresholds were identified through Youden’s index.
Ethics of the study
Formal authorization for the cultural adaptation of the instrument was granted by the original author. Ethical clearance for the research was issued by the Kütahya Health Sciences University Ethics Committee (Resolution No: 11/03). Administrative clearances were also obtained from the participating institutions, and all respondents provided written informed consent before enrollment. The investigation adhered strictly to the ethical standards outlined in the Declaration of Helsinki.
Psychometric assessment
Language validity
A forward-and-backward translation protocol was deployed. Two independent language experts translated the original instrument into Turkish, after which the versions were reconciled into a single text; this draft was subsequently back-translated into English by two native English speakers. A panel consisting of five nursing scholars evaluated the instrument to confirm its semantic and conceptual equivalence. A preliminary pilot trial involving 20 caregivers was conducted, resulting in minor grammatical and wording refinements [11].
Content validity
The appropriateness of the content was verified by a panel of specialists with at least 10 years of professional experience in palliative care. The calculated item-level and scale-level content validity indices demonstrated strong consensus I-CVI = 0.84; S-CVI = 0.92) [15].
Construct validity
Exploratory factor analysis (EFA) was performed using Principal Component Analysis (PCA) with Varimax rotation to examine the instrument’s underlying structure. PCA was selected during this initial phase because it is a common convention in cross-cultural scale translation projects for preliminary factor extraction and data simplification; nonetheless, we recognize that latent-variable extraction techniques may be more appropriate when the primary aim is to model underlying latent factors [16]. It must be emphasized, however, that PCA primarily serves as a data-reduction tool rather than a genuine latent-variable framework. Following this, confirmatory factor analysis (CFA) was executed to validate the proposed six-factor structure [17].
Reliability
Measurement consistency was evaluated using Cronbach’s alpha, McDonald’s omega, item–total correlations, split-half consistency measures, and test–retest reliability scoring (administered across a two-week window, n = 50) [18].
Results and Discussion
Table 1. Individual characteristics of caregivers. From: Care competency scale for family caregivers in home palliative care: Turkish adaptation, validity, and reliability study.
|
Variable |
Category |
% |
N |
|
Gender |
Female |
63.8 |
268 |
|
Male |
36.1 |
152 |
|
|
Level of education |
Primary school |
20.0 |
84 |
|
Secondary school |
58.3 |
245 |
|
|
Tertiary education |
21.7 |
91 |
|
|
Marital status |
Single |
20.2 |
85 |
|
Married |
79.8 |
335 |
|
|
Financial status |
Good |
22.9 |
96 |
|
Moderate |
63.8 |
268 |
|
|
Poor |
13.3 |
56 |
|
|
Relationship to care recipient |
Daughter |
44.3 |
186 |
|
Son |
27.4 |
115 |
|
|
Spouse |
23.3 |
98 |
|
|
Other relatives/caregivers |
5.0 |
21 |
|
|
Diagnosis of the care recipient |
Alzheimer’s disease |
9.5 |
40 |
|
Diabetes mellitus (DM) |
16.2 |
68 |
|
|
Hypertension (HT) |
10.2 |
43 |
|
|
Cancer |
23.3 |
98 |
|
|
Chronic obstructive pulmonary disease (COPD) |
8.3 |
35 |
|
|
Heart failure (HF) |
8.6 |
36 |
|
|
Stroke |
16.0 |
67 |
|
|
Other diagnoses |
7.9 |
33 |
|
|
Age (years) |
Mean ± SD |
48.33 ± 8.66 |
|
|
Range (Min–Max) |
32.00–63.00 |
||
|
CCSHPC total score |
Mean ± SD |
87.44 ± 13.29 |
|
|
Range (Min–Max) |
16.00–139.00 |
||
|
ZBI total score |
Mean ± SD |
44.64 ± 14.92 |
|
|
Range (Min–Max) |
4.00–84.00 |
Abbreviations: DM = Diabetes Mellitus, HT = Hypertension, COPD = Chronic obstructive pulmonary disease, HF = Heart failure, SD = Standart Deviation
The baseline demographics for the 420 participating family caregivers are detailed in Table 1. Women comprised the vast majority of the cohort (63.8%), with an overall sample mean age of 48.33 ± 8.66 years. Most respondents identified as married (79.8%) and reported a middle socioeconomic status (63.8%). Regarding academic attainment, 58.3% of the sample had completed high school. Regarding familial relationships, nearly half of those surveyed were the care recipient’s daughters (44.3%), and an oncological diagnosis was documented in 23.3% of the patient population. Taken together, these metrics indicate that home-based palliative care within this demographic is primarily sustained by middle-aged female relatives.
Validity
To establish the construct validity of the newly adapted Turkish CCSHPC, EFA and CFA were conducted.
The initial EFA metrics confirmed that the dataset was highly appropriate for factor modeling (KMO = 0.83; Bartlett’s test χ² = 8704.79, P ≤ 0.001). Individual factor loadings ranged from 0.64 to 0.93, and the cumulative six-factor framework accounted for 72.75% of the total variance.
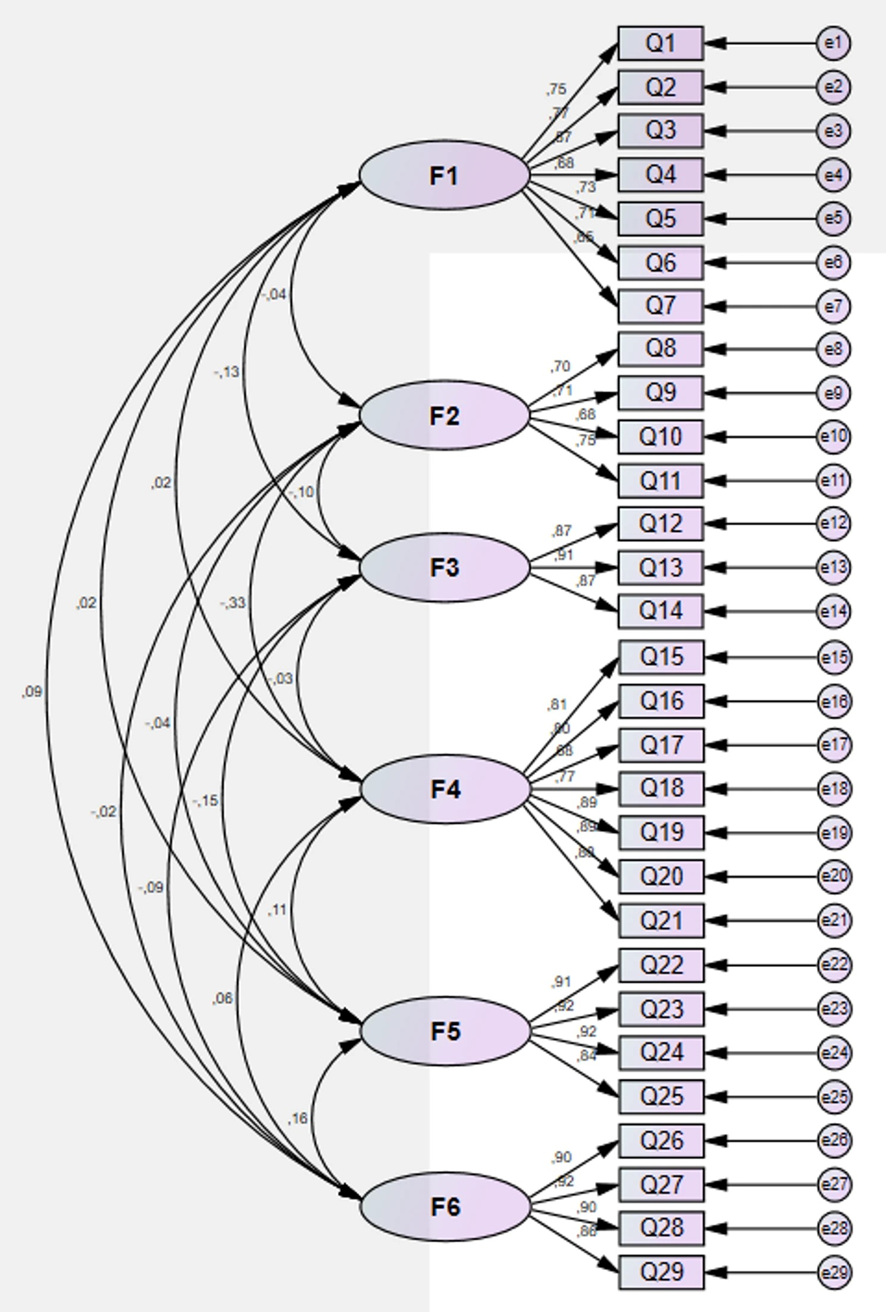
This identical six-factor layout, established via EFA, was subsequently verified via CFA. The structural model displayed a satisfactory level of fit when tested against the empirical data (Table 2). The corresponding standardized path model is shown in Figure 1. Together, the EFA and CFA parameters indicate that the original organizational structure remains stable when applied to the Turkish population, confirming the structural validity of the translated tool.
Table 2. CCSHPC confirmatory factor analysis results. From: Care competency scale for family caregivers in home palliative care: Turkish adaptation, validity, and reliability study.
|
Model fit criteria |
Acceptable |
Appropriate |
Estimated |
|
X2/df |
≤ 5 |
≤ 3 |
2.465 |
|
Comparative Fit Indices |
|
|
|
|
RMSEA |
≤ 0.08 |
≤ 0.05 |
0.055 |
|
NFI |
≥ 0.90 |
≥ 0.95 |
0.917 |
|
CFI |
≥ 0.95 |
≥ 0.97 |
0.965 |
|
IFI |
≥ 0.90 |
≥ 0.95 |
0.965 |
|
TLI |
≥ 0.90 |
≥ 0.95 |
0.955 |
|
Absolute Fit Indices |
|
|
|
|
GFI |
≥ 0.85 |
≥ 0.90 |
0.905 |
|
Residual-based Fit Indices |
|
|
|
|
RMR |
≤ 0.08 |
≤ 0.05 |
0.07 |
Abbreviations: RMSEA = Root Mean Square Error of Approximation, NFI = Normalized Fit Index, CFI = Comparative Fit Index, IFI = Incremental Fit Index, TLI = Tucker-Lewis Index, GFI = Goodness Of Fit Index, RMR = Root Mean Square Residual.
|
|
|
Figure 1. PATH diagram regarding the factor structure of the scale. Chi-square = 892.330, df = 362, p = 0.000, RMSEA = 0.055. F1: Care knowledge; F2: Daily care skills; F3: Special care skills; F4: Caregiving qualities; F5: Self-care practices; F6: Acquisition of social supports and resources |
Reliability
The Turkish CCSHPC displayed strong internal consistency. The cumulative Cronbach’s \alpha reached 0.80, while the overall McDonald’s \omega was 0.84. Reliability scores for the isolated subscales ranged from 0.85 to 0.94, indicating robust to excellent internal consistency across each dimension. Furthermore, item–total correlations ranged from 0.53 to 0.88, indicating that each question contributed meaningfully to the scale’s overall performance.
Temporal stability was assessed using a 2-week test–retest window (n = 50), yielding a correlation coefficient of 0.92, indicating strong temporal stability. Additionally, split-half reliability testing showed a strong positive association between the instrument’s halves. In short, these statistical indicators confirm that the Turkish variant of the CCSHPC delivers highly dependable and stable outcomes over extended periods.
ROC analysis results
An inverse correlation was observed between the cumulative CCSHPC scores and ZBI measurements (r < 0; P < 0.001), confirming the expected negative relationship between a relative’s caregiving aptitude and their perceived care strain.
ROC curve analyses were conducted to assess the effectiveness of the CCSHPC in distinguishing between distinct strata of caregiver strain. The assessment instrument demonstrated high accuracy in isolating different tiers of caregiving proficiency:
These specific point thresholds can be useful to clinicians seeking to identify vulnerable relatives who would benefit most from targeted skills training or psychological support systems.
This study evaluated the measurement validity and reliability of the Turkish adaptation of the CCSHPC. To our knowledge, this is the first psychometrically tested instrument in Turkey, explicitly developed to measure caregiving aptitude among relatives delivering home-based palliative care. While prior national research has primarily focused on caregiver burden, psychological distress, or general life satisfaction, this project introduces an explicit, objective measure of caregiving capability, filling a prominent void in both clinical management and the academic literature.
The combined EFA and CFA findings verified a six-factor model that mirrors the framework of the original instrument. The amount of explained variance and the overall alignment of the factor loadings confirm that the conceptual dimensions of care knowledge, daily care skills, special care skills, caregiving qualities, self-care practices, and acquisition of social supports and resources remain highly relevant and applicable within the Turkish cultural environment. These patterns suggest that the foundational components of caregiving proficiency, as outlined in the original Chinese scale, are largely cross-culturally generalizable despite differences in domestic dynamics and care routines [9].
Preserving the original subscale architecture is particularly meaningful given the deeply family-centric nature of healthcare in Turkey, where caregiving responsibilities are frequently divided among extended family members and heavily reinforced by social expectations. This unique cultural environment likely enhanced the high level of coherence observed in subscales such as caregiving qualities and self-care practices, which reflect both internal emotional dedication and self-regulation in managing an ill relative [19].
The Turkish version of the CCSHPC demonstrated strong internal consistency and excellent test–retest stability, indicating that the tool provides reliable and reproducible evaluations over time. These statistical milestones support integrating this metric into both cross-sectional clinical screenings and longitudinal tracking of caregiver aptitude, such as in future intervention programs or educational workshops [20].
From a clinical perspective, the CCSHPC provides an organized framework for pinpointing specific proficiencies and deficiencies among relatives delivering home-based palliative care. The scores from individual subscales can help nursing professionals design tailored training programs, particularly by focusing on areas such as symptom tracking, day-to-day care techniques, and caregivers’ self-care routines. By systematically evaluating caregiving aptitude, medical practitioners can readily identify relatives who need specialized training, more frequent monitoring, or psychological support, thereby optimizing the targeted allocation of healthcare resources [19].
At an institutional level, the CCSHPC can be incorporated into standard domestic palliative care protocols to foster empirical care coordination, promote the early identification of care-related hazards, and maximize patient safety. Furthermore, this assessment tool can serve as a meaningful benchmark for measuring the efficacy of caregiver instructional workshops and nursing-directed support programs within community health operations [21].
The ROC curve analyses provided further evidence of the instrument’s discriminant validity, demonstrating that elevated CCSHPC scores consistently correlated with lower levels of caregiver strain. The identified diagnostic thresholds provide baseline, clinically actionable benchmarks for classifying caregivers by proficiency level. These scores can help practitioners prioritize families who stand to benefit most from additional instruction or emotional support systems. Such thresholds are especially valuable in domestic palliative care environments, where systematic tracking of caregiving capacity can guide personalized care configuration and asset management. These specific cut-off points can be incorporated into standard home-based palliative assessments to categorize caregivers by their required level of assistance and to prioritize customized educational or psychological interventions, serving as an adjunct to clinical oversight to detect relatives who need extra resources [19, 21].
In addition to its domestic utility, this investigation enriches the global academic literature on evaluating caregiver proficiency by demonstrating that the CCSHPC can be effectively translated into an entirely different cultural and medical framework. The consistency between the Turkish factor structure and that of the baseline instrument supports international comparative research on caregiving aptitude, enabling valid cross-national analyses. The preservation of the baseline six-dimensional framework within the Turkish sample matches the structural theory outlined in the foundational validation research, indicating that the core elements of caregiving capability in domestic palliative environments are not restricted to a single cultural background. Simultaneously, caregiving routines continue to be influenced by localized community expectations, family dynamics, and the traits of the underlying medical system, all of which must be factored in when interpreting multi-country data [9, 21].
By delivering a culturally calibrated yet theoretically equivalent Turkish variant of the CCSHPC, this project establishes a uniform measurement framework for future multi-country investigations. The routine deployment of this instrument across various nations could expand the current understanding of how cultural, societal, and systemic health variables affect a relative’s capabilities and resource requirements. Such comparative documentation can guide the development of culturally adapted caregiver training curricula and contribute to global academic discourse on optimal strategies for family-focused palliative care [9].
This project was carried out within a single municipality and centered on an individual home health department; consequently, the outcomes may not be entirely representative of all geographic zones in Turkey. Future investigations encompassing varied geographic and cultural environments are required to reinforce the external validity of these results. Additionally, the methodology relied on self-reported instruments, which are inherently vulnerable to recall and social desirability biases. Although the metric demonstrated robust psychometric properties, qualitative investigations could offer a deeper understanding of caregivers’ subjective experiences of competence and its underlying influences. Furthermore, while PCA is routinely used in scale translation research, it primarily serves as a tool for data reduction rather than as a true latent-variable model; thus, subsequent projects might employ common factor extraction methods to examine the instrument’s dimensions more deeply. Lastly, household size and potential domestic disputes over care duties were not directly examined, representing areas warranting deeper future inquiry.
Conclusion
The Turkish translation of the CCSHPC is a valid and reliable tool for quantifying relatives’ caregiving capacity in home-based palliative care settings. This scale can be seamlessly integrated into everyday clinical workflows to identify caregivers’ educational and psychological needs, guide personalized nursing protocols, and reinforce family-centered care coordination in palliative care settings.
Acknowledgments: None
Conflict of interest: None
Financial support: None
Ethics statement: Ethical approval was obtained from the Kütahya Health Sciences University Non-Interventional Research Ethics Committee (Approval No: 2025/11 − 03) and from the participating hospital. All participants were informed of the aims and procedures of the study, and written informed consent was obtained from each participant. The study was conducted in accordance with the principles of the Declaration of Helsinki.